






The simplified Pulmonary Embolism Severity Index (sPESI) is widely used for risk stratification in patients with acute symptomatic pulmonary embolism (PE). Electrocardiography (ECG) provides information on cardiac stress, including right ventricular (RV) stress, but is not included in current guidelines for PE risk stratification.
MethodsWe analyzed 32,113 hemodynamically stable patients with acute symptomatic PE enrolled in the RIETE registry. ECGs obtained within 24h of diagnosis were classified as normal or abnormal according to predefined criteria. The primary outcome was 30-day all-cause mortality. Secondary outcomes included 30-day PE-related mortality and a composite endpoint of 30-day all-cause mortality, early hemodynamic deterioration, or need for escalated therapy. The prognostic performance of sPESI was compared with an ECG-augmented strategy (sPESI-ECG) using diagnostic accuracy metrics and multivariable logistic regression. A prespecified subgroup analysis was performed in patients with CT-assessed RV/LV ratio.
ResultsAn abnormal ECG was present in 63.1% of patients and was associated with more severe presentation and markers of RV dysfunction. Thirty-day mortality was higher in patients with abnormal vs normal ECG findings (5.4% vs 2.9%). For the primary outcome, sPESI-ECG showed higher sensitivity than sPESI alone (97.7% vs 94.5%) with lower specificity. Patients classified as low risk by sPESI-ECG represented a smaller subgroup with numerically lower 30-day all-cause mortality than those classified as low risk by sPESI (0.62% vs 0.82%). Findings were consistent in multivariable analysis and in the CT subgroup.
ConclusionsIncorporating ECG findings into sPESI may help identify a smaller subgroup of patients at very low short-term risk.

Early risk stratification is a cornerstone of the management of acute pulmonary embolism (PE), as it informs decisions regarding hospitalization, level of monitoring, and the potential need for reperfusion or escalation of therapy. Although most patients with PE present without hemodynamic instability, a substantial proportion experience early clinical deterioration or death despite initially stable vital signs. Identifying such patients at presentation remains a major clinical challenge [1–3].
Current clinical practice guidelines recommend using validated clinical prediction rules, particularly the simplified Pulmonary Embolism Severity Index (sPESI), to estimate early mortality risk and identify candidates for early discharge or outpatient treatment. The sPESI relies exclusively on clinical variables and vital signs, offering simplicity and broad applicability [1,4]. However, its limited specificity and the residual risk observed even among patients classified as low risk highlight the need for improved risk stratification strategies [4,5].
Although abnormal electrocardiographic (ECG) findings are neither sensitive nor specific for the diagnosis of PE, previous studies suggest that they may provide independent prognostic information in these patients [6,7]. Nevertheless, ECG abnormalities are not incorporated into sPESI or any clinical score, nor are they routinely used for formal risk stratification in hemodynamically stable patients with PE [8,9]. Beyond its established role in acute coronary syndromes and other cardiovascular conditions [10,11], ECG provides clinically meaningful information across a broad range of cardiopulmonary presentations. Although previous studies have reported associations between ECG abnormalities and adverse outcomes in PE [12–15], the clinical role of ECG abnormalities in PE remains underrecognized [9].
Advanced imaging and biomarkers, such as computed tomography (CT)-derived right ventricular (RV) dysfunction and cardiac troponins, have demonstrated prognostic value, but their availability may be limited, and their routine use in all hemodynamically stable patients remains controversial. In contrast, ECG represents a rapid, inexpensive, and widely accessible tool [5,9].
We hypothesized that ECG information, when integrated with sPESI, could refine short-term risk classification and help identify patients at very low short-term risk. Using data from the large, prospective RIETE registry, we aimed to evaluate the prognostic significance of the absence of ECG abnormalities in hemodynamically stable patients with acute symptomatic PE. Furthermore, a prespecified analysis was conducted to determine its additional prognostic value beyond the CT-assessed RV-to-left ventricular (LV) ratio.
MethodsStudy design and populationWe conducted an observational cohort study using prospectively collected data from the RIETE (Registro Informatizado Enfermedad Tromboembólica) registry (ClinicalTrials.gov identifier: NCT02832245), an ongoing international registry of patients with PE or deep vein thrombosis (DVT) that includes more than 200 centers across 28 countries. The registry design has been described previously [16]. Patients with objectively confirmed PE, as demonstrated by contrast-enhanced CT, were consecutively enrolled. All patients provided written informed consent in accordance with the requirements of the local ethics committees.
We included patients enrolled in RIETE between January 1st, 2001, and May 31st, 2025, who were diagnosed with hemodynamically stable, symptomatic acute PE, either in the emergency department or during hospitalization. Central PE was defined as the presence of thrombus in the main pulmonary artery (PA) or in the left or right main PA, whereas peripheral PE was defined as thrombus limited to the remaining pulmonary arterial territories [17]. Baseline data included demographic characteristics, clinical presentation, ECG information, and diagnostic test results.
An abnormal ECG was defined as the presence of at least 1 of the following prespecified findings: heart rate <50 or >100beats/min, any rhythm other than sinus rhythm, right bundle branch block (RBBB), S1Q3T3 pattern, or T-wave inversion in the precordial leads. All patients were followed up for 30 days to assess clinical outcomes.
Eligible patients met all the following inclusion criteria: (1) age ≥18 years; (2) imaging-confirmed, hemodynamically stable acute symptomatic PE; and (3) ECG performed within 24h of PE diagnosis. We excluded patients with (1) incidental or asymptomatic PE; (2) hemodynamic instability at presentation, defined as systolic blood pressure <90mm Hg for >15min not attributable to hypovolemia, sepsis, or arrhythmia; (3) no ECG within 24h of diagnosis; or (4) missing variables required to calculate the original sPESI. All patients were followed up for 30 days to assess clinical outcomes.
Simplified PESI score and RV dysfunctionThe original sPESI assigns 1 point for each of the following variables: age >80 years, past medical history of cancer, chronic cardiopulmonary disease, heart rate ≥110beats/min, systolic blood pressure <100mm Hg, and arterial oxygen saturation <90% [4]. Patients with a score of 0 points were classified as low risk.
A modified version using the same variables but with a heart rate threshold of 100beats/min has previously shown enhanced prognostic performance when combined with a CT-assessed RV/LV ratio ≥1.0; this model is referred to as the modified sPESI plus CT-assessed RV/LV ratio model [5] (Supplementary Table S1).
ElectrocardiogramECG interpretation was performed by the treating physicians and recorded in the RIETE case report form. A normal ECG was defined as sinus rhythm, upright P waves in leads I, II, and aVF, heart rate between 50 and 100beats/min, QRS duration ≤120ms, and absence of predefined abnormalities. ECGs were dichotomized as normal vs abnormal. This composite ECG definition was intended to identify the absence of any predefined ECG abnormality rather than to represent a single pathophysiological mechanism.
Integration of ECG into risk stratificationWe constructed an sPESI-ECG score by assigning 1 point for each of the following variables: age >80 years, cancer, chronic cardiopulmonary disease, abnormal ECG, systolic blood pressure <100mm Hg, and arterial oxygen saturation <90%. The heart rate variable in the original sPESI was replaced, rather than supplemented, by the dichotomized ECG variable to avoid double counting. Thus, sPESI-ECG should be considered a modified risk classification strategy rather than the original validated sPESI score.
In addition, we assessed a combined model that incorporated the variable CT-assessed RV/LV ratio ≥1.0, assigning 1 additional point. This model was termed the sPESI-ECG plus CT-assessed RV/LV ratio model. Patients with a score of 0 in either model were classified as very low risk (Supplementary Table S1).
Study endpointsThe primary endpoint was 30-day all-cause mortality. Secondary endpoints included 30-day PE-related mortality and a composite endpoint comprising 30-day all-cause mortality, early hemodynamic deterioration, defined as systolic blood pressure <90mm Hg for >15min not attributable to hypovolemia, sepsis, or arrhythmia and occurring within 48h of PE diagnosis, or need for escalated therapy, including rescue systemic thrombolysis, surgical or mechanical thrombectomy, extracorporeal membrane oxygenation, or vasopressor/inotropic support. Outcomes were analyzed as dichotomous variables. In addition, a predefined subanalysis was performed in patients with available CT-assessed RV/LV ratio data to determine whether this finding further enhanced risk stratification.
Statistical analysisCategorical variables were expressed as frequencies and percentages. Continuous variables were reported as mean±SD or median (IQR), as appropriate. Normality was assessed using the Kolmogorov–Smirnov test. Comparisons were performed using the Student t test or analysis of variance for normally distributed variables and the Mann–Whitney U or Kruskal–Wallis test for nonnormally distributed variables. We calculated the proportion of patients classified as low risk by each strategy and estimated diagnostic performance metrics, including sensitivity, specificity, positive predictive value (PPV), negative predictive value (NPV), and likelihood ratios, for each outcome.
Sensitivity was defined as the proportion of patients with the outcome correctly identified as high risk, and specificity was defined as the proportion of patients without the outcome correctly classified as low risk. Pairwise comparisons between strategies were performed using exact binomial tests. Confidence intervals for absolute differences were calculated using the Agresti–Min method.
Logistic regression analyses were performed to assess associations with outcomes. Univariable logistic regression estimated crude ORs with 95%CIs. Variables selected a priori included male sex, syncope, elevated cardiac troponin, and renal insufficiency. Multivariable logistic regression was performed using stepwise selection, and adjusted ORs were reported for variables meeting inclusion criteria, defined as P<.10 in univariable analysis. Multicollinearity was assessed using the variance inflation factor (VIF), with values >5 considered suggestive of problematic multicollinearity.
For regression models, covariables had <5% missing data, and complete-case analysis was performed, assuming data were missing completely at random, consistent with prior RIETE analyses [5]. Variables required for sPESI calculation with >20% missingness were not included as independent predictors, and patients with missing sPESI components were excluded from the corresponding analyses.
Two-sided P values <.05 were considered statistically significant. Analyses were conducted using IBM SPSS version 26 and R version 4.2.2 (packages binom, car, DescTools, and DTComPair).
ResultsStudy population and baseline characteristicsA total of 32,113 hemodynamically stable patients with acute symptomatic PE were included in the analysis (Fig. 1). The mean (SD) age was 68 (16) years, and 52.8% were women. According to the original sPESI, 9771 patients (30.4%) were classified as low risk at presentation.

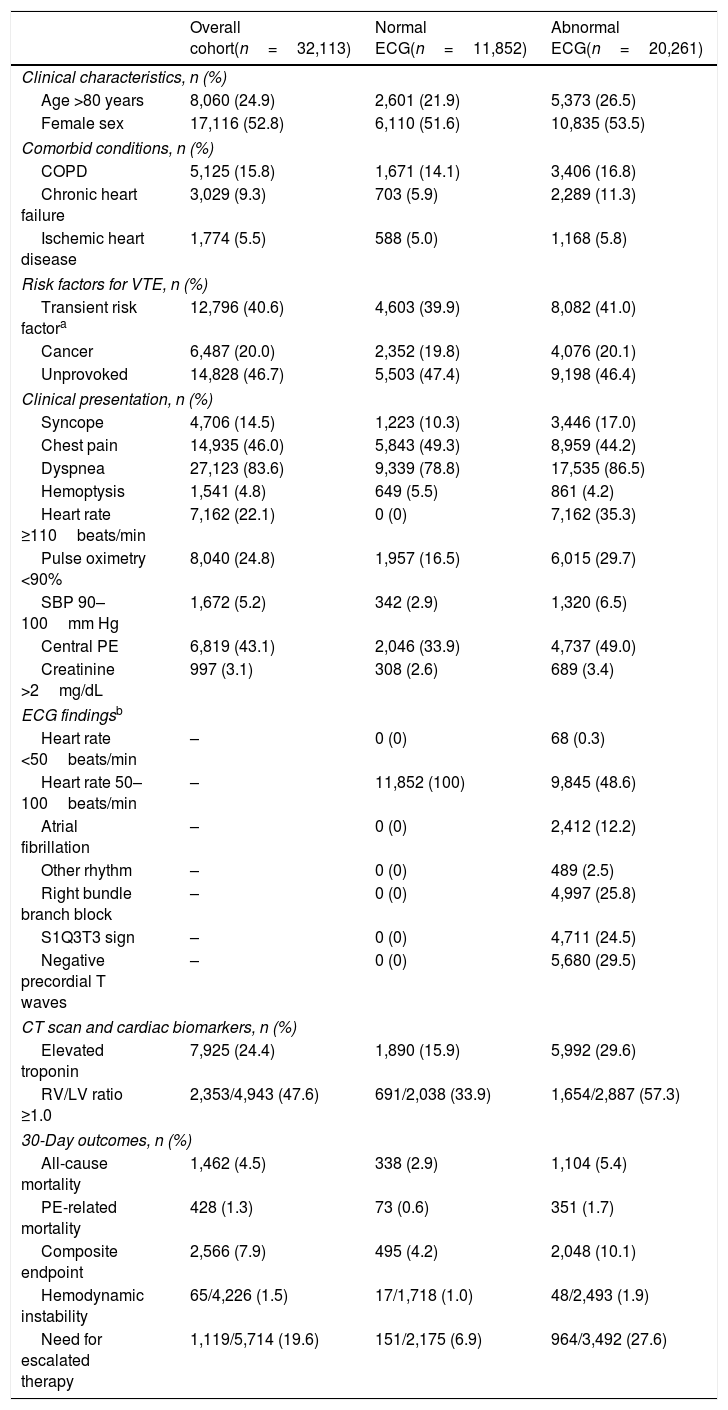
A normal ECG was observed in 11,852 patients (36.9%), whereas 20,261 patients (63.1%) had an abnormal ECG. Among these patients, 28.1% had a heart rate >110beats/min, 12.2% had atrial fibrillation (AF), 25.8% had RBBB, and 24.5% had an S1Q3T3 pattern. Patients with abnormal ECG findings were older and more frequently presented with cardiopulmonary comorbidities, including chronic obstructive pulmonary disease and chronic heart failure (Table 1).
Overall cohort baseline characteristics and differences between patients with normal vs abnormal ECG findings.
| Overall cohort(n=32,113) | Normal ECG(n=11,852) | Abnormal ECG(n=20,261) | |
|---|---|---|---|
| Clinical characteristics, n (%) | |||
| Age >80 years | 8,060 (24.9) | 2,601 (21.9) | 5,373 (26.5) |
| Female sex | 17,116 (52.8) | 6,110 (51.6) | 10,835 (53.5) |
| Comorbid conditions, n (%) | |||
| COPD | 5,125 (15.8) | 1,671 (14.1) | 3,406 (16.8) |
| Chronic heart failure | 3,029 (9.3) | 703 (5.9) | 2,289 (11.3) |
| Ischemic heart disease | 1,774 (5.5) | 588 (5.0) | 1,168 (5.8) |
| Risk factors for VTE, n (%) | |||
| Transient risk factora | 12,796 (40.6) | 4,603 (39.9) | 8,082 (41.0) |
| Cancer | 6,487 (20.0) | 2,352 (19.8) | 4,076 (20.1) |
| Unprovoked | 14,828 (46.7) | 5,503 (47.4) | 9,198 (46.4) |
| Clinical presentation, n (%) | |||
| Syncope | 4,706 (14.5) | 1,223 (10.3) | 3,446 (17.0) |
| Chest pain | 14,935 (46.0) | 5,843 (49.3) | 8,959 (44.2) |
| Dyspnea | 27,123 (83.6) | 9,339 (78.8) | 17,535 (86.5) |
| Hemoptysis | 1,541 (4.8) | 649 (5.5) | 861 (4.2) |
| Heart rate ≥110beats/min | 7,162 (22.1) | 0 (0) | 7,162 (35.3) |
| Pulse oximetry <90% | 8,040 (24.8) | 1,957 (16.5) | 6,015 (29.7) |
| SBP 90–100mm Hg | 1,672 (5.2) | 342 (2.9) | 1,320 (6.5) |
| Central PE | 6,819 (43.1) | 2,046 (33.9) | 4,737 (49.0) |
| Creatinine >2mg/dL | 997 (3.1) | 308 (2.6) | 689 (3.4) |
| ECG findingsb | |||
| Heart rate <50beats/min | – | 0 (0) | 68 (0.3) |
| Heart rate 50–100beats/min | – | 11,852 (100) | 9,845 (48.6) |
| Atrial fibrillation | – | 0 (0) | 2,412 (12.2) |
| Other rhythm | – | 0 (0) | 489 (2.5) |
| Right bundle branch block | – | 0 (0) | 4,997 (25.8) |
| S1Q3T3 sign | – | 0 (0) | 4,711 (24.5) |
| Negative precordial T waves | – | 0 (0) | 5,680 (29.5) |
| CT scan and cardiac biomarkers, n (%) | |||
| Elevated troponin | 7,925 (24.4) | 1,890 (15.9) | 5,992 (29.6) |
| RV/LV ratio ≥1.0 | 2,353/4,943 (47.6) | 691/2,038 (33.9) | 1,654/2,887 (57.3) |
| 30-Day outcomes, n (%) | |||
| All-cause mortality | 1,462 (4.5) | 338 (2.9) | 1,104 (5.4) |
| PE-related mortality | 428 (1.3) | 73 (0.6) | 351 (1.7) |
| Composite endpoint | 2,566 (7.9) | 495 (4.2) | 2,048 (10.1) |
| Hemodynamic instability | 65/4,226 (1.5) | 17/1,718 (1.0) | 48/2,493 (1.9) |
| Need for escalated therapy | 1,119/5,714 (19.6) | 151/2,175 (6.9) | 964/3,492 (27.6) |
COPD, chronic obstructive pulmonary disease; CT, computed tomography; ECG, electrocardiogram; LV, left ventricle; PE, pulmonary embolism; RV, right ventricle; SBP, systolic blood pressure; VTE, venous thromboembolism.
Patients with abnormal ECG findings presented with a more severe clinical profile. Compared with those with normal ECG findings, they more frequently presented with syncope (17.0% vs 10.3%), dyspnea (86.5% vs 78.8%), hypoxemia (oxygen saturation <90%: 29.7% vs 16.5%), and systolic blood pressure between 90 and 100mm Hg (6.5% vs 2.9%). Central PE on computed tomography was more common among patients with abnormal ECG findings (49.0% vs 33.9%). Markers of RV dysfunction were also more prevalent in patients with abnormal ECG findings, including elevated cardiac troponin levels (29.6% vs 15.9%) and CT-assessed RV/LV ratio ≥1.0 (57.3% vs 33.9%) (Table 1).
Endpoints according to ECG statusDuring follow-up, 30-day all-cause mortality occurred in 1462 patients (4.5%). The incidence was nearly twice as high in patients with abnormal ECG findings as in those with normal ECG findings (5.4% vs 2.9%). Similarly, 30-day PE-related mortality was higher among patients with abnormal ECG findings (1.7% vs 0.6%), and the composite endpoint occurred more than twice as frequently (10.1% vs 4.2%).
Early hemodynamic deterioration occurred in 65 of 4226 patients (1.5%), and 1119 of 5714 patients (19.6%) required therapy escalation, with a higher rate among patients with abnormal ECG findings (Table 1).
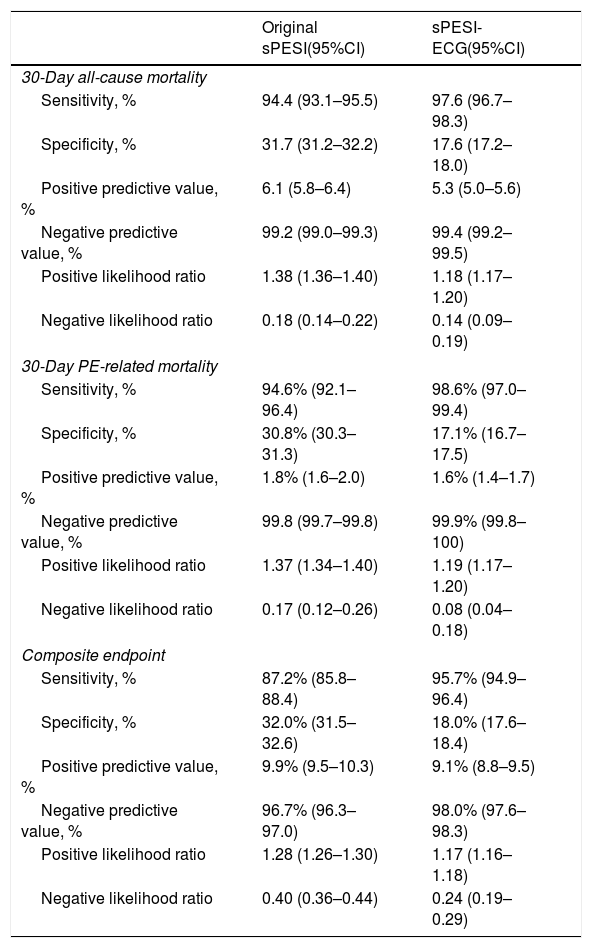
Diagnostic performance of risk stratification scoresFor 30-day overall mortality, the original sPESI demonstrated high sensitivity (94.5%) but limited specificity (31.6%), with an NPV of 99.2%. Incorporation of ECG findings into sPESI increased sensitivity to 97.7% and NPV to 99.4% (95%CI, 99.1–99.6), at the expense of lower specificity (17.4%).
Similar increases in sensitivity and NPV were observed for 30-day PE-related mortality and for the composite endpoint, with an NPV of 98.0% (95%CI, 97.6–98.3). The increase in NPV for the primary and secondary endpoints was statistically significant (P<.01) (Table 2). Positive predictive values remained low across all outcomes for both scores.
Diagnostic accuracy performance for primary and secondary endpoints (n=32,113).
| Original sPESI(95%CI) | sPESI-ECG(95%CI) | |
|---|---|---|
| 30-Day all-cause mortality | ||
| Sensitivity, % | 94.4 (93.1–95.5) | 97.6 (96.7–98.3) |
| Specificity, % | 31.7 (31.2–32.2) | 17.6 (17.2–18.0) |
| Positive predictive value, % | 6.1 (5.8–6.4) | 5.3 (5.0–5.6) |
| Negative predictive value, % | 99.2 (99.0–99.3) | 99.4 (99.2–99.5) |
| Positive likelihood ratio | 1.38 (1.36–1.40) | 1.18 (1.17–1.20) |
| Negative likelihood ratio | 0.18 (0.14–0.22) | 0.14 (0.09–0.19) |
| 30-Day PE-related mortality | ||
| Sensitivity, % | 94.6% (92.1–96.4) | 98.6% (97.0–99.4) |
| Specificity, % | 30.8% (30.3–31.3) | 17.1% (16.7–17.5) |
| Positive predictive value, % | 1.8% (1.6–2.0) | 1.6% (1.4–1.7) |
| Negative predictive value, % | 99.8 (99.7–99.8) | 99.9% (99.8–100) |
| Positive likelihood ratio | 1.37 (1.34–1.40) | 1.19 (1.17–1.20) |
| Negative likelihood ratio | 0.17 (0.12–0.26) | 0.08 (0.04–0.18) |
| Composite endpoint | ||
| Sensitivity, % | 87.2% (85.8–88.4) | 95.7% (94.9–96.4) |
| Specificity, % | 32.0% (31.5–32.6) | 18.0% (17.6–18.4) |
| Positive predictive value, % | 9.9% (9.5–10.3) | 9.1% (8.8–9.5) |
| Negative predictive value, % | 96.7% (96.3–97.0) | 98.0% (97.6–98.3) |
| Positive likelihood ratio | 1.28 (1.26–1.30) | 1.17 (1.16–1.18) |
| Negative likelihood ratio | 0.40 (0.36–0.44) | 0.24 (0.19–0.29) |
ECG, electrocardiogram; PE, pulmonary embolism; sPESI, simplified Pulmonary Embolism Severity Index; 95%CI, 95% confidence interval.
Receiver operating characteristic curve analysis showed comparable discrimination between strategies. For 30-day all-cause mortality, the C statistic was 0.73 (95%CI, 0.72–0.74) for both the original sPESI and sPESI-ECG. For 30-day PE-related mortality, discrimination was similar: 0.73 (95%CI, 0.71–0.76) vs 0.74 (95%CI, 0.72–0.76). For the composite endpoint, the C statistic was 0.66 (95%CI, 0.64–0.67) for the original sPESI and 0.66 (95%CI, 0.65–0.67) for sPESI-ECG.
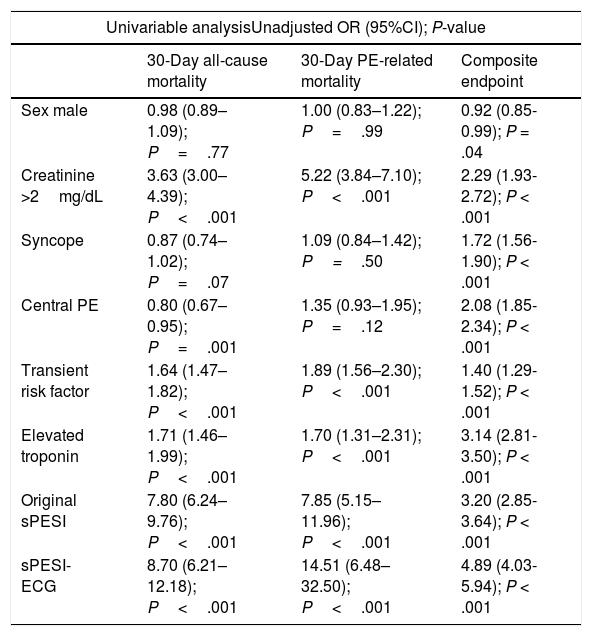
Regression analysesIn univariable analyses, syncope, central PE, transient risk factors, renal dysfunction, and elevated troponin levels were significantly associated with adverse outcomes. For 30-day all-cause mortality, sPESI-ECG yielded an adjusted OR, 10.16 (95%CI, 4.51–22.91), compared with OR, 7.04 (95%CI, 4.36–11.38) for the original sPESI. Similar patterns were observed for 30-day PE-related mortality (adjusted OR, 7.91 vs 4.40) and for the composite endpoint (adjusted OR, 3.39 vs 2.13) (Table 3).
Logistic regression analysis assessing the different strategies in relation to 30-day outcomes (n=32,113).
| Univariable analysisUnadjusted OR (95%CI); P-value | |||
|---|---|---|---|
| 30-Day all-cause mortality | 30-Day PE-related mortality | Composite endpoint | |
| Sex male | 0.98 (0.89–1.09); P=.77 | 1.00 (0.83–1.22); P=.99 | 0.92 (0.85-0.99); P = .04 |
| Creatinine >2mg/dL | 3.63 (3.00–4.39); P<.001 | 5.22 (3.84–7.10); P<.001 | 2.29 (1.93-2.72); P < .001 |
| Syncope | 0.87 (0.74–1.02); P=.07 | 1.09 (0.84–1.42); P=.50 | 1.72 (1.56-1.90); P < .001 |
| Central PE | 0.80 (0.67–0.95); P=.001 | 1.35 (0.93–1.95); P=.12 | 2.08 (1.85-2.34); P < .001 |
| Transient risk factor | 1.64 (1.47–1.82); P<.001 | 1.89 (1.56–2.30); P<.001 | 1.40 (1.29-1.52); P < .001 |
| Elevated troponin | 1.71 (1.46–1.99); P<.001 | 1.70 (1.31–2.31); P<.001 | 3.14 (2.81-3.50); P < .001 |
| Original sPESI | 7.80 (6.24–9.76); P<.001 | 7.85 (5.15–11.96); P<.001 | 3.20 (2.85-3.64); P < .001 |
| sPESI-ECG | 8.70 (6.21–12.18); P<.001 | 14.51 (6.48–32.50); P<.001 | 4.89 (4.03-5.94); P < .001 |
| Multivariable analysis | ||
|---|---|---|
| 30-Day all-cause mortality | ||
| Strategy | Adjusted OR (95%CI) | P value |
| Original sPESIa,b | OR, 7.04 (95%CI, 4.36–11.38) | <.001 |
| sPESI-ECGa,b | OR, 10.16 (95%CI, 4.51–22.91) | <.001 |
| 30-Day PE-related mortality | ||
|---|---|---|
| Original sPESIa,b | OR, 4.40 (95%CI, 2.43–7.97) | <.001 |
| sPESI-ECGa,b | OR, 7.91 (95%CI, 2.51–24.93) | <.001 |
| Composite endpoint | ||
|---|---|---|
| Strategya | Adjusted OR (95%CI) | P value |
| Original sPESIb | 2.13 (1.76–2.58) | <.001 |
| sPESI-ECGb | 3.39 (2.44–4.71) | <.001 |
ECG, electrocardiogram; OR, odds ratio; PE, pulmonary embolism; sPESI, simplified Pulmonary Embolism Severity Index; 95%CI, 95% confidence interval.
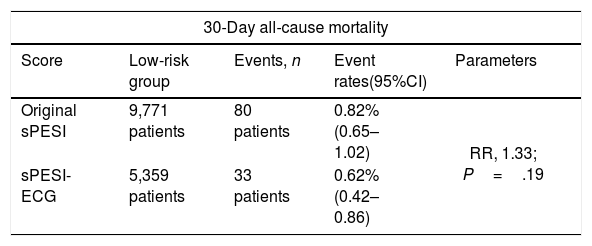
The original sPESI classified 9771 patients (30.4%) as low risk, whereas sPESI-ECG identified a smaller low-risk group of 5359 patients (16.7%). Patients classified as low risk by sPESI-ECG had lower observed event rates. Thirty-day all-cause mortality was 0.62% in the sPESI-ECG low-risk group compared with 0.82% in the original sPESI low-risk group (RR, 1.33; P=.19). Similar reductions were observed for 30-day PE-related mortality (0.11% vs 0.24%; RR, 2.10; P=.14) and for the composite endpoint (2.00% vs 3.33%; RR, 1.67; P<.001) (Table 4).
Comparison of the number of events at 30 days in the low-risk group for each scoring strategy (n=32,113).
| 30-Day all-cause mortality | ||||
|---|---|---|---|---|
| Score | Low-risk group | Events, n | Event rates(95%CI) | Parameters |
| Original sPESI | 9,771 patients | 80 patients | 0.82% (0.65–1.02) | RR, 1.33; P=.19 |
| sPESI-ECG | 5,359 patients | 33 patients | 0.62% (0.42–0.86) | |
| 30-Day PE-related mortality | ||||
|---|---|---|---|---|
| Score | Low-risk group | Events, n | Event rates(95%CI) | Parameters |
| Original sPESI | 9,771 patients | 23 patients | 0.24% (0.15–0.35) | RR, 2.11; P=.14 |
| sPESI-ECG | 5,359 patients | 6 patients | 0.12% (0.04–0.24) | |
| Composite endpoint | ||||
|---|---|---|---|---|
| Score | Low-risk group | Events, n | Event rates(95%CI) | Parameters |
| Original sPESI | 9,771 patients | 326 patients | 3.34% (2.99–3.71) | RR, 1.67; P<.001 |
| sPESI-ECG | 5,359 patients | 107 patients | 2.00% (1.64–2.41) | |
95%CI, 95% confidence interval; ECG, electrocardiogram; PE, pulmonary embolism; RR, relative risk; sPESI, simplified Pulmonary Embolism Severity Index.
ECG abnormality as a composite variable was independently associated with the primary outcome after adjustment for the original sPESI and relevant covariates.
To explore whether specific ECG abnormalities individually accounted for the association between abnormal ECG findings and outcomes, we evaluated each ECG component separately. For 30-day all-cause mortality, nonsinus rhythm, bradycardia, heart rate of 101 to 110 beats/min, and heart rate >110beats/min were significantly associated with the outcome. In contrast, ECG signs typically related to RV overload, including RBBB, S1Q3T3, and negative precordial T waves, were not significantly associated with all-cause mortality, either individually or when combined. For the composite endpoint, however, most ECG components were significantly associated with events, including RBBB, S1Q3T3, and negative precordial T waves. These findings suggest that RV overload patterns on ECG may be more closely related to early clinical deterioration than to all-cause mortality alone. Detailed estimates are shown in Table S2.
When each ECG component was individually added to the original sPESI, none achieved the sensitivity or NPV observed with the composite sPESI-ECG model, nor did any reduce event rates in the low-risk group to the same extent (Table S2). These findings suggest that the prognostic performance of the sPESI-ECG model was not solely explained by the heart rate component.
CT subgroup analysisAmong the 4943 patients with available CT-assessed RV/LV ratio data, 2353 (47.6%) had RV/LV ratio ≥1.0. Baseline characteristics are summarized in Table S3. In this subgroup, strategies incorporating ECG findings and/or RV/LV ratio ≥1.0 showed progressively higher sensitivity and negative predictive value for 30-day all-cause mortality and the composite endpoint, with a corresponding decrease in specificity.
For 30-day all-cause mortality, the original sPESI and sPESI-ECG showed similar discriminative ability, with a C statistic of 0.73. The addition of CT-assessed RV/LV ratio ≥1.0 yielded no meaningful improvement in discrimination, with C statistics of 0.71 (95%CI, 0.67–0.74) when added to the original sPESI and 0.70 (95%CI, 0.66–0.73) when added to the sPESI-ECG model. Discrimination for the composite endpoint was modest for clinical scores alone, with a C statistic of 0.62 (95%CI, 0.59–0.64) for both the original sPESI and sPESI-ECG, and increased slightly with the addition of CT-assessed RV/LV ratio ≥1.0, with a C statistic of 0.66 for both original sPESI and sPESI-ECG.
Event rates in the low-risk groups decreased stepwise with the addition of ECG findings and RV/LV ratio ≥1.0, supporting the incremental prognostic value of these variables in terms of risk reclassification rather than overall discrimination. Across all evaluated strategies, sPESI-ECG showed the strongest independent association with 30-day all-cause mortality and the composite endpoint in multivariable models, with adjusted ORs of 13.57 and 2.33, respectively (Tables S4–S6).
DiscussionECG is a noninvasive, inexpensive, and widely available diagnostic tool that is routinely obtained during the initial evaluation of patients presenting with dyspnea or chest pain. Unlike prior investigations that focused primarily on isolated ECG markers of RV dysfunction, often associated with modest effect sizes and limited clinical applicability [14,15], the present study emphasizes the prognostic relevance of a normal ECG as a marker for identifying patients at very low short-term risk after PE [9].
In this large, real-world cohort of more than 30,000 hemodynamically stable patients with acute PE, ECG abnormalities were common and consistently associated with adverse short-term outcomes, including overall and PE-related mortality, as well as the composite endpoint. The incorporation of ECG findings into sPESI modestly increased sensitivity and NPV, particularly for the composite endpoint, while reducing specificity. Thus, the main potential value of sPESI-ECG appears to lie in identifying a smaller, very low-risk subgroup rather than in improving overall discrimination. Compared with the original sPESI, patients classified as low risk by sPESI-ECG had numerically lower rates of all-cause and PE-related mortality, although these differences did not reach statistical significance. For the composite endpoint, event rates were significantly lower among patients classified as low risk by sPESI-ECG. These findings suggest that ECG incorporation may help refine low-risk classification but should not be interpreted as evidence of improved clinical outcomes or as a substitute for prospective validation.
In the prespecified subgroup of patients with available CT-assessed RV/LV ratio data, findings were directionally consistent with those of the overall cohort. The addition of CT-assessed RV/LV ratio did not meaningfully improve discrimination for mortality and produced only modest gains for the composite endpoint. These results support the interpretation that the incremental value of sPESI-ECG is mainly related to low-risk reclassification rather than overall model performance. However, ECG should not be considered a substitute for RV dysfunction assessment, and additional tools remain necessary for comprehensive risk stratification in patients who are not classified as very low risk. Moreover, the wide confidence intervals observed in this subgroup reflect limited precision and warrant cautious interpretation.
Interestingly, RBBB, S1Q3T3, and negative precordial T waves were not associated with all-cause mortality but were associated with the composite endpoint, which included early hemodynamic deterioration. This finding is consistent with conflicting evidence on the prognostic value of isolated ECG patterns in PE [6,7] and with serial ECG studies showing that persistent RV strain patterns were associated with 30-day mortality mainly in hemodynamically unstable, but not stable, patients [18].
Importantly, our results should be interpreted primarily in the context of identifying a very low-risk profile, rather than as a mechanistic model of ECG abnormalities in PE. The observed performance of sPESI-ECG was not solely explained by the heart rate component, as individual ECG components did not reproduce the performance of the composite ECG variable. This suggests that the dichotomous classification of ECG as normal vs abnormal may capture a broader representation of hemodynamic status and cardiopulmonary reserve than isolated parameters. However, this composite ECG definition includes heterogeneous abnormalities and should not be interpreted as reflecting a single pathophysiological mechanism. Because heart rate is included in both ECG assessment and the original sPESI framework, sPESI-ECG should be interpreted as a modified reclassification strategy rather than as a direct additive improvement over the validated sPESI score [19].
From a clinical perspective, ECG is a pragmatic and widely available tool that may complement existing risk stratification strategies. It requires no additional cost, is rapidly available at the bedside, and may help support early risk assessment, particularly in resource-limited settings where advanced imaging or biomarker testing is not readily available [20–22].
Several limitations should be acknowledged. Although data in the RIETE registry were prospectively collected, the present analysis was retrospective. Approximately 23% of otherwise eligible patients were excluded because ECG data were unavailable, which may have introduced selection bias. To explore this issue, we compared baseline characteristics and outcomes between patients with and without available ECG data (Table S7). Patients without ECG data differed in several baseline characteristics, including a higher prevalence of cancer and a lower prevalence of some markers of PE severity. Because ECG status was the exposure of interest, a formal sensitivity analysis of the sPESI-ECG model in patients without ECG data was not feasible; therefore, these findings should be interpreted with caution. Moreover, the RIETE registry lacks prior ECGs, and we could not determine whether abnormalities such as RBBB or rhythm disturbances were new or preexisting. Similarly, the registry records only the presence or absence of negative T waves in precordial leads, without specifying the affected leads. CT-assessed RV/LV ratio was available in a minority of patients, limiting the generalizability of subgroup findings. Additionally, discharge decisions are influenced by factors not captured in the registry, including bleeding risk, social context, and patient preferences. Finally, as with all registry-based studies, selection and survivor bias cannot be excluded [23,24].
In conclusion, in this large prospective cohort of hemodynamically stable patients with acute symptomatic PE, ECG abnormalities were common and independently associated with adverse short-term outcomes. Incorporating ECG findings into sPESI may help identify a smaller subgroup of patients with very low short-term event rates and could be considered a complementary tool for early risk assessment. Prospective validation is required before this strategy can be used to guide early discharge decisions.
Principal investigatorManuel Monreal.
RIETE Steering Committee Members: Paolo Prandoni, Benjamin Brenner, and Dominique Farge-Bancel.
RIETE National Coordinators: Raquel Barba (Spain), Peter Verhamme (Belgium), Hugo Hyung Bok Yoo (Brazil), Radovan Malý (Czech Republic), Laurent Bertoletti (France), Sebastian Schellong (Germany), Inna Tzoran (Israel), Pierpaolo Di Micco (Italy), Abilio Reis (Portugal), Marijan Bosevski (Republic of North Macedonia), Lucia Mazzolai (Switzerland), Joseph A. Caprini (United States), and My Hanh Bui (Vietnam).
RIETE Registry Coordinating Center: S&H Medical Science Service.
Declaration of generative AI and AI-assisted technologies in the writing processThe authors declare that no artificial intelligence tools were used in the preparation of this manuscript.
FundingNone declared.
Conflicts of interestCMO has received speaker fees from the pharmaceutical companies ROVI and Leo Pharma. PDR has received speaker fees from the following pharmaceutical companies: ROVI, Bayer, Techdow, Menarini, Leo Pharma, Pfizer, Bristol-Myers, Sanofi, and Daiichi-Sankyo. In addition, he has engaged in advisory consultancy work for Techdow, Leo Pharma, and Pfizer. FGV has received speaker honoraria from the following pharmaceutical companies: ROVI, Techdow, Pfizer, Bristol-Myers, and Daiichi-Sankyo. The remaining authors declared no conflicts of interest whatsoever.
We express our gratitude to ROVI for supporting this registry with an unrestricted educational grant. We also thank the RIETE Registry Coordinating Center, S&H Medical Science Service, for quality control of the data and logistic and administrative support.
SPAIN: Abad-Fernández A, Adarraga MD, Agudo-de Blas P, Aibar J, Alberich-Conesa A, Alda A, Alfonso J, Álvarez-Albarrán J, Amado C, Angelina-García M, Arcelus JI, Ballaz A, Barba R, Barbagelata C, Barrón M, Barrón-Andrés B, Beddar-Chaib F, Blanco-Molina Á, Chamorro N, Chasco L, Claver G, Crecente-Otero P, Creu-Paris J, Criado J, De Juana-Izquierdo C, Del Molino F, Del Toro J, Delgado-Casado N, Demelo-Rodríguez P, Díaz-Pedroche MC, Díaz-Peromingo JA, Dubois-Silva Á, Durán D, Escribano JC, Fernández-Martínez de Septién C, Fernández-Morales M, Ferreiro-Celeiro J, Fidalgo Á, Formica A, Francisco I, Fuentes-Spínola MF, Gabara C, Galeano-Valle F, García-Ortega A, García-Bragado F, Gavín-Sebastián O, Gil-Díaz A, Girona E, Gómez-Cuervo C, González-Munera A, Gorostidi-Pérez J, Gorostidi-Álvarez I, Guirado L, Gutiérrez-Guisado J, Hernández-Blasco L, Hernández-Borge J, Jiménez D, Jou I, Joya MD, Lalueza A, Larrauri A, Llamas P, López-Brull H, López-Jiménez L, López-Miguel P, López-Núñez JJ, López-Ruiz A, López-Sáez JB, Lorenzo A, Macedo J, Madridano O, Maestre A, Marchena PJ, Martín-del Pozo M, Mas-Maresma L, Menéndez-Sánchez C, Moisés-Lafuente J, Monreal M, Monzón-Escribano L, Moreno-Casas S, Moreno-Fernández A, Nieto JA, Núñez-Fernández MJ, Olid M, Ordieres-Ortega L, Ortiz M, Osorio J, Otálora S, Padín-Paz EM, Pagán J, Parra-Caballero P, Pedrajas JM, Pérez-Pinar M, Pérez-Ductor C, Peris ML, Pesce ML, Prieto-Gañán LM, Puche G, Rivas A, Rivera-Cívico F, Rodríguez-Cobo A, Ruiz-Artacho P, Ruiz-Giménez N, Ruiz-Torregrosa P, Sánchez-Camacho M, Sancho T, Sendín V, Sidawi-Urbano T, Sierra-Palomares G, Sigüenza P, Sindín-Martín L, Solé A, Suárez-Fernández S, Tascón-Rodríguez R, Terés-Pueyo L, Toda MR, Tolosa C, Trujillo-Santos J, Tudela L, Valle R, Varona JF, Vega-Romero E, Vidal G, Villares P, You JS; AUSTRIA: Ay C, Nopp S, Pabinger I; BELGIUM: Erard M, Verhamme P, Verstraete A; BRAZIL: Rocha AT, Yoo HHB; COLOMBIA: Carbonell SE, Gómez-Mesa JE, Montenegro AC, Roa J; CZECH REPUBLIC: Grenar P, Hirmerova J, Malý R; FRANCE: Accassat S, Benarroch S, Bertoletti L, Bura-Riviere A, Catella J, Chopard R, Couturaud F, Crichi B, Duong R, Espitia O, Le Mao R, Leclercq B, Mahé I, Millet G, Moustafa F, Poenou G, Sarlon-Bartoli G; GERMANY: Schellong S; IRAN: Jenab Y, Khodayari A, Sadeghipour P, Yadangi S; ISRAEL: Brenner B, Dally N, Tzoran I; ITALY: Barillari G, Basaglia M, Bilora F, Bissacco D, Bortoluzzi C, Bortoluzzi M, Brandolin B, Buso G, Casana R, Ciammaichella MM, Di Micco P, Guida A, Imbalzano E, Lambertenghi-Deliliers D, Licci A, Marcon C, Mastroiacovo D, Mazzarelli U, Mumoli N, Pesavento R, Pizzuti V, Poz A, Prandoni P, Scandiuzzi-Piovesan T, Scarinzi P, Siniscalchi C, Vo Hong N, Zalunardo B; LATVIA: Kigitovica D, Skride A, Zicans M; MEXICO: Flores-Ramírez C, Mendoza Romo-Ramírez MÁ, Tarín-Recéndez D; PORTUGAL: Fonseca S, Martins MD, Pereira-Fontes C, Soeiro B; REPUBLIC OF NORTH MACEDONIA: Bosevski M, Geceska M, Zdraveska M; SWITZERLAND: Barco S, Mazzolai L; UNITED STATES: Angiolillo DJ, Caprini JA, Ortega-Paz L, Tafur AJ; and VIETNAM: Bui MH, Nguyen ST, Pham KQ, Tran GB.
The following are the supplementary data to this article:










