






This study evaluated the performance of seven POCs, focusing on FiO2, bolus triggering delay, synchronization, and technical specifications, including weight, size, noise level, and battery autonomy.
MethodsA bench study was conducted using a mechanical lung model (ASL 5000) equipped with a Fast Oxygen Measurement sensor. Seven devices available on the European market were tested: FreeStyle Comfort, iGo2, Inogen One G4, Inogen One G5, Platinum Mobile, Zen-O lite, and Horizon P5. 200 ventilatory cycles were simulated per device across various respiratory rates (RR). Measurements included FiO2, bolus triggering delay, synchronization, and bolus volume. Technical specifications were also compared. All devices were tested across their full range of settings, with each test replicated on a second device to confirm results within a 10% margin of error.
ResultsSignificant differences in FiO2 delivery were observed (p<0.001), with all devices delivering at least 28% FiO2 at their lowest settings. The Inogen One G5 and Horizon P5 achieved the highest FiO2 levels (48.7% [38.4–56.9%] and 47.8% [35.6–56.4%], respectively). Synchronization was high across devices but declined at extreme RR (15 and 40bpm). FiO2 variations were influenced by RR, while bolus delays depended on device type and RR. Technical specifications varied widely across devices.
ConclusionsPOCs demonstrate notable differences in performance, with RR and device type impacting FiO2 delivery and synchronization. These findings may help support more informed device selection according to the intended conditions of use and patient requirements.

Long-term oxygen therapy (LTOT) is an established treatment in patients with severe hypoxemic respiratory failure [1]. The goals of LTOT are to improve quality of life and exercise performance, as well as to reduce morbidity [1,2]. The current recommendation is to use LTOT at least 15h/d. The prolonged use of oxygen supplementation requires patients to remain connected to an oxygen source for extended periods, which significantly interferes with daily activities and restricts mobility. The past two decades have seen the development of miniaturized systems capable of delivering ambulatory oxygen and improving patient autonomy [3]. These devices, known as portable oxygen concentrators (POCs), concentrate atmospheric oxygen, serving as autonomous oxygen sources and providing a portable solution for ambulatory patients. There are two types of POCs, those that can only operate in the pulse dose and those capable of operating in both pulse mode and continuous mode.
Compared to conventional oxygen delivery systems, modern lightweight pulse dose devices offer significant advantages. By delivering oxygen boluses, they minimize atmospheric oxygen loss, unlike continuous flow systems, allowing for lighter and more autonomous devices. These characteristics are particularly beneficial for patients seeking to maintain an active lifestyle, including activities such as work, shopping, or travel. Moreover, ambulatory oxygen can improve exercise tolerance and relieve exertional dyspnea in selected patients with exercise-induced desaturation, although benefits are inconsistent across studies [4–7].
Although some clinical studies suggest that pulse oxygen delivery is equivalent to continuous flow systems [8,9], others have demonstrated superiority of continuous flow. Furthermore, given the diversity of pulse oxygen delivery systems currently available on the market, each with distinct technical designs, their intrinsic performances are likely to vary significantly [3,10,11].
To address this variability, we conducted a pragmatic bench study comparing seven POCs. The evaluation encompassed both performance metrics, such as FiO2 and bolus volumes, and technical features, such as weight, size, noise level, and battery autonomy. This comprehensive approach reflects our belief that all these factors are critical for making an informed choice of the most suitable POC for a given patient.
Our primary goal was to evaluate the performance of seven POCs in terms of the delivered oxygen fraction (FiO2). Secondary objectives included assessing their performance regarding bolus triggering delay and the volume of delivered boluses to better understand how these variables influence FiO2. Additionally, we compared the devices based on battery autonomy, noise level, and other technical characteristics.
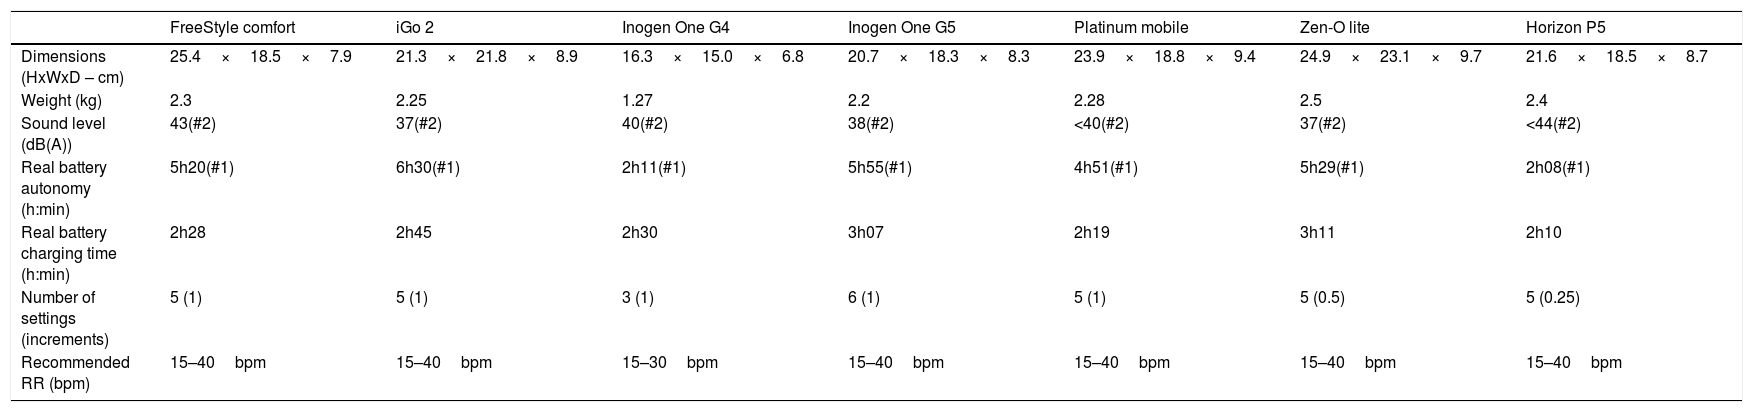
MethodsSeven devices were assessed following standardized conditions (see below): FreeStyle Comfort™ (Caire, Ball Ground, Georgia, USA), iGo2™ (Devilbiss Healthcare, Port Washington, New York, USA), Inogen One G4, ™ Inogen One G5™ (Inogen, Goleta, California, USA), Platinum Mobile™ (Invacare, Elyria, Ohio, USA), Zen-O lite (GCE Medical, Turmstrasse, Switzerland) and Horizon P5™ (Scaleo Medical, Montpellier, France). All devices were warmed-up before starting simulations according to the user manual provided by the manufacturer, and each device was systematically tested across its full range of settings (generally 1–5), excluding intermediate increments (see Table 1).
Characteristics of the seven portable devices studied.
| FreeStyle comfort | iGo 2 | Inogen One G4 | Inogen One G5 | Platinum mobile | Zen-O lite | Horizon P5 | |
|---|---|---|---|---|---|---|---|
| Dimensions (HxWxD – cm) | 25.4×18.5×7.9 | 21.3×21.8×8.9 | 16.3×15.0×6.8 | 20.7×18.3×8.3 | 23.9×18.8×9.4 | 24.9×23.1×9.7 | 21.6×18.5×8.7 |
| Weight (kg) | 2.3 | 2.25 | 1.27 | 2.2 | 2.28 | 2.5 | 2.4 |
| Sound level (dB(A)) | 43(#2) | 37(#2) | 40(#2) | 38(#2) | <40(#2) | 37(#2) | <44(#2) |
| Real battery autonomy (h:min) | 5h20(#1) | 6h30(#1) | 2h11(#1) | 5h55(#1) | 4h51(#1) | 5h29(#1) | 2h08(#1) |
| Real battery charging time (h:min) | 2h28 | 2h45 | 2h30 | 3h07 | 2h19 | 3h11 | 2h10 |
| Number of settings (increments) | 5 (1) | 5 (1) | 3 (1) | 6 (1) | 5 (1) | 5 (0.5) | 5 (0.25) |
| Recommended RR (bpm) | 15–40bpm | 15–40bpm | 15–30bpm | 15–40bpm | 15–40bpm | 15–40bpm | 15–40bpm |
Battery autonomy tests were carried out at setting “1” (i.e. minimum bolus setting). # indicates the setting corresponding to the measured value. Actual battery autonomy was measured in our laboratory. The Zen-O Lite and Horizon P5 offer 9 and 20 setting increments, respectively, yet both cover the same range: levels 1–5. All measurements were conducted in the laboratory and were not taken from the devices’ user manuals.
The tests were performed using a mechanical lung model (ASL5000, IngMar Medical, Pittsburgh, PA, USA) equipped with a Fast Oxygen Measurement (FOM) sensor to measure FiO2 of the simulated patient. The sensor had a response time below 350ms. The lung model was characterized by a resistance (R) set at 5cmH2OsL−1 and a compliance set at 50mL/cmH2O, and an uncompensated residual capacity of 200ml. The occlusion pressure (P0.1) was set at 1cmH2O and the following respiratory rates (RR) were assessed: 15, 20, 30 and 40 breaths per minute (bpm). Each POC was interfaced with the ASL 5000 using a 1.80m oxygen tubing connected to a T-piece positioned at the inlet of the mechanical lung. The distal end of the T-piece was occluded, and a calibrated 4mm leak was added to reproduce the intentional leak that occurs between nasal cannulas and the patient's nares. Although the setup did not include an anatomical upper airway model, it reproduced open-interface nasal oxygen delivery conditions (Fig. 1). Fifty ventilatory cycles were simulated and analyzed for each RR. Therefore we simulated 200 ventilatory cycles in total for each setting, on each device. Details of the respiratory modalities used at each respiratory rate are provided in e-Table 1.

To validate the outcomes of our study, we conducted a replication of the experiment using a second identical concentrator, setting it to both minimum and maximum bolus settings for each device. We then compared the recorded values with values obtained from the first concentrator. We established a 10% margin of error as the threshold for validating each test indicator.
Main outcomes of interest- •
The average inspired fraction of oxygen (FiO2), expressed as a percentage (%) received by the lung model – representing the patient under simulated conditions – was reported as well as the average bolus volume delivered in ml and equivalent flow in L/min.
- •
The average bolus triggering delay, reported in milliseconds (ms), was also calculated. Bolus triggering delay was defined as the time interval between the onset of the inspiratory effort generated by the mechanical lung model and the onset of oxygen bolus delivery by the POC. This value was calculated for each respiratory cycle and then averaged for each condition tested.
- •
The synchronization between the lung model and the concentrator was assessed and reported in terms of percentage (%) of boluses correctly triggered. Two types of asynchronies were identified: non-triggered boluses (patient efforts not detected by the device) and auto-triggered boluses (boluses delivered without a patient effort). An asynchrony level (AL) was defined as the ratio between the number of asynchronous boluses and the total number of respiratory events, as follows: AL=(non-triggered boluses+auto-triggered boluses)/(mechanical lung respiratory cycles+auto-triggered boluses). The synchronization rate was then calculated as: 1−AL, and expressed in percentage. A synchronization rate of 100% therefore indicated that all patient efforts triggered a bolus and that no auto-triggered bolus occurred.
- •
Weight, dimension, measured battery autonomy and charging time were also retrieved. Battery autonomy was assessed at setting 1 under a respiratory rate of 15breaths/min using a pressure trigger to activate pulse delivery, until complete device shutdown. Charging time was measured as the time required to recharge the device from complete battery depletion to 100% battery level.
Continuous variables are presented as medians with interquartile ranges. The Shapiro–Wilk test was used to assess the non-normality of the data. For each experimental condition, defined by the combination of device, setting, and respiratory rate, the 50 simulated respiratory cycles were first aggregated by calculating the mean value of the outcome of interest. The unit of analysis for inferential statistics was the aggregated experimental condition. Comparisons across multiple groups were performed using the Kruskal–Wallis test, followed by Dunn's post hoc test for pairwise comparisons when appropriate. A p-value<0.05 was considered statistically significant.
ResultsThe tests were conducted in collaboration between ANTADIR and KerNel Biomedical from 2018 to 2024, as part of the technical evaluation of new pulse oxygenation devices on the market. Following the validation test, all measurements remained within the 10% error margin, confirming the reliability of our results. The intraclass correlation coefficient between the two experiments for the FiO2 assessment was 0.96, indicating an excellent level of agreement. Table 1 summarizes the main characteristics of the seven tested devices. Weight, sound level, measured battery autonomy and charging time are also presented for each device in E-Fig. 1.
Delivered FiO2The FiO2 delivered by POCs varied significantly between devices (p<0.001), with some achieving higher oxygen fractions than others. However, all POCs delivered a minimum FiO2 of at least 28% at their lowest settings (Fig. 2). The Inogen One G5 and Horizon P5 demonstrated the highest FiO2 levels, at 48.7% [38.4–56.9%] and 47.8% [35.6–56.4%], respectively, with no statistically significant difference between them. Across all devices, the FiO2 increased with higher respiratory rates (RR) and decreased as RR declined (e-Table 2). Detailed FiO2 according to device settings and respiratory rates are available in the online supplement (e-Fig. 2). While the variations in FiO2 were statistically significant, they were more strongly influenced by the ‘respiratory rate effect’ than the ‘device effect’ (E-Table 2 and E-Fig. 2).
Time to triggering
Statistically significant differences were observed between the devices in terms of bolus triggering delay (p<0.001). The Platinum Mobile exhibited the shortest triggering delay, with a median of 83ms [65–130ms], and was the only device to consistently remain below the 200ms threshold (Fig. 3). In contrast, the FreeStyle Comfort, Inogen One G5, and Zen-O lite showed greater variability depending on respiratory rates, with median delays of 183ms [138–272ms], 184ms [141–259ms], and 181ms [169–222ms], respectively. Triggering times across respiratory rates are detailed in E-Fig. 3, which highlights the influence of both device and respiratory rate on triggering delays.
Bolus volume and flow patterns
Although bolus volumes were not statistically different across devices (Fig. 4), qualitative analysis revealed notable variations in the flow shapes of boluses (Fig. 5). For instance, with the iGO2, the flow shape was broader at a respiratory rate of 15bpm compared to 40bpm. Similarly, the Zen-O lite exhibited delayed peak flow at 40bpm. These findings suggest that the interaction between device mechanics and respiratory rate plays a critical role in oxygen delivery dynamics, even when total bolus volumes are comparable, as shown in e-Fig. 4.
Synchronization rate

The synchronization rates across all seven devices did not show statistically significant differences (p=0.12, Fig. 6). At a respiratory rate of 15bpm, the Inogen One G4 had the lowest synchronization rate at 91±7%, primarily due to auto-triggering events. When the respiratory rate increased to 40bpm, synchronization rates for the Zen-O lite and FreeStyle Comfort dropped to 84±4% and 86±29%, respectively. For the Zen-O lite, the primary issue at 40bpm was a high incidence of non-triggered boluses. At the maximum setting (#5) and a respiratory rate of 40bpm, the FreeStyle Comfort's synchronization rate fell below 50%, with non-triggered cycles leading to missed boluses in 66% of cases. Detailed data on bolus synchronization rates by device type, respiratory rate, and setting are provided in E-Table 3.
Discussion
This bench study demonstrated substantial inter-device variability in FiO2 delivery, triggering delays, and synchronization among POCs under standardized conditions. Respiratory rate emerged as a determinant of performance, influencing FiO2 delivery, bolus triggering delays, and synchronization rates. Although bolus volume did not differ statistically between devices, bolus flow profiles varied across devices and respiratory rates, potentially influencing FiO2 delivery.
Pulsed oxygen delivery, as provided by POCs, enhances device autonomy but typically delivers lower FiO2 levels compared to continuous flow systems, particularly at higher respiratory rates [12]. Chen et al. [11] demonstrated that continuous flow systems outperformed POCs in FiO2 delivery. Additionally, actual FiO2 values were influenced by device type, settings, breathing patterns. The same team reported FiO2 values for pulsed systems ranging from 25% to 45%, consistent with our findings [12]. However, they employed validated anatomical replicas and varied tidal volumes, which were not included in our study. The bench settings used in the present study were initially designed to challenge device triggering under standardized conditions across a wide range of respiratory rates and inspiratory efforts. Consequently, the generated tidal volumes (E-Table 1) were lower than those reported by Chen et al. [12] and those typically observed in patients, potentially leading to FiO2 overestimation compared with real-life conditions. Although this standardized approach improves device-to-device comparability, it does not fully reflect the complexity of real-life respiratory mechanics and interface-related conditions. Therefore, these findings should primarily be interpreted as comparative technical performance data rather than direct indicators of clinical effectiveness.
In addition, under extreme conditions, such as simulated high altitudes, POC performance in terms of FiO2 is also highly variable [13]. This variability is particularly critical for patients with hypoxemic respiratory conditions traveling on long-haul flights, where POCs are often the only approved devices [13]. These findings align with our results and emphasize the variability in performance observed across different device types and respiratory conditions. These observations are also consistent with the broader bench literature on oxygen-delivery systems, which has repeatedly highlighted that device-specific characteristics may influence the effective gas flow and delivered FiO2[14–16].
Despite delivering lower FiO2 levels, POCs are often preferred by patients [17]. A crossover trial involving 25 COPD patients on LTOT demonstrated a preference for portable systems in daily life [18]. In this study, 43% of patients favored portable systems, likely due to their contribution to mobility, which is essential for maintaining a minimum level of physical activity. Khor et al. compared two POCs with a compressed oxygen cylinder during six-minute walk tests (6MWT) in patients with interstitial lung diseases. Their results showed no significant differences in nadir oxygen saturation between the devices (Inogen One G2: 82.3% vs. cylinder: 80.3%; EverGo: 85.7% vs. cylinder: 86.1%), while patient preferences leaned toward POCs due to portability and ease of use [19]. However, performance on the 6MWT was comparable across devices, reinforcing the viability of POCs in clinical practice. Similar findings were previously reported by Strickland et al. [20].
Ambulatory oxygen therapy is essential not only for maintaining a sufficient level of oxygen in the blood or alleviating dyspnea but also for enabling daily activities and reducing sedentary lifestyles [21,22]. Patients frequently prefer portable systems due to their lightweight and compact design, which facilitates leaving the home, working, and traveling [20,21]. Selecting an appropriate device requires balancing factors such as weight, autonomy, and FiO2 delivery performance, aligned with the patient's characteristics and preferences. Similar to non-invasive ventilation or continuous positive airway pressure therapy, if a patient is unable to effectively use the device (comfort, perception of others, etc.) the therapy becomes ineffective [19–21]. Factors such as device noise or bulkiness (E-Fig. 1), which might attract unwanted attention, could discourage participation in daily activities [23].
ConclusionTwo decades ago, only a limited number of portable oxygen concentrators were available, whereas a wide range of devices is now accessible on the European market. This bench study demonstrates substantial inter-device variability in terms of technical performances, under standardized conditions. These findings may help support more informed device selection according to the intended conditions of use and patient requirements.
Author contributionsLiterature search: ML, EF, MP, CR; Study concept and design: ML, EF, JD, MP, CR; Acquisition of data: ML, EF; Analysis and interpretation of data: ML, EF, MP, CR; Statistical analysis: LM, EF; Drafting of the manuscript: ML, EF; Critical revision of the manuscript for important intellectual content: ML, EF, JD, MP, CR.
ML had full access to all the data in the study and takes responsibility for the integrity of the data and the accuracy of the data analysis.
AI use disclosureThe authors declare that no artificial intelligence tools were used to draft the manuscript or to process the data.
FundingThis work has been funded by Fédération Antadir.
Conflict of interestML is a part-time employee of Air Liquide Medical Systems in a non-commercial role; this work was carried out outside the time allocated to his duties at Air Liquide Medical Systems. CR reports consulting fees from Resmed, Philips, Lowenstein and Air Liquide Medical Systems and lecturing fees from Philips, Lowenstein, Fischer & Paykel, Inogen outside the submitted work. MP reports lecturing fees from Philips, Resmed, SOS oxygen, Chiesi, Lowenstein, Bastide Medical, Elivie, Asten Santé, Air liquide Medical Systems, Antadir, jazz Pharmaceutical, Fisher & Paykel,Orkyn and Sanofi, grants from Resmed, Fisher & Paykel and Asten santé, Consulting fees from Philips Respironics, Resmed, Asten Santé, Air Liquide Medical Systems, Yuwell and GSK, outside of the submitted work.
The followings are the supplementary data tot his article:









