






To characterise long-term mask-type trajectories among patients receiving continuous positive airway pressure (CPAP) and assess their associations with CPAP nonadherence and treatment termination.
MethodsThis real-world longitudinal cohort study included newly diagnosed adults treated with CPAP for more than 1 month. Patients had unrestricted access to 48 models across 4 mask types: nasal masks (NMs), oronasal masks (ONMs), and nasal-pillow masks (NPMs), with the latter subdivided into nasal-cradle masks (NCMs) and intranasal masks (INMs). Sequence analysis was used to identify mask trajectories, and multivariable models were used to estimate odds ratios (ORs) for CPAP nonadherence and treatment termination.
ResultsAmong 4675 patients, the median duration of CPAP treatment was 1.5 years (IQR, 0.7–2.8 years); 21.8% were nonadherent, and 26.1% terminated treatment. Adherent patients changed mask type less frequently than nonadherent patients and those who terminated treatment (43.7% vs 50.4% and 53.8%, respectively; p<.001). NM use decreased from 72.3% to 43.1%, whereas ONM use increased from 19.8% to 37.0%, INM use from 2.4% to 6.5%, and NCM use from 5.5% to 13.4%. Fifteen trajectories were identified. Compared with NM renewal, ONM and INM renewal were not associated with a higher risk of nonadherence or treatment termination, whereas NCM renewal was associated with CPAP termination (OR, 1.60; 95%CI, 1.04–2.47; p=.034). Switching from an initial NM to an INM (OR, 1.68; 95%CI, 1.18–2.39; p=.004), NCM (OR, 1.76; 95%CI, 1.26–2.45; p=.001), or ONM (OR, 1.31; 95%CI, 1.01–1.70; p=.046) was associated with CPAP termination.
ConclusionsIn routine clinical practice, NM, ONM, and INM renewal trajectories were comparable, whereas NCM renewal was associated with unfavourable outcomes. Switching from an NM to an ONM or NPM was associated with poorer CPAP use. NCMs and INMs should not be pooled under the general NPM category.
Trial registrationThe SwitchAdene study is registered with the Health Data Hub under registration No. 19334378.

Obstructive sleep apnoea (OSA) is highly prevalent worldwide and remains a major public health challenge, with its burden expected to increase further in the coming decades [1–3]. Continuous positive airway pressure (CPAP) remains a recommended treatment for moderate to severe OSA, with clinical guidelines emphasising structured follow-up and review of objective data to ensure effective treatment and sustained use [4–7]. Because adherence to CPAP improves quality of life and is associated with lower cardiovascular mortality and fewer major adverse cardiovascular events, improving adherence is a primary objective of OSA management [4–6,8,9].
Among the modifiable determinants of CPAP adherence, mask-type selection was identified as a pivotal consideration in the 2020 American Thoracic Society Workshop Report, which synthesised clinical evidence comparing nasal and oronasal masks and emphasised patient involvement in mask selection [10]. In large real-world cohorts, NMs have generally been associated with greater CPAP use and a lower residual apnoea–hypopnoea index (AHI) than ONMs, supporting a nasal-first approach in routine clinical care [4–6,10,11]. NPMs, including NCMs and INMs, appear to perform similarly to NMs in terms of adherence, therapeutic pressure, and residual AHI [12]. However, evidence concerning the more recently introduced NCMs remains limited, and no specific first-line recommendations address their use [4–6].
In contrast to cross-sectional cohort studies, randomised clinical trials have not demonstrated improved adherence with NMs compared with ONMs, despite higher residual AHI values and more leak-related problems with ONMs [4–6,10,11]. There is increasing consensus that mask-type selection should be individualised and integrated into long-term care pathways [4–6,10,13]. Nevertheless, important evidence gaps remain regarding the effects of mask-type changes on long-term CPAP use. Most published studies have evaluated a single mask type only at baseline or over short follow-up periods, thereby failing to capture longitudinal adaptations and switching patterns in real-world practice.
To address these gaps, we analysed a large cohort of patients with OSA receiving CPAP who had unrestricted access to different mask types—nasal, oronasal, nasal-cradle, and intranasal—over a 5-year period. The objectives were to (1) describe long-term mask-type trajectories, (2) identify clusters of mask-switching behaviour, and (3) quantify their associations with CPAP nonadherence and treatment termination.
MethodsStudy design and populationThe SwitchAdene study was a real-world cohort study conducted between October 1, 2018, and April 30, 2023, among newly diagnosed adults receiving CPAP for OSA for at least 1 month.
OSA was defined according to French Social Security criteria as follows: (1) AHI≥30events/h or AHI≥15events/h with more than 10 respiratory effort-related arousals per hour or cardiovascular comorbidities and (2) the presence of at least 3 of the following symptoms: excessive daytime sleepiness, snoring, headache, asthenia, nocturia, or choking or suffocation during sleep.
Groupe Adène, a nonprofit home healthcare provider, delivered care to patients in the Occitanie and Auvergne-Rhône-Alpes regions of France through a network of at least 352 physicians and 53 technicians.
For patients who underwent at least 1 mask change, eligibility required at least 1 month of follow-up after delivery of the final mask. Consequently, all participants had at least 1 month of follow-up with their final mask at the end of the study.
Ethics approval and consent to participateThe SwitchAdene study is registered with the Health Data Hub under registration No. 19334378. All participants provided written informed consent. The study complied with the Declaration of Helsinki and was reviewed and approved by the Institutional Review Board Adene Fonds de dotation on August 8, 2024 (No. IRB_ADENE_20240805).
Data collectionClinical data collected at CPAP initiation included age, sex, body mass index (BMI), and AHI measured using respiratory polygraphy or polysomnography. Data on CPAP and mask use were collected daily throughout the study and included mask type, CPAP use, device-reported AHI (AHI_flow), pressure, and leaks.
Leak data from 4 manufacturers were recorded. To make data expressed in litres per minute or percentages as comparable as possible, a previously validated pooled categorical variable termed “device-reported leaks” was used [14]. The definitions are provided in Table E1.
Patients had unrestricted access to 48 models across 4 mask types: NMs, ONMs, NCMs, and INMs. The characteristics of the masks provided during the study are described in Table E2.
Definitions and proceduresA mask-type switch was defined as a change to a different mask type, whereas mask renewal was defined as provision of a replacement mask of the same type. A change in size, brand, series, or model without a change in mask category was considered a mask renewal.
The protocol for mask initiation, renewal, and switching was as follows. At CPAP initiation, an NM was the preferred first-line option unless otherwise specified by the referring physician. Mask renewals were performed according to the payer-defined protocol during scheduled follow-up visits. At least 4 masks could be provided during the first year after treatment initiation, followed by 2 masks per year thereafter. A mask-type switch could be requested by the physician, patient, or technician but required approval from the prescribing physician.
CPAP adherence was defined as mean CPAP use of at least 4h/d during the final month of observation. CPAP nonadherence was defined as mean CPAP use of less than 4h/d during the final month. In France, the French Social Security system uses a threshold of 4h/d to determine the reimbursement level received by the home healthcare provider.
For patients who did not discontinue CPAP, the final month of CPAP use was April 2023. For patients who discontinued treatment, it was the final month before discontinuation. CPAP termination was defined as discontinuation before the end of follow-up following a patient or physician decision and confirmed by termination of payer coverage.
AHI_flow was defined as the number of apnoea and hypopnoea events per hour reported by the CPAP device. First-month AHI_flow, CPAP use in hours per day, pressure, and leak variables were calculated from a maximum of 1 month of data. Shorter periods were used for patients who changed mask type during the first month of treatment.
Patients with missing telemonitoring or covariate data were excluded. The only variable with missing data was mean pressure during the first month, measured in cm H2O, for which 1.1% of observations were missing.
Statistical analysesContinuous variables are presented as medians and IQRs because of their non-Gaussian distributions. Categorical variables are presented as numbers and percentages.
Sequence analysis was performed to classify mask-type trajectories, as described in Method E1. Patient characteristics were compared according to CPAP adherence status, CPAP nonadherence, CPAP termination, initial mask type, and mask-type sequence group. The Kruskal–Wallis test was used for quantitative variables, and the χ2 test or Fisher exact test was used for categorical variables.
When an overall comparison was statistically significant, pairwise comparisons were performed using false discovery rate correction.
Univariate and multivariable regression analyses were performed to investigate associations of patient characteristics and mask-type sequence groups with CPAP adherence, CPAP nonadherence, and treatment termination, as detailed in Method E1. All statistical analyses were performed using R, version 4.3.1.
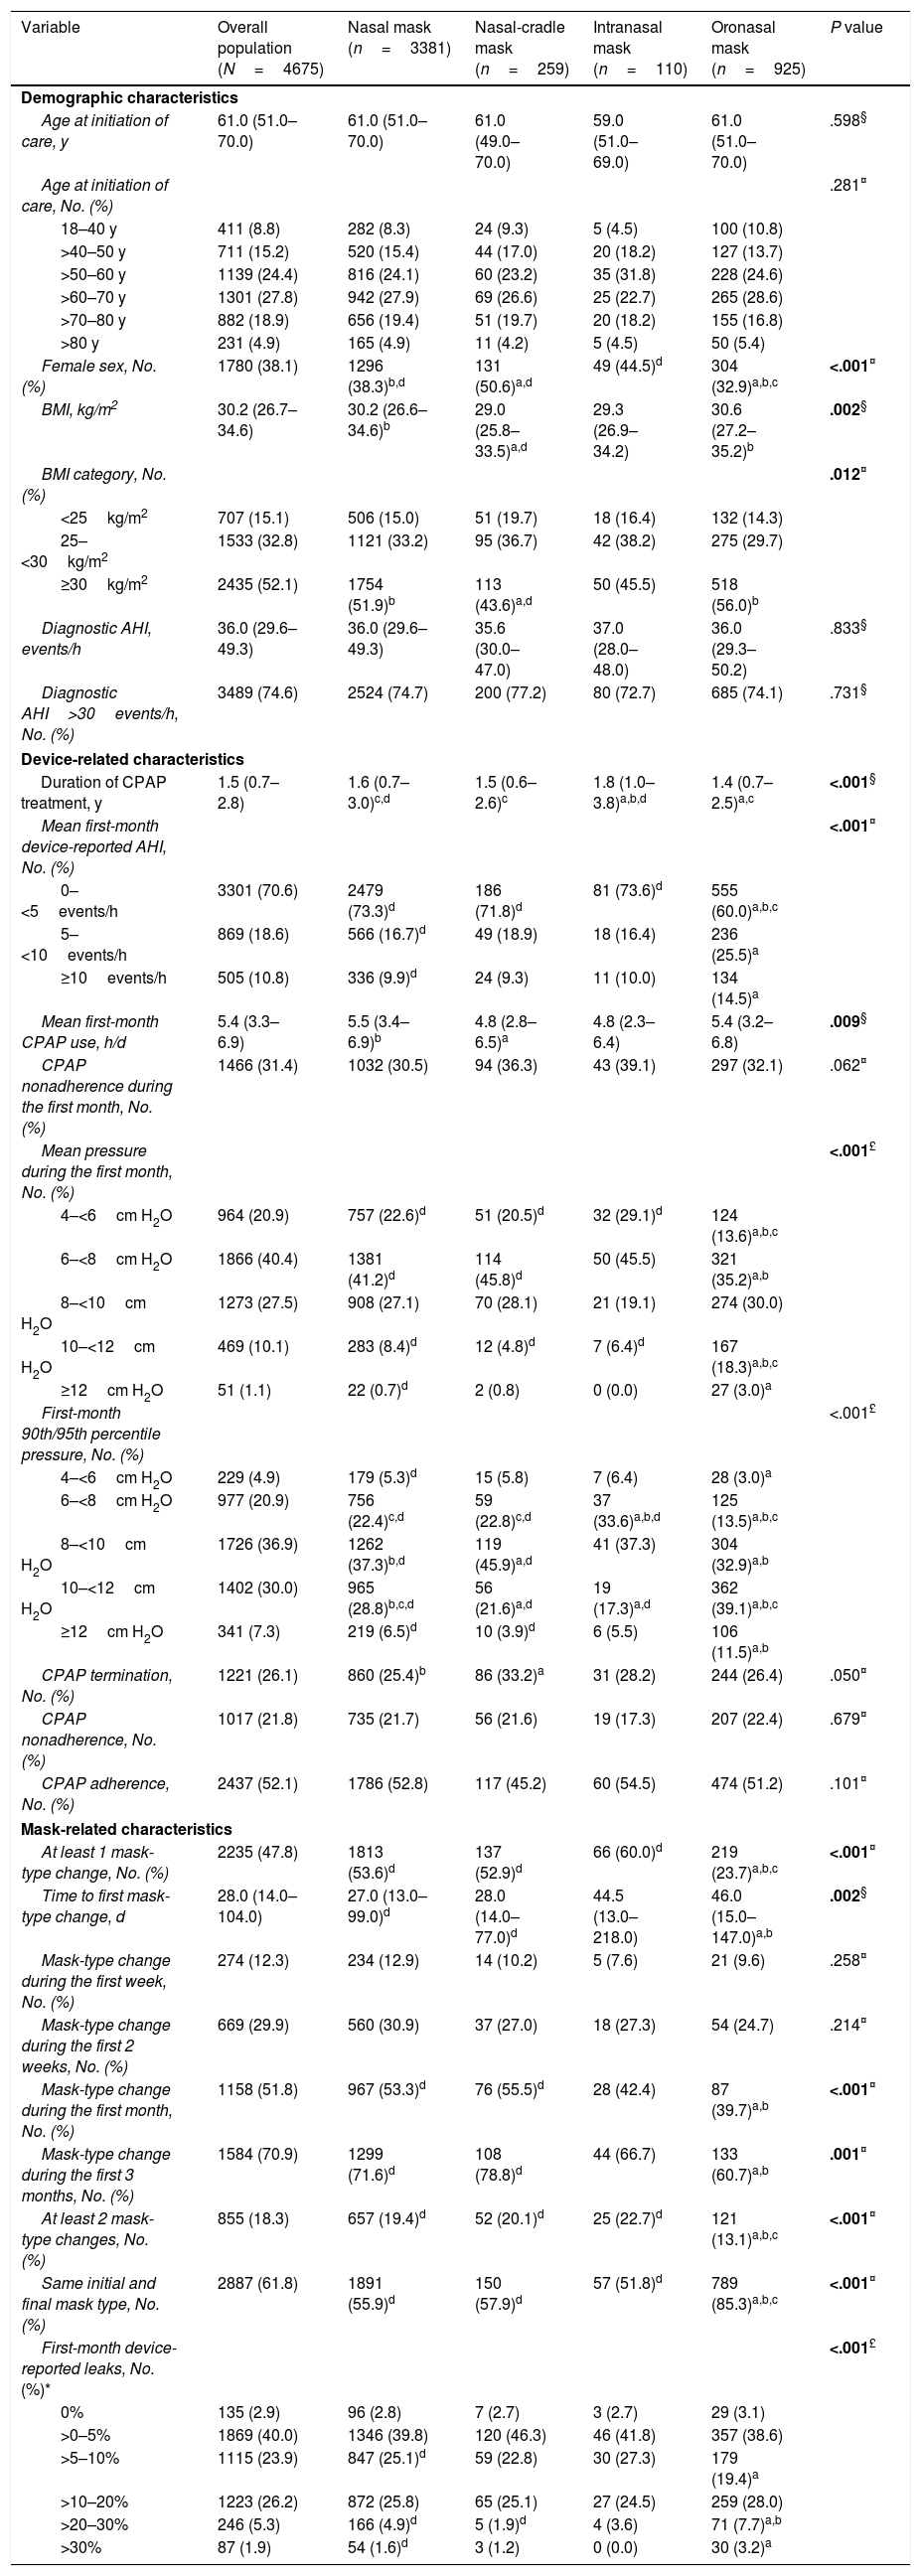
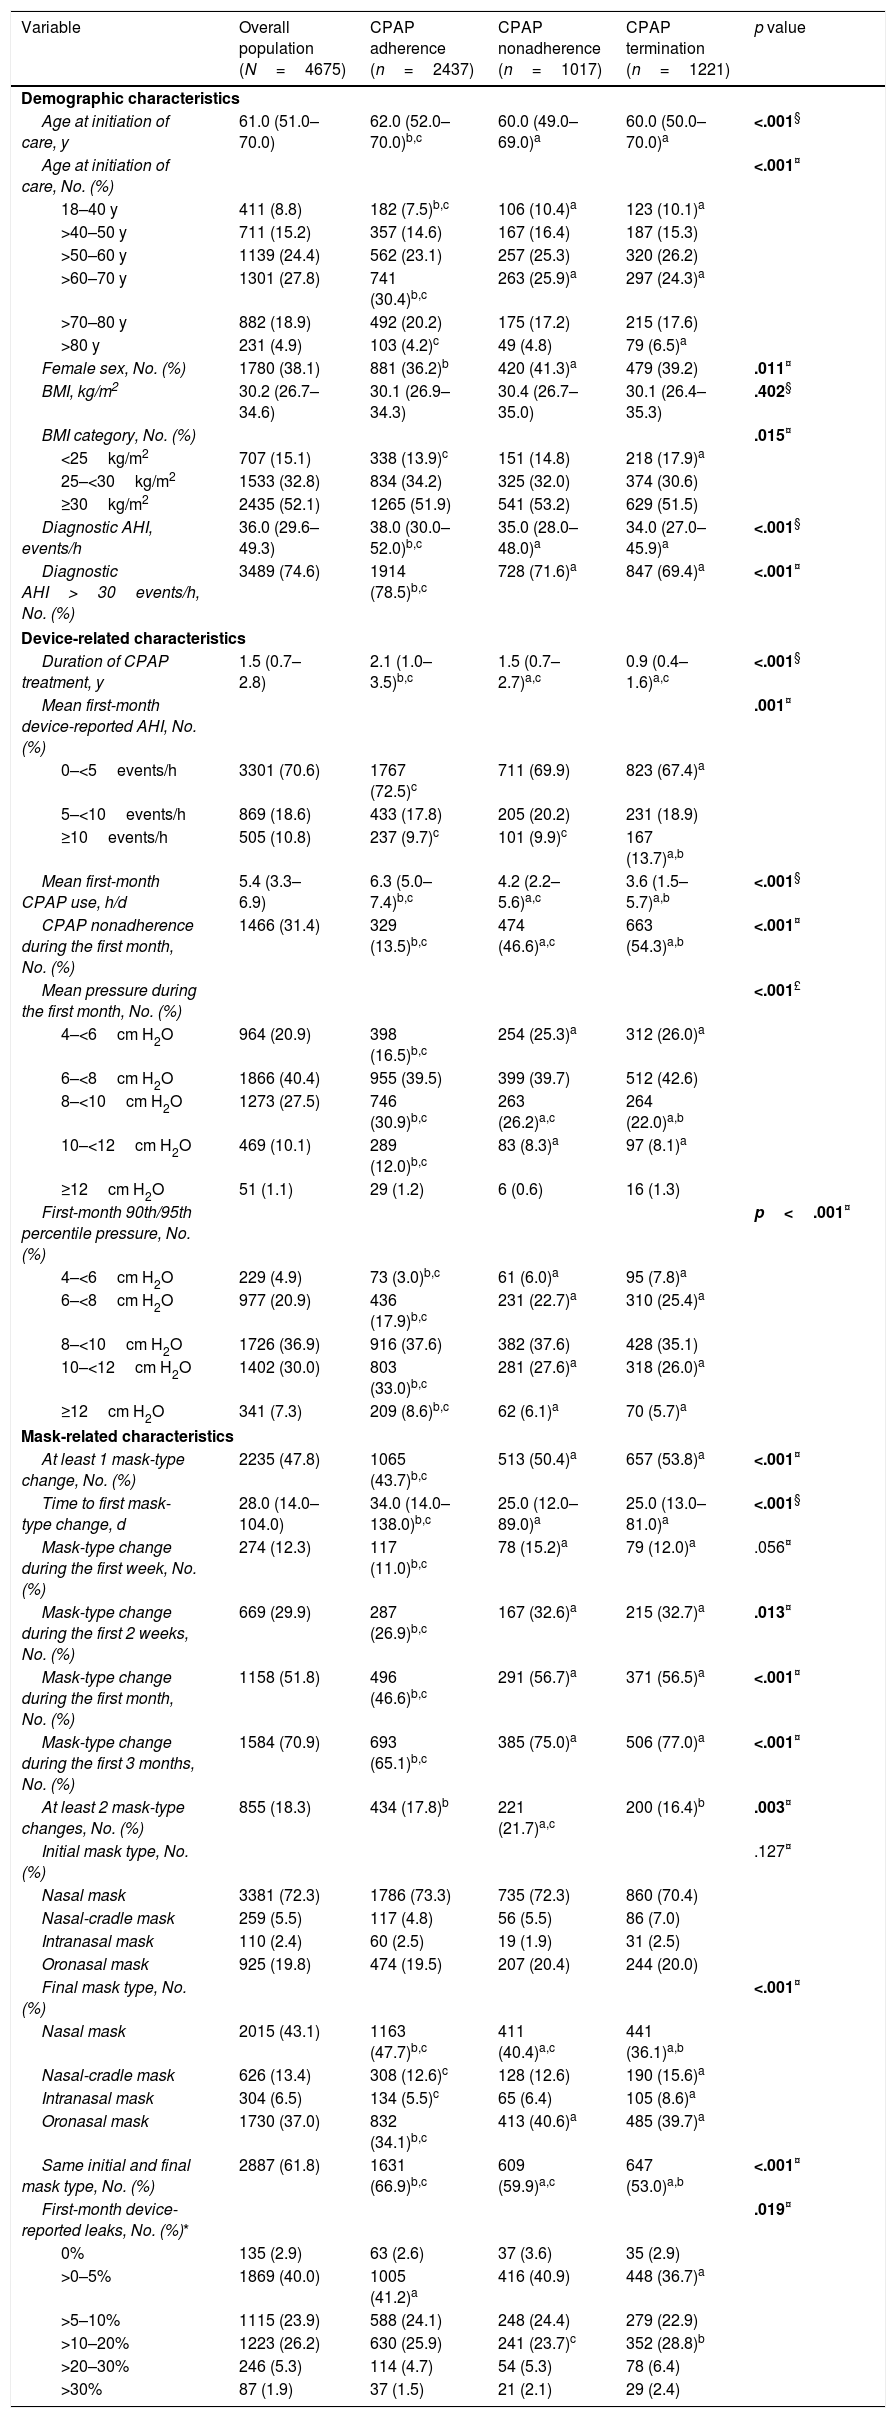
ResultsPatient characteristicsA total of 4675 adults were included in the analysis (Fig. 1). Population characteristics according to initial mask type are presented in Table 1. At the end of the study, 2437 patients (52.1%) were adherent to CPAP, 1017 (21.8%) were nonadherent, and 1221 (26.1%) had discontinued CPAP treatment (Table 2). The median duration of CPAP use was 1.5 years (IQR, 0.7–2.8 years). Auto-adjusting CPAP was used by 3677 patients (78.7%).

Population characteristics according to initial mask type.
| Variable | Overall population (N=4675) | Nasal mask (n=3381) | Nasal-cradle mask (n=259) | Intranasal mask (n=110) | Oronasal mask (n=925) | P value |
|---|---|---|---|---|---|---|
| Demographic characteristics | ||||||
| Age at initiation of care, y | 61.0 (51.0–70.0) | 61.0 (51.0–70.0) | 61.0 (49.0–70.0) | 59.0 (51.0–69.0) | 61.0 (51.0–70.0) | .598§ |
| Age at initiation of care, No. (%) | .281¤ | |||||
| 18–40 y | 411 (8.8) | 282 (8.3) | 24 (9.3) | 5 (4.5) | 100 (10.8) | |
| >40–50 y | 711 (15.2) | 520 (15.4) | 44 (17.0) | 20 (18.2) | 127 (13.7) | |
| >50–60 y | 1139 (24.4) | 816 (24.1) | 60 (23.2) | 35 (31.8) | 228 (24.6) | |
| >60–70 y | 1301 (27.8) | 942 (27.9) | 69 (26.6) | 25 (22.7) | 265 (28.6) | |
| >70–80 y | 882 (18.9) | 656 (19.4) | 51 (19.7) | 20 (18.2) | 155 (16.8) | |
| >80 y | 231 (4.9) | 165 (4.9) | 11 (4.2) | 5 (4.5) | 50 (5.4) | |
| Female sex, No. (%) | 1780 (38.1) | 1296 (38.3)b,d | 131 (50.6)a,d | 49 (44.5)d | 304 (32.9)a,b,c | <.001¤ |
| BMI, kg/m2 | 30.2 (26.7–34.6) | 30.2 (26.6–34.6)b | 29.0 (25.8–33.5)a,d | 29.3 (26.9–34.2) | 30.6 (27.2–35.2)b | .002§ |
| BMI category, No. (%) | .012¤ | |||||
| <25kg/m2 | 707 (15.1) | 506 (15.0) | 51 (19.7) | 18 (16.4) | 132 (14.3) | |
| 25–<30kg/m2 | 1533 (32.8) | 1121 (33.2) | 95 (36.7) | 42 (38.2) | 275 (29.7) | |
| ≥30kg/m2 | 2435 (52.1) | 1754 (51.9)b | 113 (43.6)a,d | 50 (45.5) | 518 (56.0)b | |
| Diagnostic AHI, events/h | 36.0 (29.6–49.3) | 36.0 (29.6–49.3) | 35.6 (30.0–47.0) | 37.0 (28.0–48.0) | 36.0 (29.3–50.2) | .833§ |
| Diagnostic AHI>30events/h, No. (%) | 3489 (74.6) | 2524 (74.7) | 200 (77.2) | 80 (72.7) | 685 (74.1) | .731§ |
| Device-related characteristics | ||||||
| Duration of CPAP treatment, y | 1.5 (0.7–2.8) | 1.6 (0.7–3.0)c,d | 1.5 (0.6–2.6)c | 1.8 (1.0–3.8)a,b,d | 1.4 (0.7–2.5)a,c | <.001§ |
| Mean first-month device-reported AHI, No. (%) | <.001¤ | |||||
| 0–<5events/h | 3301 (70.6) | 2479 (73.3)d | 186 (71.8)d | 81 (73.6)d | 555 (60.0)a,b,c | |
| 5–<10events/h | 869 (18.6) | 566 (16.7)d | 49 (18.9) | 18 (16.4) | 236 (25.5)a | |
| ≥10events/h | 505 (10.8) | 336 (9.9)d | 24 (9.3) | 11 (10.0) | 134 (14.5)a | |
| Mean first-month CPAP use, h/d | 5.4 (3.3–6.9) | 5.5 (3.4–6.9)b | 4.8 (2.8–6.5)a | 4.8 (2.3–6.4) | 5.4 (3.2–6.8) | .009§ |
| CPAP nonadherence during the first month, No. (%) | 1466 (31.4) | 1032 (30.5) | 94 (36.3) | 43 (39.1) | 297 (32.1) | .062¤ |
| Mean pressure during the first month, No. (%) | <.001£ | |||||
| 4–<6cm H2O | 964 (20.9) | 757 (22.6)d | 51 (20.5)d | 32 (29.1)d | 124 (13.6)a,b,c | |
| 6–<8cm H2O | 1866 (40.4) | 1381 (41.2)d | 114 (45.8)d | 50 (45.5) | 321 (35.2)a,b | |
| 8–<10cm H2O | 1273 (27.5) | 908 (27.1) | 70 (28.1) | 21 (19.1) | 274 (30.0) | |
| 10–<12cm H2O | 469 (10.1) | 283 (8.4)d | 12 (4.8)d | 7 (6.4)d | 167 (18.3)a,b,c | |
| ≥12cm H2O | 51 (1.1) | 22 (0.7)d | 2 (0.8) | 0 (0.0) | 27 (3.0)a | |
| First-month 90th/95th percentile pressure, No. (%) | <.001£ | |||||
| 4–<6cm H2O | 229 (4.9) | 179 (5.3)d | 15 (5.8) | 7 (6.4) | 28 (3.0)a | |
| 6–<8cm H2O | 977 (20.9) | 756 (22.4)c,d | 59 (22.8)c,d | 37 (33.6)a,b,d | 125 (13.5)a,b,c | |
| 8–<10cm H2O | 1726 (36.9) | 1262 (37.3)b,d | 119 (45.9)a,d | 41 (37.3) | 304 (32.9)a,b | |
| 10–<12cm H2O | 1402 (30.0) | 965 (28.8)b,c,d | 56 (21.6)a,d | 19 (17.3)a,d | 362 (39.1)a,b,c | |
| ≥12cm H2O | 341 (7.3) | 219 (6.5)d | 10 (3.9)d | 6 (5.5) | 106 (11.5)a,b | |
| CPAP termination, No. (%) | 1221 (26.1) | 860 (25.4)b | 86 (33.2)a | 31 (28.2) | 244 (26.4) | .050¤ |
| CPAP nonadherence, No. (%) | 1017 (21.8) | 735 (21.7) | 56 (21.6) | 19 (17.3) | 207 (22.4) | .679¤ |
| CPAP adherence, No. (%) | 2437 (52.1) | 1786 (52.8) | 117 (45.2) | 60 (54.5) | 474 (51.2) | .101¤ |
| Mask-related characteristics | ||||||
| At least 1 mask-type change, No. (%) | 2235 (47.8) | 1813 (53.6)d | 137 (52.9)d | 66 (60.0)d | 219 (23.7)a,b,c | <.001¤ |
| Time to first mask-type change, d | 28.0 (14.0–104.0) | 27.0 (13.0–99.0)d | 28.0 (14.0–77.0)d | 44.5 (13.0–218.0) | 46.0 (15.0–147.0)a,b | .002§ |
| Mask-type change during the first week, No. (%) | 274 (12.3) | 234 (12.9) | 14 (10.2) | 5 (7.6) | 21 (9.6) | .258¤ |
| Mask-type change during the first 2 weeks, No. (%) | 669 (29.9) | 560 (30.9) | 37 (27.0) | 18 (27.3) | 54 (24.7) | .214¤ |
| Mask-type change during the first month, No. (%) | 1158 (51.8) | 967 (53.3)d | 76 (55.5)d | 28 (42.4) | 87 (39.7)a,b | <.001¤ |
| Mask-type change during the first 3 months, No. (%) | 1584 (70.9) | 1299 (71.6)d | 108 (78.8)d | 44 (66.7) | 133 (60.7)a,b | .001¤ |
| At least 2 mask-type changes, No. (%) | 855 (18.3) | 657 (19.4)d | 52 (20.1)d | 25 (22.7)d | 121 (13.1)a,b,c | <.001¤ |
| Same initial and final mask type, No. (%) | 2887 (61.8) | 1891 (55.9)d | 150 (57.9)d | 57 (51.8)d | 789 (85.3)a,b,c | <.001¤ |
| First-month device-reported leaks, No. (%)* | <.001£ | |||||
| 0% | 135 (2.9) | 96 (2.8) | 7 (2.7) | 3 (2.7) | 29 (3.1) | |
| >0–5% | 1869 (40.0) | 1346 (39.8) | 120 (46.3) | 46 (41.8) | 357 (38.6) | |
| >5–10% | 1115 (23.9) | 847 (25.1)d | 59 (22.8) | 30 (27.3) | 179 (19.4)a | |
| >10–20% | 1223 (26.2) | 872 (25.8) | 65 (25.1) | 27 (24.5) | 259 (28.0) | |
| >20–30% | 246 (5.3) | 166 (4.9)d | 5 (1.9)d | 4 (3.6) | 71 (7.7)a,b | |
| >30% | 87 (1.9) | 54 (1.6)d | 3 (1.2) | 0 (0.0) | 30 (3.2)a | |
Data are expressed as median (IQR) or No. (%), as appropriate. Boldface indicates statistical significance at the 5% level.
AHI, apnoea–hypopnoea index; BMI, body mass index; CPAP, continuous positive airway pressure.
Leaks were obtained using built-in CPAP software; Leak severity categories (based on percentiles of the maximum leak) in the first month. Data are reported as medians and quartiles or numbers and percentages of total as appropriate.
Fisher's Exact Test. Bolds variables are statistically significant at the 5% threshold.
Labels a, b, c and d: within a given line, initial mask type subgroups with different letters are significantly different (p<0.05) according to post hoc pairwise comparisons after false discovery rate corrections. Label a for nasal mask, label b for nasal cradle mask, label c for intranasal mask and label d for oronasal mask. As an example, for the gender variable, there is a significant difference (p<0.05) between initial mask type. Post hoc pairwise comparisons indicate that nasal mask is significantly different with nasal cradle mask (label b) and oronasal mask (label d) but there is no significant difference between nasal mask and intranasal mask (no label c).
Population characteristics according to final CPAP adherence, CPAP nonadherence, and CPAP termination.
| Variable | Overall population (N=4675) | CPAP adherence (n=2437) | CPAP nonadherence (n=1017) | CPAP termination (n=1221) | p value |
|---|---|---|---|---|---|
| Demographic characteristics | |||||
| Age at initiation of care, y | 61.0 (51.0–70.0) | 62.0 (52.0–70.0)b,c | 60.0 (49.0–69.0)a | 60.0 (50.0–70.0)a | <.001§ |
| Age at initiation of care, No. (%) | <.001¤ | ||||
| 18–40 y | 411 (8.8) | 182 (7.5)b,c | 106 (10.4)a | 123 (10.1)a | |
| >40–50 y | 711 (15.2) | 357 (14.6) | 167 (16.4) | 187 (15.3) | |
| >50–60 y | 1139 (24.4) | 562 (23.1) | 257 (25.3) | 320 (26.2) | |
| >60–70 y | 1301 (27.8) | 741 (30.4)b,c | 263 (25.9)a | 297 (24.3)a | |
| >70–80 y | 882 (18.9) | 492 (20.2) | 175 (17.2) | 215 (17.6) | |
| >80 y | 231 (4.9) | 103 (4.2)c | 49 (4.8) | 79 (6.5)a | |
| Female sex, No. (%) | 1780 (38.1) | 881 (36.2)b | 420 (41.3)a | 479 (39.2) | .011¤ |
| BMI, kg/m2 | 30.2 (26.7–34.6) | 30.1 (26.9–34.3) | 30.4 (26.7–35.0) | 30.1 (26.4–35.3) | .402§ |
| BMI category, No. (%) | .015¤ | ||||
| <25kg/m2 | 707 (15.1) | 338 (13.9)c | 151 (14.8) | 218 (17.9)a | |
| 25–<30kg/m2 | 1533 (32.8) | 834 (34.2) | 325 (32.0) | 374 (30.6) | |
| ≥30kg/m2 | 2435 (52.1) | 1265 (51.9) | 541 (53.2) | 629 (51.5) | |
| Diagnostic AHI, events/h | 36.0 (29.6–49.3) | 38.0 (30.0–52.0)b,c | 35.0 (28.0–48.0)a | 34.0 (27.0–45.9)a | <.001§ |
| Diagnostic AHI>30events/h, No. (%) | 3489 (74.6) | 1914 (78.5)b,c | 728 (71.6)a | 847 (69.4)a | <.001¤ |
| Device-related characteristics | |||||
| Duration of CPAP treatment, y | 1.5 (0.7–2.8) | 2.1 (1.0–3.5)b,c | 1.5 (0.7–2.7)a,c | 0.9 (0.4–1.6)a,c | <.001§ |
| Mean first-month device-reported AHI, No. (%) | .001¤ | ||||
| 0–<5events/h | 3301 (70.6) | 1767 (72.5)c | 711 (69.9) | 823 (67.4)a | |
| 5–<10events/h | 869 (18.6) | 433 (17.8) | 205 (20.2) | 231 (18.9) | |
| ≥10events/h | 505 (10.8) | 237 (9.7)c | 101 (9.9)c | 167 (13.7)a,b | |
| Mean first-month CPAP use, h/d | 5.4 (3.3–6.9) | 6.3 (5.0–7.4)b,c | 4.2 (2.2–5.6)a,c | 3.6 (1.5–5.7)a,b | <.001§ |
| CPAP nonadherence during the first month, No. (%) | 1466 (31.4) | 329 (13.5)b,c | 474 (46.6)a,c | 663 (54.3)a,b | <.001¤ |
| Mean pressure during the first month, No. (%) | <.001£ | ||||
| 4–<6cm H2O | 964 (20.9) | 398 (16.5)b,c | 254 (25.3)a | 312 (26.0)a | |
| 6–<8cm H2O | 1866 (40.4) | 955 (39.5) | 399 (39.7) | 512 (42.6) | |
| 8–<10cm H2O | 1273 (27.5) | 746 (30.9)b,c | 263 (26.2)a,c | 264 (22.0)a,b | |
| 10–<12cm H2O | 469 (10.1) | 289 (12.0)b,c | 83 (8.3)a | 97 (8.1)a | |
| ≥12cm H2O | 51 (1.1) | 29 (1.2) | 6 (0.6) | 16 (1.3) | |
| First-month 90th/95th percentile pressure, No. (%) | p<.001¤ | ||||
| 4–<6cm H2O | 229 (4.9) | 73 (3.0)b,c | 61 (6.0)a | 95 (7.8)a | |
| 6–<8cm H2O | 977 (20.9) | 436 (17.9)b,c | 231 (22.7)a | 310 (25.4)a | |
| 8–<10cm H2O | 1726 (36.9) | 916 (37.6) | 382 (37.6) | 428 (35.1) | |
| 10–<12cm H2O | 1402 (30.0) | 803 (33.0)b,c | 281 (27.6)a | 318 (26.0)a | |
| ≥12cm H2O | 341 (7.3) | 209 (8.6)b,c | 62 (6.1)a | 70 (5.7)a | |
| Mask-related characteristics | |||||
| At least 1 mask-type change, No. (%) | 2235 (47.8) | 1065 (43.7)b,c | 513 (50.4)a | 657 (53.8)a | <.001¤ |
| Time to first mask-type change, d | 28.0 (14.0–104.0) | 34.0 (14.0–138.0)b,c | 25.0 (12.0–89.0)a | 25.0 (13.0–81.0)a | <.001§ |
| Mask-type change during the first week, No. (%) | 274 (12.3) | 117 (11.0)b,c | 78 (15.2)a | 79 (12.0)a | .056¤ |
| Mask-type change during the first 2 weeks, No. (%) | 669 (29.9) | 287 (26.9)b,c | 167 (32.6)a | 215 (32.7)a | .013¤ |
| Mask-type change during the first month, No. (%) | 1158 (51.8) | 496 (46.6)b,c | 291 (56.7)a | 371 (56.5)a | <.001¤ |
| Mask-type change during the first 3 months, No. (%) | 1584 (70.9) | 693 (65.1)b,c | 385 (75.0)a | 506 (77.0)a | <.001¤ |
| At least 2 mask-type changes, No. (%) | 855 (18.3) | 434 (17.8)b | 221 (21.7)a,c | 200 (16.4)b | .003¤ |
| Initial mask type, No. (%) | .127¤ | ||||
| Nasal mask | 3381 (72.3) | 1786 (73.3) | 735 (72.3) | 860 (70.4) | |
| Nasal-cradle mask | 259 (5.5) | 117 (4.8) | 56 (5.5) | 86 (7.0) | |
| Intranasal mask | 110 (2.4) | 60 (2.5) | 19 (1.9) | 31 (2.5) | |
| Oronasal mask | 925 (19.8) | 474 (19.5) | 207 (20.4) | 244 (20.0) | |
| Final mask type, No. (%) | <.001¤ | ||||
| Nasal mask | 2015 (43.1) | 1163 (47.7)b,c | 411 (40.4)a,c | 441 (36.1)a,b | |
| Nasal-cradle mask | 626 (13.4) | 308 (12.6)c | 128 (12.6) | 190 (15.6)a | |
| Intranasal mask | 304 (6.5) | 134 (5.5)c | 65 (6.4) | 105 (8.6)a | |
| Oronasal mask | 1730 (37.0) | 832 (34.1)b,c | 413 (40.6)a | 485 (39.7)a | |
| Same initial and final mask type, No. (%) | 2887 (61.8) | 1631 (66.9)b,c | 609 (59.9)a,c | 647 (53.0)a,b | <.001¤ |
| First-month device-reported leaks, No. (%)* | .019¤ | ||||
| 0% | 135 (2.9) | 63 (2.6) | 37 (3.6) | 35 (2.9) | |
| >0–5% | 1869 (40.0) | 1005 (41.2)a | 416 (40.9) | 448 (36.7)a | |
| >5–10% | 1115 (23.9) | 588 (24.1) | 248 (24.4) | 279 (22.9) | |
| >10–20% | 1223 (26.2) | 630 (25.9) | 241 (23.7)c | 352 (28.8)b | |
| >20–30% | 246 (5.3) | 114 (4.7) | 54 (5.3) | 78 (6.4) | |
| >30% | 87 (1.9) | 37 (1.5) | 21 (2.1) | 29 (2.4) | |
Data are presented as median (IQR) or No. (%), as appropriate. Boldface indicates statistical significance at the 5% level.
AHI, apnoea–hypopnoea index; BMI, body mass index; CPAP, continuous positive airway pressure.
Leaks were obtained using built-in CPAP software; Leak severity categories (based on percentiles of the maximum leak) in the first month. Data are reported as medians and quartiles or numbers and percentages of total as appropriate.
Fisher's Exact Test. Bolds variables are statistically significant at the 5% threshold.
Labels a, b, and c: within a given line, CPAP-adherence, CPAP-non-adherence and CPAP termination subgroups with different letters are significantly different (p<0.05) according to post hoc pairwise comparisons after false discovery rate corrections. Label a for CPAP-adherence, label b for CPAP-non-adherence and label c for CPAP termination. As an example, for the gender variable, there is a significant difference (p<0.05) between CPAP-adherence, CPAP-non-adherence and CPAP termination subgroups. Post hoc pairwise comparisons indicate that CPAP-adherence (label a) is significantly different with CPAP-non-adherence (label b) but there is no significant difference between CPAP-adherence and CPAP termination (no label c).
Mask-type trajectories are shown in Fig. 2. Overall, 47.8% of patients changed mask type at least once, with a maximum of 8 changes (Fig. E1).

Sankey diagram of mask-type trajectories from treatment initiation to the end of the study. Flows represent transitions between mask types over time, with band width proportional to the number of patients. The left margin shows the initial distribution of mask types, and the right margin shows the final distribution. INM, intranasal mask; NCM, nasal-cradle mask; NM, nasal mask; ONM, oronasal mask.
From baseline to the final assessment, NM use decreased from 72.3% to 43.1%, whereas ONM use increased from 19.8% to 37.0%, INM use from 2.4% to 6.5%, and NCM use from 5.5% to 13.4%.
CPAP-adherent patients changed mask type less frequently than nonadherent patients or those who discontinued CPAP treatment (43.7% vs 50.4% and 53.8%, respectively; p<.001) (Table 2).
Fig. 3 shows transitions between mask types at 2 consecutive mask changes, stratified according to final CPAP status: adherence, nonadherence, or treatment termination.

Mask-type transitions between consecutive changes. Heat maps show the percentage of transitions from the mask used at time t (rows) to the mask used at time t+1 (columns). Panels are stratified according to final CPAP-use status: adherence, nonadherence, or treatment termination. Diagonal cells indicate persistence with the same mask type, whereas off-diagonal cells indicate switches. Colour intensity increases with the percentage of patients.
Fig. E2 shows the 11 mask-type sequence groups identified using sequence analysis. The first 4 groups comprised patients with renewal trajectories involving NM, ONM, NCM, or INM. Groups 5–7 comprised patients who switched from an NM to an ONM, NCM, or INM.
Groups 8–11 included patients with 2 switches and shared similar final 2-step patterns: ONM→NM, NCM→NM, INM→NM, and NCM→ONM. After groups 8–11 were subdivided according to initial mask type, 15 distinct trajectories were analysed. Population characteristics according to trajectory are presented in Table E3 and Fig. 4.

Mask-sequence groups according to patient characteristics. Heat maps show the characteristics of each mask-sequence group. For each trajectory group (columns), rows show clinical and treatment characteristics expressed as percentages—female sex, BMI≥30kg/m2, diagnostic AHI>30events/h, CPAP termination, CPAP nonadherence, and CPAP adherence—or medians (IQR)—age, first-month CPAP use, and final-month CPAP use excluding patients who terminated treatment. Colour intensity increases with the value. AHI, apnoea–hypopnoea index; BMI, body mass index; INM, intranasal mask; NCM, nasal-cradle mask; NM, nasal mask; ONM, oronasal mask. Technical note: For quantitative CPAP-use variables, 8h/d was defined as 100%.
Two models were fitted: model 1 compared nonadherence with adherence (Fig. 5 and Table E4), and model 2 compared treatment termination with adherence (Fig. 6 and Table E4).


Multivariable multinomial regression analysis of CPAP termination. INM, intranasal mask; NCM, nasal-cradle mask; NM, nasal mask; ONM, oronasal mask. First-month leak values correspond to leak-severity categories based on percentiles of the maximum leak recorded during the first month. NM→NM indicates NM renewal.
In model 1, the area under the receiver operating characteristic curve was 0.77 (95%CI, 0.76–0.79). The trajectory involving a return to NM after an intermediate ONM, NM/∅→ONM→NM with NM as the initial mask, was associated with higher odds of nonadherence (OR, 1.70; 95%CI, 1.13–2.54; p=.010). The remaining trajectories did not differ significantly from the NM renewal trajectory.
In model 2, the area under the receiver operating characteristic curve was 0.83 (95%CI, 0.82–0.84). Several mask-use trajectories were independently associated with higher odds of treatment termination: NM→INM (OR, 1.88; 95%CI, 1.28–2.39; p=.004), NM→NCM (OR, 1.76; 95%CI, 1.26–2.45; p=.001), NM→ONM (OR, 1.31; 95%CI, 1.01–1.70; p=.046), and NCM renewal (n=181; OR, 2.04; 95%CI, 1.04–2.47; p=.034).
Notably, ONM and INM renewal trajectories were not associated with a higher risk of CPAP nonadherence or treatment termination than the reference NM renewal trajectory.
Consequences of combining nasal and nasal-pillow masks into a single mask categoryConsistent with the conclusions of the workshop report, which compared oronasal masks with nonoronasal masks without distinguishing between nasal and nasal-pillow masks [10], we conducted an exploratory analysis comparing 2 mask categories: ONM and a combined NM/NPM category.
Mask-type trajectories, sequence analysis, and predictors of CPAP nonadherence and treatment termination are shown in Figs. E3–E6. Combining nasal and nasal-pillow masks into a single category resulted in loss of the statistically significant association between switching from an NM to an ONM and CPAP termination.
DiscussionTo our knowledge, this is the first long-term study to evaluate CPAP mask-use trajectories and adherence in a large cohort of 4675 adults initiating treatment with unrestricted access to 48 mask models across 4 mask types.
The principal findings were as follows: (1) almost half of the patients changed mask type at least once, and the distribution of mask types changed substantially from baseline to the end of follow-up; (2) patients who were adherent to CPAP at the end of follow-up changed mask type less frequently than nonadherent patients or those who discontinued treatment; (3) in multivariable analyses, the trajectory involving return to NM after an intermediate ONM was associated with higher odds of CPAP nonadherence, whereas switching from an initial NM to an INM, NCM, or ONM was associated with higher odds of CPAP termination; and (4) ONM and INM renewal trajectories were not associated with a higher risk of CPAP nonadherence or treatment termination than the reference NM renewal trajectory, whereas NCM renewal was significantly associated with treatment termination.
Reconciling nasal-first recommendations with evidence from cohort studies and clinical trialsCurrent guidelines and expert statements converge on a nasal-first strategy for CPAP initiation. The 2020 American Thoracic Society workshop report [10] and the 2019 American Academy of Sleep Medicine guidelines [5] conclude that nasal interfaces, including NMs and NPMs, should generally be preferred to ONMs. This position is supported by meta-analyses showing slightly lower residual AHI, lower therapeutic pressure, and better adherence with NMs and NPMs than with ONMs [11,12].
However, randomised crossover trials comparing NMs or NPMs with ONMs under controlled conditions have not consistently demonstrated poorer adherence with ONMs, although ONMs often require slightly higher pressures or are associated with slightly more residual respiratory events [15–17]. In contrast, large cohort and registry studies have repeatedly reported lower long-term CPAP adherence with ONMs [14,18,19].
Our trajectory-based analysis may help reconcile this discrepancy. In our cohort, stable mask-type trajectories, such as ONM renewal, were associated with rates of long-term CPAP nonadherence and treatment termination similar to those observed with the reference NM renewal trajectory. Conversely, trajectories involving a switch from an initial NM to an ONM or cycling through an ONM before returning to an NM, such as NM/∅→ONM→NM, were consistently associated with a higher risk of treatment termination.
These findings suggest that the apparent advantage of nasal masks reported in observational studies may partly reflect rescue use of ONMs in patients whose treatment course is already difficult rather than an inherent inferiority of ONMs when selected and maintained as the primary interface. Delayed switching to an ONM was associated with poorer long-term CPAP use. Whether earlier identification of patients likely to require an ONM and initial selection of this interface would improve outcomes requires prospective evaluation.
Differentiating intranasal masks from nasal-cradle masks in long-term outcomesOur findings refine the evidence regarding so-called nasal-pillow masks. A recent meta-analysis that excluded NCMs and was restricted to INMs showed that, compared with standard NMs, INMs achieved similar residual AHI values and therapeutic pressures, with only a clinically negligible increase in nightly CPAP use of 0.29min [12].
In designing the present study, we therefore deliberately distinguished INMs from NCMs because nasal-cradle designs are more recent, have been less extensively studied, and their appropriate role in CPAP management remains uncertain.
In our cohort, renewal trajectories involving INMs performed similarly to the reference NM renewal trajectory. Among patients who did not discontinue treatment, CPAP use during the final month was 6.1h/d (IQR, 4.1–7.2h/d) in the INM group and 6.0h/d (IQR, 4.0–7.3h/d) in the NM group.
In multivariable models, INM renewal was not associated with higher odds of CPAP nonadherence or treatment termination than NM renewal, suggesting broadly comparable long-term performance. These comparisons should nevertheless be interpreted cautiously because of the smaller size of the INM renewal group (n=103) and its higher proportion of women (44.7%), which may have reduced precision and reflected selection effects.
In contrast, NCM renewal was associated with lower CPAP use during the final month (median, 5.3h/d; IQR, 2.2–7.1h/d), a higher treatment termination rate of 32.6%, and independently higher odds of CPAP termination in adjusted models. The NM→NCM trajectory was also associated with higher rates of treatment termination and unstable patterns, with frequent switching back to NM.
These NCM trajectories differ from the INM renewal trajectory and indicate that INMs and NCMs should not be combined within a single nasal-pillow category. Defining the appropriate role of NCMs will require adequately powered trials in both CPAP-naive and CPAP-experienced populations, with mask-specific reporting of adherence, treatment discontinuation, and long-term outcomes.
In this context, Zhu et al. [20] recently evaluated a remote mask-switching protocol among adults receiving positive airway pressure therapy who had long-standing treatment and high baseline device use of 7.1h/night. New-generation masks, including the AirFit F30i ONM and N30i NCM, were fitted remotely in 215 participants. Only 136 participants (63%) were still using the new mask at day 90, whereas the remainder had returned to their previous interface.
However, the primary analyses pooled the F30i and N30i masks and did not report adherence or discontinuation separately for the N30i. In addition, no positive airway pressure-naive patients were included. These limitations restrict conclusions regarding nasal-cradle designs both during routine treatment initiation and after switching from an NM.
Mask-type switching, CPAP nonadherence, and treatment terminationIn our cohort, mask-type switches were more frequent among patients who eventually became nonadherent or discontinued CPAP than among those who remained adherent.
In multivariable models, all sequences that began with an NM and ended with another mask type, including NM→ONM, NM→NCM, and NM→INM, as well as the NCM renewal trajectory, were independently associated with higher odds of treatment termination. In contrast, stable NM and ONM renewal trajectories were not associated with increased risk.
These findings suggest that mask switching in routine practice may more often be a marker of a difficult treatment course than a straightforward remedy.
Our results complement a recent telemedicine study that evaluated either an initial mask switch or simple mask renewal during the first year after initiation of auto-adjusting CPAP [21]. In that study, only patients with low baseline use of less than 4h/night experienced a clinically meaningful increase in nightly CPAP use after switching mask type, amounting to 55 additional minutes per night. Renewal of the same mask produced a smaller effect, and neither intervention benefited patients who were already adherent.
However, that study did not assess long-term treatment discontinuation or the cumulative effects of multiple mask-type switches. Another prospective single-centre cohort found that patients who changed mask type had a substantially higher 1-year CPAP termination rate than those who did not (12.7% vs 1.8%; adjusted OR, 7.24) [22]. This finding suggests that mask-type switching may identify a subgroup at increased risk of treatment discontinuation rather than consistently improving outcomes.
Taken together, these data indicate that targeted early mask-type changes may benefit selected patients with low use but that mask switching is not universally advantageous. Our trajectory analysis further suggests that repeated or delayed switches, particularly those involving departure from an initial nasal interface or persistent use of an NCM, identify patients at increased risk of long-term nonadherence and CPAP termination.
Nasal-cradle masks are relatively recent interfaces, and their introduction with full reimbursement in the French healthcare system may have generated an early-adopter effect. Consequently, our findings should be interpreted cautiously and require external validation in other settings and populations.
Telemonitoring-based prediction of CPAP termination: early use, leaks, and mask-type switchingThe CPAP termination model showed strong discrimination, with an area under the receiver operating characteristic curve of 0.83, indicating clinically useful differentiation between patients who remained on treatment and those who ultimately discontinued it.
First-month telemonitoring variables, particularly duration of CPAP use and early leak burden, were more informative than baseline disease severity. Each additional hour of CPAP use during the first month was associated with approximately 33% lower odds of subsequent treatment termination. Higher early leak levels showed a dose-response association with later discontinuation.
Mask-type trajectories provided additional prognostic information beyond these early behavioural variables. Sequences involving departure from an initial NM and ending with another interface, as well as patterns involving an ONM before return to an NM, were associated with higher odds of treatment termination. In contrast, NM, INM, and ONM renewal trajectories were not associated with increased risk.
Although the effect sizes associated with mask-type trajectories were smaller than those associated with early use and leak burden, they improved risk stratification. These findings suggest that telemonitoring strategies should not only assess hours of use and leak levels but should also document mask-type changes and identify high-risk switching trajectories to help prevent treatment termination.
Strengths and limitationsThe strengths of this study include the large cohort of CPAP-naive patients, unrestricted access to 48 mask models across 4 mask types, including newer nasal-cradle designs, and daily telemonitoring data collected over prolonged follow-up.
Several limitations should also be acknowledged. First, the observational design precludes causal inference, and residual confounding cannot be excluded. In particular, unmeasured clinical or behavioural factors may have influenced both mask selection and switching.
Second, initial mask allocation and subsequent mask changes were not randomised and may have reflected technician- or physician-specific practices within the home healthcare network, which comprised at least 352 physicians and 53 technicians.
Third, although we distinguished 4 major mask types and analysed INMs separately from NCMs, we did not evaluate individual models or manufacturers. Estimates for NCM trajectories were also less precise because these interfaces were more recent and less frequently used.
Fourth, the determinants of mask switching, including excessive leak, reduced adherence, and higher CPAP pressure, were not analysed in the present study and warrant dedicated multivariable investigation.
Finally, the external validity of our findings depends on the organisational, funding, and telemonitoring framework of CPAP care. Spain shares several relevant characteristics with France because home respiratory therapies are predominantly publicly funded and involve home healthcare providers [23]. Telemonitoring of adherence is also a key component of the value-based care model recently proposed for OSA management in Spain [23].
However, this proposed framework should not be considered equivalent to the French reimbursement-linked telemonitoring system. Accordingly, the distribution of mask trajectories and the magnitude of their associations with CPAP outcomes require validation in healthcare systems with different arrangements for funding, follow-up, mask provision, and telemonitoring.
ConclusionsTaken together, our findings support a nasal-first strategy for most patients and emphasise the importance of selecting the most appropriate initial interface—an NM or INM for most patients and an ONM in selected cases—rather than focusing on identifying the “best second mask.”
They also support telemonitoring strategies that integrate early CPAP use and leak data with systematic documentation of mask-type switching to identify high-risk trajectories before treatment is discontinued.
Authors’ contributionsD.J. had full access to all study data and takes responsibility for the integrity of the data and the accuracy of the data analysis. All authors contributed to and approved the final submitted manuscript.
C.V.: data collection, statistical analysis, and manuscript preparation. J.P.M.: study design, statistical analysis, and manuscript preparation. R.G.: data collection and statistical analysis. O.G.: data collection and statistical analysis. J.C.B.: manuscript preparation. F.G.: manuscript preparation. A.P.: manuscript preparation. A.B.: manuscript preparation. N.M.: study design, data collection, statistical analysis, and manuscript preparation. D.J.: study design, statistical analysis, and manuscript preparation.
Ethics approval and consent to participateThe SwitchAdene study is registered with the Health Data Hub under registration No. 19334378. The study protocol complied with the Declaration of Helsinki. All participants provided written informed consent.
Consent for publicationNot applicable.
Artificial intelligenceNot applicable.
FundingNone declared.
Conflict of interestsC.V. is employed by Groupe Adène, a home healthcare provider. J.P.M. reports grants or funding from Groupe Adène, Novartis, Chiesi, GSK, and DPC-ORL and personal fees from Pulmonx. R.G. and O.G. are employed by Groupe Adène. J.C.B. reports consultancy fees from AGIR à dom, a French home healthcare provider.
F.G. reports personal fees from Air Liquide Santé, Inspire, Bioprojet, ResMed, and SEFAM; payment for presentations from Bioprojet, Cidelec, Inspire, ResMed, and SEFAM; and nonfinancial support from Asten Santé.
A.P. is a consultant for ResMed and reports personal fees from Elia Medical and Air Liquide Santé; payment for presentations from ResMed, Bastide, SOS Oxygène, GSK, and Isis Medical; and nonfinancial support from Air Liquide Santé, Asten Santé, SOS O2, and Elia Medical, outside the submitted work.
A.B. reports grants or funding from Boehringer Ingelheim; personal fees from AstraZeneca, Boehringer Ingelheim, Chiesi, GlaxoSmithKline, Novartis, and Sanofi-Regeneron; and participation as a clinical trial investigator for Acceleron, Actelion, Galapagos, Merck Sharp & Dohme, Nuvaira, Pulmonx, United Therapeutics, Celltrion, and Vertex.
N.M. reports grants or funding from GlaxoSmithKline and personal fees from Sanofi-Regeneron.
D.J. reports personal fees from Löwenstein, Jazz Pharmaceuticals, Bioprojet, Groupe Adène, Bastide, LVL Médical, GSK, AstraZeneca, ALK, Boehringer Ingelheim, Sanofi, Philips Healthcare, and ResMed; personal fees and nonfinancial support from SEFAM and Nomics; and grants and personal fees from Novartis, outside the submitted work.
Availability of data and materialsThe datasets used and/or analysed during the current study are available from the corresponding author upon reasonable request.
The authors thank the Groupe Adène team for their assistance in conducting this study: the administrative team—Pierre Coulot, Valérie Bachelier, Sylvie Cottret, Christophe Jeanjean, Sophie Lafitte, and Magali Partyka—and the technical team—Frédéric Bousquet, Fabrice Dumont, Sébastien Faure, Laure Ferraz, Zakarias Khalil, Yohan Lasry, David Minguez, Christophe Pinotti, Antoine Ruault, and Jean-Marc Uriol. The authors also thank Dr Joana Da Silva Pissarra for editing the manuscript.
The following are the supplementary data to this article:









