





Respiratory impairment is a major complication of neuromuscular diseases (NMDs), primarily resulting from progressive respiratory muscle weakness and dysfunction, altered chest wall mechanics, impaired central respiratory drive, or peripheral nerve dysfunction [1–3]. Alongside cardiac involvement, respiratory failure is one of the principal determinants of morbidity and mortality in this population [4–6]. Clinically, respiratory dysfunction typically develops insidiously and is often first manifested by nocturnal alveolar hypoventilation, reflecting early ventilatory insufficiency during sleep before daytime hypercapnia becomes apparent [7–9].
Early diagnosis and management of respiratory failure in patients with NMDs are essential to prevent serious respiratory complications and improve prognosis [8,10]. Nevertheless, robust and reproducible prognostic indicators capable of guiding therapeutic decisions and their timing are currently lacking.
Nocturnal hypercapnia, even in the absence of daytime hypercapnia, appears to be the most informative prognostic marker of alveolar hypoventilation in individuals with NMDs [5,8]. However, there is no consensus regarding the thresholds that define nocturnal alveolar hypoventilation [10]. Moreover, the clinical heterogeneity among different NMDs means that diagnosis and prognosis may vary substantially according to the threshold selected in individual studies [11].
Novel physiological markers are therefore needed to better characterize the severity of nocturnal respiratory abnormalities in patients with NMDs. In this study, we investigated hypercapnic burden (tcCO2bur), defined as the cumulative area of transcutaneous carbon dioxide tension (tcCO2) above a predefined threshold, as a candidate metric for quantifying nocturnal hypercapnia.
The primary endpoint of this pilot study was to develop a computer algorithm for measuring tcCO2bur in a population of patients with NMDs. The secondary objectives were to provide preliminary descriptive data regarding the value of this measurement by examining the relationship between tcCO2bur and functional and blood gas parameters and by describing patient outcomes according to tcCO2bur level.
We conducted an ancillary analysis of a single-center, cross-sectional, retrospective medical-record study involving patients with NMDs followed at the sleep disorders unit of a tertiary referral center specializing in slowly progressive neuromuscular diseases [12]. The ethical procedures specified under the MR-004 reference methodology were followed.
Data were collected retrospectively between October 2023 and March 2024. Demographic and clinical data, information on noninvasive ventilation (NIV), and details regarding the underlying neuromuscular disorder were extracted from electronic medical records (Supplementary Table 1).
To identify major cardiorespiratory events or death (MaCRED) in the study population, we used the Cohort360 platform, the health data warehouse of Assistance Publique–Hôpitaux de Paris. The platform provides coded information on reasons for consultation, symptoms, and diagnoses. International Classification of Diseases, 10th Revision codes were used to define MaCRED (Supplementary Table 2).
The eligibility of all patients included in the main study was assessed. Exclusion criteria for the ancillary study were opposition to the use of data from the institution's health data warehouse and insufficient data from the tcCO2 recording.
All patients included in the original study had undergone nocturnal tcCO2 monitoring using a Sentec® device, respiratory polygraphy, pulmonary function testing (PFT), and blood gas analysis between October 2018 and November 2023.
Hypercapnic burden was measured by calculating the area under the tcCO2 curve above a threshold of 45mm Hg over the entire recording period and was expressed in mm Hg s. This biomarker was calculated using a computer algorithm developed and implemented in MATLAB (Supplementary Fig. 1 and Supplementary Methods).
Based on the tcCO2bur values obtained, the study population was divided into 3 groups. Patients with a hypercapnic burden of 0 were assigned to group 1 (no tcCO2bur; n=50). Among patients with a positive hypercapnic burden, the median tcCO2bur was calculated and used to divide the remaining cohort into group 2 (low tcCO2bur, <8.3×104 mm Hg s; n=47) and group 3 (high tcCO2bur, ≥8.3×104 mm Hg s; n=48).
Statistical analyses were performed using JASP software (Jeffreys's Amazing Statistics Program, version 0.96.0; JASP Team, 2020). Conventional analysis of variance was used to compare the 3 patient groups with respect to demographic data, tcCO2 measurements, PFT results, and blood gas parameters. Pearson correlation coefficients (r) were calculated to assess linear associations between tcCO2bur and the different PFT and blood gas parameters. A detailed description of the methods is provided in the online Supplementary Material.
Data from 145 of the 149 patients screened in the original study were analyzed in this pilot study (Supplementary Fig. 2). The most common NMD was myotonic dystrophy type 1, also known as Steinert disease (n=46) (Supplementary Table 1). The study population comprised predominantly middle-aged patients, with a mean age of 45.4 years (SD, 18 years); 60% were men. The mean body mass index was 24.2kg/m2 (SD, 6.2kg/m2) (Supplementary Table 3).
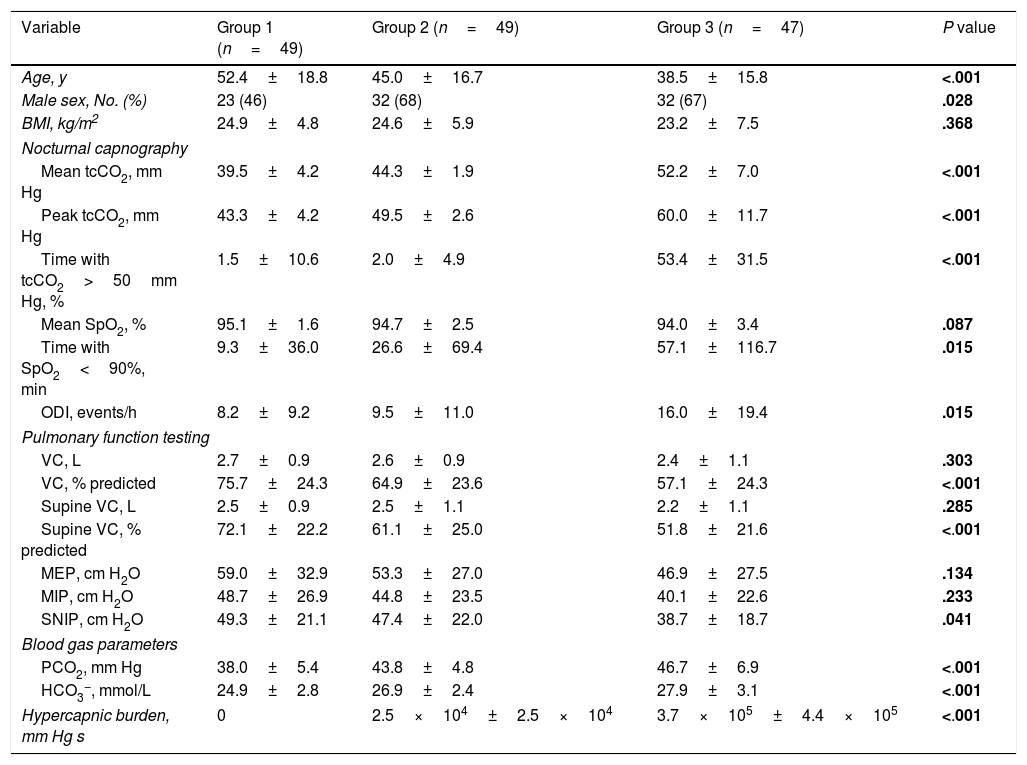
The tcCO2bur measurement algorithm was successfully applied to all tcCO2 recordings, and a numerical tcCO2bur value was obtained for every patient. Of the 145 patients, 50 had no hypercapnic burden and were assigned to group 1. The remaining 95 had a positive hypercapnic burden and were assigned to groups 2 and 3. Mean tcCO2bur was 2.5×104 mm Hg s in group 2 and 3.7×105 mm Hg s in group 3.
Hypercapnic burden was significantly correlated with vital capacity (VC), supine VC, partial pressure of carbon dioxide (PCO2), and bicarbonate concentration (HCO3−), with Pearson correlation coefficients ranging from 0.20 to 0.39, indicating weak correlations (Fig. 1). No significant correlation was observed between tcCO2bur and maximum inspiratory pressure or maximum expiratory pressure.

Significant correlations were found between tcCO2bur and mean tcCO2, peak tcCO2, and the percentage of recording time with tcCO2>50mm Hg, with Pearson correlation coefficients ranging from 0.60 to 0.79; P<.001. These findings indicated strong correlations.
A significant but weak correlation was also observed between hypercapnic burden and oximetry parameters, including mean oxygen saturation measured by pulse oximetry (SpO2), percentage of recording time with SpO2<90%, and oxygen desaturation index, with Pearson correlation coefficients ranging from 0.20 to 0.39 (Supplementary Fig. 3).
Comparison of the 3 groups defined according to tcCO2bur revealed significant between-group differences in tcCO2 and blood gas parameters. Mean tcCO2, peak tcCO2, percentage of time with tcCO2>50mm Hg, PCO2, and HCO3− increased with increasing tcCO2bur (Table 1).
Comparison of patients with neuromuscular diseases according to hypercapnic burden.
| Variable | Group 1 (n=49) | Group 2 (n=49) | Group 3 (n=47) | P value |
|---|---|---|---|---|
| Age, y | 52.4±18.8 | 45.0±16.7 | 38.5±15.8 | <.001 |
| Male sex, No. (%) | 23 (46) | 32 (68) | 32 (67) | .028 |
| BMI, kg/m2 | 24.9±4.8 | 24.6±5.9 | 23.2±7.5 | .368 |
| Nocturnal capnography | ||||
| Mean tcCO2, mm Hg | 39.5±4.2 | 44.3±1.9 | 52.2±7.0 | <.001 |
| Peak tcCO2, mm Hg | 43.3±4.2 | 49.5±2.6 | 60.0±11.7 | <.001 |
| Time with tcCO2>50mm Hg, % | 1.5±10.6 | 2.0±4.9 | 53.4±31.5 | <.001 |
| Mean SpO2, % | 95.1±1.6 | 94.7±2.5 | 94.0±3.4 | .087 |
| Time with SpO2<90%, min | 9.3±36.0 | 26.6±69.4 | 57.1±116.7 | .015 |
| ODI, events/h | 8.2±9.2 | 9.5±11.0 | 16.0±19.4 | .015 |
| Pulmonary function testing | ||||
| VC, L | 2.7±0.9 | 2.6±0.9 | 2.4±1.1 | .303 |
| VC, % predicted | 75.7±24.3 | 64.9±23.6 | 57.1±24.3 | <.001 |
| Supine VC, L | 2.5±0.9 | 2.5±1.1 | 2.2±1.1 | .285 |
| Supine VC, % predicted | 72.1±22.2 | 61.1±25.0 | 51.8±21.6 | <.001 |
| MEP, cm H2O | 59.0±32.9 | 53.3±27.0 | 46.9±27.5 | .134 |
| MIP, cm H2O | 48.7±26.9 | 44.8±23.5 | 40.1±22.6 | .233 |
| SNIP, cm H2O | 49.3±21.1 | 47.4±22.0 | 38.7±18.7 | .041 |
| Blood gas parameters | ||||
| PCO2, mm Hg | 38.0±5.4 | 43.8±4.8 | 46.7±6.9 | <.001 |
| HCO3−, mmol/L | 24.9±2.8 | 26.9±2.4 | 27.9±3.1 | <.001 |
| Hypercapnic burden, mm Hg s | 0 | 2.5×10⁴±2.5×10⁴ | 3.7×10⁵±4.4×10⁵ | <.001 |
Values are presented as mean±SD unless otherwise indicated.
BMI, body mass index; HCO3−, bicarbonate; MEP, maximal expiratory pressure; MIP, maximal inspiratory pressure; NMD, neuromuscular disease; ODI, oxygen desaturation index; PCO2, daytime partial pressure of carbon dioxide measured by blood gas analysis; SNIP, sniff nasal inspiratory pressure; SpO2, oxygen saturation measured by pulse oximetry; tcCO2, transcutaneous carbon dioxide tension; tcCO2bur, hypercapnic burden derived from tcCO2 monitoring; VC, vital capacity.
Group 1 comprised patients with no hypercapnic burden. Among patients with a positive hypercapnic burden, the median tcCO2bur was used to define group 2 (low tcCO2bur, <8.3×10⁴mmHgs) and group 3 (high tcCO2bur, ≥8.3×10⁴mmHgs). Groups were compared using analysis of variance. Statistical significance was defined as P<.05.
Significant differences were also found in several PFT parameters. Supine VC and VC were significantly lower in group 3; P<.001 for both comparisons. Sniff nasal inspiratory pressure was also significantly lower in group 3; P=.041 (Table 1). The percentage of time with SpO2<90% and oxygen desaturation index were significantly higher in group 3. Patients in group 3 were significantly younger. No significant differences in body mass index were observed among the groups (Table 1).
Descriptive data on patient outcomes, including NIV and prognostic variables, according to tcCO2bur level are provided in the online Supplementary data (Supplementary Results and Supplementary Figs. 4–6). These analyses are descriptive and should not be interpreted as demonstrating an independent association.
This study demonstrates that measurement of hypercapnic burden is feasible. During the course of the study, another research group formalized the concept of hypercapnic burden in 9 patients with obesity hypoventilation syndrome [13]. In that study, hypercapnic burden, calculated as the cumulative area of tcCO2 above a predefined threshold during sleep, was technically feasible, reproducible, and potentially more informative than isolated mean or peak tcCO2 measurements.
There is a lack of consensus regarding biomarkers for chronic respiratory failure. Nevertheless, nocturnal hypercapnia has emerged as a clinically meaningful prognostic indicator, particularly in neuromuscular disorders. In mechanically ventilated patients with NMDs, Ogna et al. [11] investigated the prognostic value of residual hypoventilation measured using nocturnal tcCO2 monitoring. They found that residual hypoventilation assessed using tcCO2 was significantly associated with adverse events, including death and admission to the intensive care unit for respiratory events, whereas oximetry was not. Our study identified strong correlations between tcCO2bur and conventional tcCO2 thresholds commonly used in clinical practice and the literature.
Our results showed weak correlations between tcCO2bur and both PFT and blood gas parameters. However, a study involving 128 patients with NMDs showed, after reviewing the different definitions of alveolar hypoventilation, that VC was a less informative prognostic marker than nocturnal hypercapnia [5].
Blood gas analysis is also less sensitive than tcCO2 monitoring for identifying nocturnal hypoventilation. In a study by Georges et al. [14], nocturnal tcCO2 monitoring detected nocturnal hypoventilation in patients with NMDs or restrictive thoracic disorders despite normal arterial blood gas and nocturnal oximetry results in 30% of cases. Accordingly, the limited correlations between tcCO2bur and standard pulmonary function and blood gas measurements do not undermine the potential value of this novel biomarker.
This study has several limitations. First, because there is no universally accepted reference standard for diagnosing nocturnal alveolar hypoventilation, our analyses relied on conventional measurements of nocturnal and daytime hypercapnia. This precluded definitive conclusions regarding the diagnostic performance of hypercapnic burden.
Second, the retrospective design may have resulted in underestimation of MaCRED because the Cohort360 database captures only events managed within our institution. Missing data also limited the assessment of ventilatory management and adherence to treatment. Consequently, the lower MaCRED rate observed among patients with the highest tcCO2bur in group 3 may partly reflect more appropriate ventilatory management.
Third, the heterogeneity of the neuromuscular disorders included in the study may limit the generalisability of the findings and preclude disease-specific conclusions. However, this heterogeneity also highlights the need for robust biomarkers that can be applied across different neuromuscular conditions.
Finally, we focused exclusively on hypercapnic burden without accounting for concomitant hypoxic burden. The cardiovascular consequences of hypoxic burden are well established and may have contributed to the higher MaCRED rate observed among patients with isolated obstructive sleep apnoea [15,16].
We developed a novel algorithm for quantifying hypercapnic burden from transcutaneous CO2 recordings by integrating both the duration and severity of nocturnal hypercapnia into a single metric. In this exploratory study, hypercapnic burden was associated with established markers of respiratory impairment, supporting its potential utility as a complementary measure of nocturnal alveolar hypoventilation in patients with neuromuscular disorders.
However, given the retrospective design, the heterogeneous study population, and the absence of a validated reference standard for nocturnal alveolar hypoventilation, these findings should be considered hypothesis-generating.
Because physiological markers that better reflect the severity and heterogeneity of nocturnal respiratory abnormalities in patients with NMDs are needed, future prospective studies should determine whether hypercapnic burden represents a clinically relevant biomarker of disease severity, prognosis, and response to treatment. They should also investigate whether its integration into clinical practice could influence therapeutic decision-making and improve patient outcomes.
Future studies should validate hypercapnic burden against clinically meaningful outcomes, determine its incremental value beyond conventional measurements, investigate its relationship with hypoxic burden, and assess its applicability in homogeneous neuromuscular cohorts and other disorders associated with nocturnal alveolar hypoventilation.
Authors’ contributionsConceptualisation: S.B., A.L., I.B., G.B., and H.P. Data curation: S.B., P.D., and A.P. Formal analysis: S.B., P.D., M.A.M., P.T., M.P., H.P., and A.L. Funding acquisition: none. Methodology: S.B., A.L., and I.B. Supervision: M.P., G.B., H.P., and A.L. Validation: all authors. Writing—original draft: S.B., P.D., M.A.M., P.T., and A.L. Writing—review and editing: all authors.
Research involving human participantsAll procedures involving human participants were performed in accordance with the ethical standards of the relevant institutional and national research committees and with the 1964 Declaration of Helsinki and its subsequent amendments or comparable ethical standards.
Informed consentThe study followed the ethical procedures applicable to research involving routine care data under the MR-004 reference methodology. Specific patient information was provided in accordance with national regulations. All patients were fully informed about the nature of the study and were given the opportunity to object to the use of their medical data. No patient objected to participation.
Declaration on the use of generative artificial intelligence and AI-assisted technologiesDuring preparation of this manuscript, the authors used ChatGPT to improve the English language and readability of the text under human supervision. The authors subsequently reviewed and edited the content as necessary and take full responsibility for the content of the published article.
FundingNone declared.
Data availability statementThe datasets generated and/or analyzed during the current study are available from the corresponding author upon reasonable request.
Conflicts of interestThe authors certify that they have no affiliations with or involvement in any organization or entity with any financial interest, including honoraria, educational grants, participation in speakers’ bureaus, membership, employment, consultancies, stock ownership or other equity interests, expert testimony, or patent-licensing arrangements, related to the subject matter or materials discussed in this manuscript.
We extend our special thanks to the sleep unit nurses, Marie, Laure, and Elsa.
The followings are the supplementary data tot his article:









