




Bronchiectasis is a chronic lung disease characterised by permanent airway dilation, often accompanied by chronic bacterial infections [1]. It has a heterogeneous aetiology, although many cases remain idiopathic [2]. Disease severity assessment is essential, and multidimensional scores have been developed to predict clinical outcomes [3,4].
Chronic airway infection drives disease progression, influencing symptoms, exacerbation frequency and clinical outcomes [1]. Among pathogens, Pseudomonas aeruginosa is particularly relevant due to its association with increased morbidity and mortality, making early eradication after first isolation a key clinical objective [5–7].
In cystic fibrosis, eradication of P. aeruginosa is well established, with evidence supporting inhaled antibiotics with or without systemic therapy to reduce the risk of chronic infection [8]. Based on this evidence and expert consensus, international guidelines, recommend eradication treatment after a first isolation of P. aeruginosa in bronchiectasis [5–7]. However, eradication remains challenging due to intrinsic bacterial factors [9,10].
Diverse eradication strategies have been explored, including oral, intravenous and inhaled antibiotics [5], but evidence remains limited and the optimal regimen is unclear [11,12].
We conducted a retrospective, multicentre observational study across five Portuguese hospitals, including adult patients (≥18 years) with non-cystic fibrosis bronchiectasis and a first documented isolation of P. aeruginosa between January 2019 and December 2023.
Bronchiectasis diagnosis was established by computed tomography. Patients were eligible if they had a first documented isolation of P. aeruginosa and subsequently received an eradication regimen consisting of systemic (oral or intravenous) and/or inhaled antibiotics. All initial isolates were susceptible to the prescribed antibiotics, and all patients ultimately received active therapy based on susceptibility results.
Microbiological identification of P. aeruginosa was performed using standard respiratory culture techniques. Respiratory samples were obtained from spontaneous sputum or bronchoalveolar lavage according to clinical judgement; bronchoalveolar lavage was mainly performed in patients unable to produce sputum or when sputum samples were considered inadequate. Follow-up sampling was not standardised across centres. The primary outcome was bacteriological eradication, defined as the absence of P. aeruginosa isolation within 12 months after treatment [13]. Eradication required at least one documented negative respiratory culture during this period, and all patients classified as eradicated had microbiological confirmation. Secondary outcomes included exacerbations and hospitalisations within 12 months.
Statistical analysis was performed using SPSS® version 21.0. Univariate and multivariable analyses were conducted using negative binomial and logistic regression. A p-value<0.05 was considered statistically significant. The study was approved by the Ethics Committees of all participating centres, with waiver of informed consent.
A total of 147 patients met the inclusion criteria and were analysed. The cohort had a balanced sex distribution (51.0% male) and a median age of 64 years.
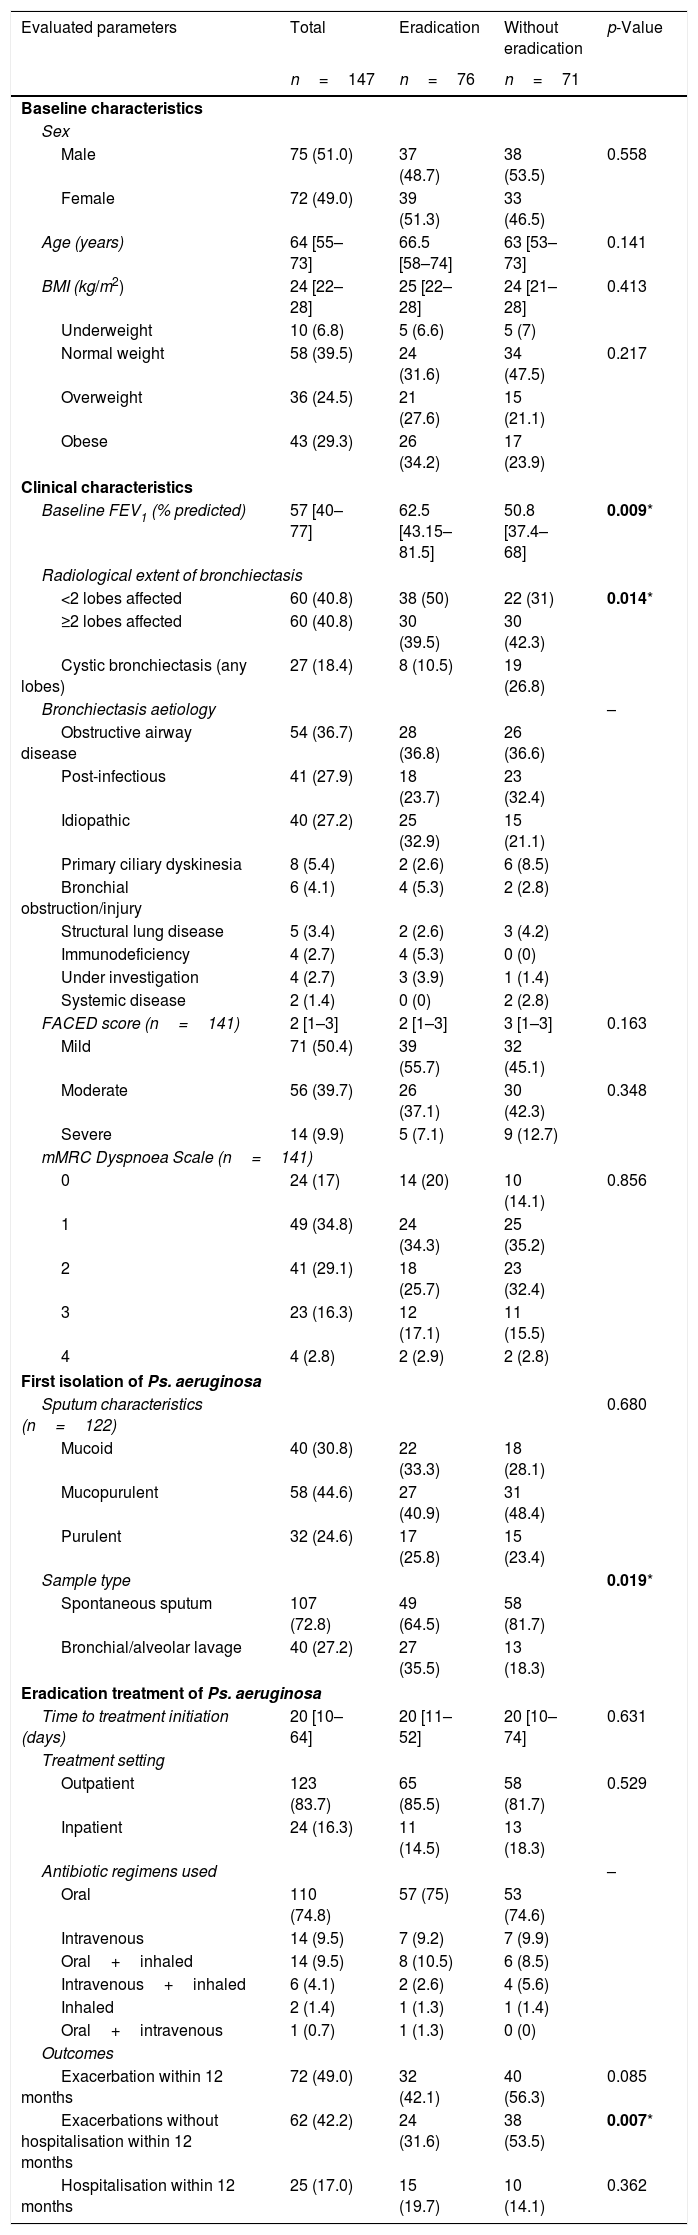
Baseline demographic and clinical characteristics were compared between patients who achieved successful P. aeruginosa eradication and those who failed. Regarding demographic factors, sex, age, and body mass index were similar between the two groups, showing no statistically significant differences. The complete baseline characteristics of the study cohort, including clinical parameters (such as baseline FEV1 and radiological extent of bronchiectasis, aetiological distribution, FACED severity categories, mMRC dyspnoea scores) and the context of the first P. aeruginosa isolation (sputum characteristics and sample site), details of the eradication treatment regimen used, and secondary outcomes in terms of exacerbations and hospitalizations within 12 months, are comprehensively detailed in Table 1.
Clinical and therapeutic data of bronchiectasis patients with primary infection by Pseudomonas aeruginosa undergoing eradication treatment.
| Evaluated parameters | Total | Eradication | Without eradication | p-Value |
|---|---|---|---|---|
| n=147 | n=76 | n=71 | ||
| Baseline characteristics | ||||
| Sex | ||||
| Male | 75 (51.0) | 37 (48.7) | 38 (53.5) | 0.558 |
| Female | 72 (49.0) | 39 (51.3) | 33 (46.5) | |
| Age (years) | 64 [55–73] | 66.5 [58–74] | 63 [53–73] | 0.141 |
| BMI (kg/m2) | 24 [22–28] | 25 [22–28] | 24 [21–28] | 0.413 |
| Underweight | 10 (6.8) | 5 (6.6) | 5 (7) | |
| Normal weight | 58 (39.5) | 24 (31.6) | 34 (47.5) | 0.217 |
| Overweight | 36 (24.5) | 21 (27.6) | 15 (21.1) | |
| Obese | 43 (29.3) | 26 (34.2) | 17 (23.9) | |
| Clinical characteristics | ||||
| Baseline FEV1 (% predicted) | 57 [40–77] | 62.5 [43.15–81.5] | 50.8 [37.4–68] | 0.009* |
| Radiological extent of bronchiectasis | ||||
| <2 lobes affected | 60 (40.8) | 38 (50) | 22 (31) | 0.014* |
| ≥2 lobes affected | 60 (40.8) | 30 (39.5) | 30 (42.3) | |
| Cystic bronchiectasis (any lobes) | 27 (18.4) | 8 (10.5) | 19 (26.8) | |
| Bronchiectasis aetiology | – | |||
| Obstructive airway disease | 54 (36.7) | 28 (36.8) | 26 (36.6) | |
| Post-infectious | 41 (27.9) | 18 (23.7) | 23 (32.4) | |
| Idiopathic | 40 (27.2) | 25 (32.9) | 15 (21.1) | |
| Primary ciliary dyskinesia | 8 (5.4) | 2 (2.6) | 6 (8.5) | |
| Bronchial obstruction/injury | 6 (4.1) | 4 (5.3) | 2 (2.8) | |
| Structural lung disease | 5 (3.4) | 2 (2.6) | 3 (4.2) | |
| Immunodeficiency | 4 (2.7) | 4 (5.3) | 0 (0) | |
| Under investigation | 4 (2.7) | 3 (3.9) | 1 (1.4) | |
| Systemic disease | 2 (1.4) | 0 (0) | 2 (2.8) | |
| FACED score (n=141) | 2 [1–3] | 2 [1–3] | 3 [1–3] | 0.163 |
| Mild | 71 (50.4) | 39 (55.7) | 32 (45.1) | |
| Moderate | 56 (39.7) | 26 (37.1) | 30 (42.3) | 0.348 |
| Severe | 14 (9.9) | 5 (7.1) | 9 (12.7) | |
| mMRC Dyspnoea Scale (n=141) | ||||
| 0 | 24 (17) | 14 (20) | 10 (14.1) | 0.856 |
| 1 | 49 (34.8) | 24 (34.3) | 25 (35.2) | |
| 2 | 41 (29.1) | 18 (25.7) | 23 (32.4) | |
| 3 | 23 (16.3) | 12 (17.1) | 11 (15.5) | |
| 4 | 4 (2.8) | 2 (2.9) | 2 (2.8) | |
| First isolation of Ps. aeruginosa | ||||
| Sputum characteristics (n=122) | 0.680 | |||
| Mucoid | 40 (30.8) | 22 (33.3) | 18 (28.1) | |
| Mucopurulent | 58 (44.6) | 27 (40.9) | 31 (48.4) | |
| Purulent | 32 (24.6) | 17 (25.8) | 15 (23.4) | |
| Sample type | 0.019* | |||
| Spontaneous sputum | 107 (72.8) | 49 (64.5) | 58 (81.7) | |
| Bronchial/alveolar lavage | 40 (27.2) | 27 (35.5) | 13 (18.3) | |
| Eradication treatment of Ps. aeruginosa | ||||
| Time to treatment initiation (days) | 20 [10–64] | 20 [11–52] | 20 [10–74] | 0.631 |
| Treatment setting | ||||
| Outpatient | 123 (83.7) | 65 (85.5) | 58 (81.7) | 0.529 |
| Inpatient | 24 (16.3) | 11 (14.5) | 13 (18.3) | |
| Antibiotic regimens used | – | |||
| Oral | 110 (74.8) | 57 (75) | 53 (74.6) | |
| Intravenous | 14 (9.5) | 7 (9.2) | 7 (9.9) | |
| Oral+inhaled | 14 (9.5) | 8 (10.5) | 6 (8.5) | |
| Intravenous+inhaled | 6 (4.1) | 2 (2.6) | 4 (5.6) | |
| Inhaled | 2 (1.4) | 1 (1.3) | 1 (1.4) | |
| Oral+intravenous | 1 (0.7) | 1 (1.3) | 0 (0) | |
| Outcomes | ||||
| Exacerbation within 12 months | 72 (49.0) | 32 (42.1) | 40 (56.3) | 0.085 |
| Exacerbations without hospitalisation within 12 months | 62 (42.2) | 24 (31.6) | 38 (53.5) | 0.007* |
| Hospitalisation within 12 months | 25 (17.0) | 15 (19.7) | 10 (14.1) | 0.362 |
Data presented as n (%) or median [IQR]. FEV1: forced expiratory volume in 1second; BMI: body mass index; mMRC: Modified Medical Research Council scale; FACED: bronchiectasis severity score.
Obstructive airway disease was the most frequent underlying aetiology, accounting for more than one-third of all cases (n=54, 36.7%), followed by idiopathic and post-infectious bronchiectasis. Most patients reported mild-to-moderate dyspnoea (mMRC 1–2: n=90/141, 63.8%), and FACED severity was predominantly mild (n=71/141, 50.4%), with neither measure differing significantly between patients who achieved eradication and those who did not.
Functional and radiological markers of disease severity differed between groups. Patients with successful eradication exhibited significantly better baseline lung function, with a median FEV1 of 62.5%, compared with 50.8% in those who failed eradication (p=0.009) (Supplementary Fig. 1). Radiological disease was also less extensive in this group (p=0.014). In multivariable analysis, cystic bronchiectasis remained independently associated with a lower likelihood of eradication (OR 0.28; p=0.012), while baseline FEV1 maintained a positive association with eradication success (OR 1.02; p=0.046) (Supplementary Table 1).
With respect to microbiological evaluation, sputum purulence categories (mucoid, mucopurulent or purulent) did not differ significantly between the eradication and non-eradication groups. However, the type of respiratory sample used for the first detection of P. aeruginosa demonstrated a statistically significant association with outcome. Patients whose initial isolation was obtained via bronchoalveolar lavage were more likely to achieve subsequent eradication, whereas those diagnosed through spontaneous sputum were less likely to clear the organism (p=0.019).
Eradication therapy was initiated a median of 20 days after first isolation, mainly in the outpatient setting (n=123, 83.7%). Oral antibiotic regimens represented the majority of eradication strategies used in this cohort, followed by intravenous antibiotics and combined oral-inhaled approaches. The distribution of treatment modalities was similar between patients with and without eradication, indicating that treatment regimens alone did not differentiate the two groups. Systemic antibiotic courses lasted 14–21 days. The median duration of inhaled antibiotic therapy was 7.2 months, with treatment discontinued in four patients due to bronchospasm.
Overall, bacteriological eradication within 12 months was achieved in 51.7% of patients. During follow-up, the proportion of patients experiencing ≥1 non-hospitalized exacerbation was lower in the eradication group (31.6% vs 53.5%, p=0.007). Differences in the total number of exacerbations did not reach statistical significance (p=0.085). Hospitalisation rates were similar between groups (19.7% vs 14.1%, p=0.362). Further analysis using negative binomial regression did not confirm any significant association between eradication and exacerbation rates (Supplementary Table 2).
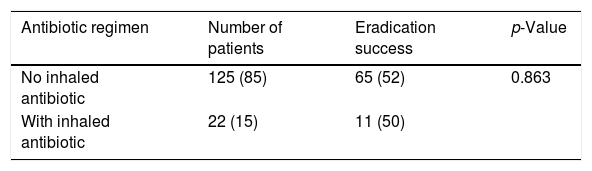
Eradication rates varied across therapeutic categories, with 52.0% (n=65/125) in patients treated without inhaled antibiotics and 50.0% (n=11/22) in those receiving inhaled antibiotic-based regimens. Specifically, eradication was achieved in 47.1% (n=8/17) of patients treated with inhaled colistimethate and in 60.0% (n=3/5) of those receiving inhaled tobramycin. Regimens combining oral fluoroquinolones with inhaled antibiotics resulted in a 57.1% (n=8/14) success rate. Although these differences suggest potential variation in clinical performance between antibiotic strategies, no statistically significant difference was found when comparing eradication rates across treatment groups (p=0.863) (Table 2 and Supplementary Table 3).
Eradication success according to antibiotic regimen.
| Antibiotic regimen | Number of patients | Eradication success | p-Value |
|---|---|---|---|
| No inhaled antibiotic | 125 (85) | 65 (52) | 0.863 |
| With inhaled antibiotic | 22 (15) | 11 (50) |
Data presented as n (%). Percentages are calculated based on the total study population (n=147). A simplified classification according to the use of inhaled antibiotics is shown; detailed treatment regimens are provided in Supplementary Table 3.
The present multicentre retrospective study provides real-world data on eradication treatment following a first P. aeruginosa isolation in adults with non-cystic fibrosis bronchiectasis in Portugal. The observed eradication rate (51.7%) was higher than the approximately 40% reported in recent meta-analyses [12], possibly reflecting differences in disease severity, follow-up, treatment strategies and definitions. The sex distribution was nearly balanced, contrasting with the female predominance usually reported, which may reflect local population characteristics or differences in underlying aetiologies [5].
Previous pooled analyses have suggested a possible advantage of combining systemic and inhaled antibiotics, although the available evidence remains limited [12]. In our study, eradication rates were numerically similar across treatment strategies with no statistically significant differences between regimens. However, subgroup sizes were small, and treatment allocation was not randomised, raising the possibility of limited statistical power and confounding by indication.
A relevant finding was the association between milder disease and higher likelihood of eradication. Patients with better baseline lung function and less extensive radiological involvement were more likely to achieve eradication, supporting the rationale for early microbiological surveillance.
We also observed an association between sample type of the first isolation and eradication, with higher success in patients diagnosed by bronchoalveolar lavage. This may reflect earlier detection, lower bacterial burden or improved lower-airway sampling accuracy; however, this association should be interpreted cautiously given potential selection and surveillance biases in a retrospective design.
In our cohort, eradication was not associated with exacerbation rates within 12 months. Although eradication was initially associated with fewer non-hospitalised exacerbations, this finding was not confirmed in negative binomial regression.
Eradication rates in bronchiectasis remain lower than those typically achieved in cystic fibrosis [14,15]. Differences in patient age, comorbidity burden, background therapies, and sputum monitoring likely contribute to this discrepancy.
This study has limitations inherent to its retrospective real-world design, including heterogeneity in microbiological sampling and the absence of a standardised eradication protocol. Microbiological follow-up was not systematic, and some patients may have had fewer cultures during follow-up, potentially under-detecting persistent infection and overestimating eradication. In addition, information on prior disease burden, previous treatment exposure, clinical status at the time of microbiological sampling, and other clinically relevant outcomes was not systematically collected, which may limit the interpretation of the broader clinical impact of eradication. Furthermore, only patients receiving eradication therapy were included, which may introduce selection bias, and some subgroup analyses should be interpreted with caution due to small sample sizes.
Despite these limitations, this multicentre real-world study provides evidence that approximately half of patients achieved eradication after first P. aeruginosa isolation, more frequently in those with milder disease. No regimen showed clear superiority, although differences cannot be excluded due to small subgroups and non-random treatment allocation. These findings support the need for prospective studies to define optimal eradication strategies using standardised definitions and follow-up.
Author contributionsThis multicentre study, conducted across five hospitals, required coordinated collaboration across institutions and the involvement of multiple investigators throughout the different stages of the project. The study was designed by Dr. Pais, Dr. Sanches and Dr. Pascoal, and all authors contributed to patient recruitment and data collection. Dr. Gigante performed the statistical analysis. The first draft of the manuscript was prepared by Dr. Pais, and all remaining authors critically revised the manuscript. All authors contributed to the final version of the paper and approved it for submission.
Artificial intelligence involvementNo artificial intelligence tools were used to generate scientific content, data analysis or results in this manuscript. Artificial intelligence tools were only used for language refinement and editorial assistance.
Funding of the researchThis research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Conflicts of interestThe authors declare not to have any conflicts of interest that may be considered to influence directly or indirectly the content of the manuscript.
The authors would like to thank the clinical teams and staff at the participating hospitals for their support in patient management and data collection.
The followings are the supplementary data to this article:









