






To assess associations of Enterobacterales isolation and prognostic nutritional index (PNI) with mechanical ventilation and long-term mortality in bronchiectasis exacerbations.
MethodsWe conducted a retrospective cohort study of bronchiectasis exacerbations at a university-affiliated tertiary hospital in China between January 2009 and July 2024. Patients were classified into Enterobacterales and non-Enterobacterales groups. The primary outcomes were long-term all-cause and cause-specific mortality; secondary outcomes were invasive mechanical ventilation (IMV) and non-invasive mechanical ventilation (NIMV). Propensity scores for Enterobacterales isolation were estimated using logistic regression for 1:1 nearest-neighbour matching in mortality analyses. Associations with IMV and NIMV were evaluated in multivariable logistic regression models, and mortality in Cox proportional hazards models. Model adequacy was assessed by examining multicollinearity, calibration, discrimination, and proportional hazards, and E-values were calculated to assess robustness to unmeasured confounding.
ResultsAmong 4634 patients, Enterobacterales were isolated in 228 (4.9%). Enterobacterales isolation was independently associated with IMV (aOR, 2.39; 95%CI, 1.21–6.87; P=.022) and cause-specific mortality over a median follow-up of 72 months (aHR, 1.49; 95%CI, 1.13–2.30; P=.035). In species-level models, Escherichia coli was associated with increased risks of all-cause (aHR, 1.84; 95%CI, 1.18–2.87; P=.007) and cause-specific mortality (aHR, 1.99; 95%CI, 1.13–3.50; P=.017). PNI was inversely associated with risks of IMV, NIMV, and mortality (all P<.001).
ConclusionsEnterobacterales isolation is associated with an increased risk of IMV and cause-specific mortality. In species-level analyses, E. coli was associated with increased risks of all-cause and cause-specific mortality, while elevated PNI was associated with lower mortality.

Bronchiectasis is a chronic, irreversible airway disease characterised by impaired mucociliary clearance, persistent inflammation, and structural damage [1,2]. In a UK population-based study from 2004 to 2013, the point prevalence increased from 350.5 to 566.1 per 100,000 in women and from 301.2 to 485.5 per 100,000 in men [3]. Age-adjusted mortality in patients with bronchiectasis is more than double that of the general population in both sexes [3]. Major aetiologies of bronchiectasis include post-infective disease, post-tuberculosis, and chronic obstructive pulmonary disease (COPD); idiopathic cases predominate [4,5]. Exacerbations are strongly associated with adverse outcomes and are a major driver of the socioeconomic burden of bronchiectasis [6,7]. Previous studies have shown that isolation of Pseudomonas aeruginosa (P. aeruginosa) is an independent risk factor for acute exacerbations, lung function decline, frequent hospitalisations, and increased mortality in bronchiectasis [8,9]. However, the contribution of Enterobacterales to bronchiectasis outcomes remains unclear.
Enterobacterales comprise clinically important Gram-negative pathogens frequently isolated from respiratory specimens in hospitalised patients with bronchiectasis, including Klebsiella pneumoniae (K. pneumoniae), Escherichia coli (E. coli), Enterobacter cloacae complex, and Serratia marcescens[10,11]. Isolation rates of Enterobacterales remain substantial at 3.9%-15.9% despite geographical diversity [9,12]. K. pneumoniae and E. coli possess multiple virulence factors, including siderophore-mediated iron acquisition and mechanisms of immune evasion that promote persistence, while extended-spectrum β-lactamase (ESBL) production and carbapenem resistance further complicate therapy [13,14]. Emerging evidence suggests that Enterobacterales may be associated with increased mortality in bronchiectasis [15,16]. However, existing studies of Enterobacterales in bronchiectasis have generally been limited by small sample sizes, lack of a clearly defined non-Enterobacterales comparator, and scarce data on long-term outcomes or species-level effects. The prognostic nutritional index (PNI) is a simple composite measure of nutritional and immune status [17]. Emerging data suggest that lower PNI is associated with worse outcomes in bronchiectasis [18], but evidence on long-term outcomes remains scarce.
We therefore conducted a large retrospective cohort study of hospitalised patients with bronchiectasis exacerbations to estimate the associations of Enterobacterales isolation and PNI with mechanical ventilation and long-term mortality.
MethodsStudy population and designThis retrospective cohort study was conducted at a university-affiliated tertiary hospital in China between January 2009 and July 2024. We included hospitalised patients with bronchiectasis exacerbations, defined according to Hill et al. [19] Inclusion criteria were as follows: (a) age ≥18 years; and (b) availability of sputum or bronchoalveolar lavage fluid (BALF) specimens. Exclusion criteria were as follows: (a) poor-quality sputum sample; (b) absence of chest high-resolution computed tomography (HRCT); (c) co-isolation of Enterobacterales and Pseudomonas aeruginosa (P. aeruginosa); (d) incomplete data; and (e) initiation of mechanical ventilation within the first 24h of admission. Each patient was included only once; for patients with multiple hospital admissions during the study period, only the first eligible admission was used as the baseline for analysis.
Clinical data were extracted from the electronic medical records, including demographic characteristics (age and sex), comorbidities (e.g., hypertension, diabetes, COPD, pulmonary aspergillosis, and malignant tumour), baseline laboratory parameters obtained within the first 24h of admission, and microbiological findings based on respiratory specimens collected during the initial 24h of admission. Follow-up information, including vital status, was obtained through telephone contact and outpatient visits up to 31 August 2025, or until loss to follow-up or death, whichever occurred first.
The study was conducted in accordance with the Declaration of Helsinki (as revised in 2013). The study was approved by the Ethics Committee on Biomedical Research at West China Hospital of Sichuan University (approval No. 2022455). The requirement for informed consent was waived because of the retrospective design and the use of de-identified data.
Microbiological assessmentDeep sputum or BALF specimens were collected for microbiological culture within the first 24h of admission. Sputum samples with <10 squamous epithelial cells per low-power field (LPF) and >25 white blood cells (WBCs)/LPF were considered acceptable for analysis [20]. Isolated pathogens included P. aeruginosa, Acinetobacter baumannii, Haemophilus influenzae, Staphylococcus aureus, Streptococcus pneumoniae, Enterobacterales, Aspergillus spp., and other organisms. Co-isolation was defined as the isolation of ≥2 of these microorganisms (excluding Candida spp.) from the same respiratory specimen.
Patients were classified into Enterobacterales and non-Enterobacterales groups according to respiratory culture results obtained during admission. Enterobacterales comprised Escherichia coli (E. coli), Klebsiella pneumoniae (K. pneumoniae), Serratia spp., and Enterobacter cloacae (E. cloacae). In subgroup analyses, Enterobacterales isolates were categorised as E. coli, K. pneumoniae, or other Enterobacterales (including Serratia spp. and E. cloacae).
EndpointsPrimary endpoints were all-cause and cause-specific mortality. Secondary endpoints were invasive mechanical ventilation (IMV) and non-invasive mechanical ventilation (NIMV) initiated >24h after hospital admission. Cause-specific mortality was defined as bronchiectasis-related death, determined from medical records and follow-up information, including death due to massive haemoptysis, pneumonia/respiratory infection, or respiratory failure primarily attributable to bronchiectasis or its exacerbation.
Cause-specific mortality was independently adjudicated by 2 investigators who were blinded to the study variables of interest, based on review of medical records and follow-up data, with disagreements resolved by a third senior investigator. Patients receiving only NIMV during hospitalisation were classified into the NIMV group, whereas those receiving IMV at any time were classified into the IMV group.
Statistical analysisStatistical analyses were performed using R (version 4.2.3) and Stata (version 17.0). The Shapiro–Wilk test was used to assess the normality of continuous variables. Normally distributed data are presented as mean±SD, and non-normally distributed data as median (IQR). Between-group differences in continuous variables were assessed using the t test for normally distributed data and the Wilcoxon rank-sum test for non-normally distributed data. Categorical variables are expressed as number (percentage) and were compared using the χ2 test.
Propensity scores for Enterobacterales isolation were estimated using a logistic regression model including baseline demographic, comorbidity, microbiological, and laboratory variables. Patients were matched in a 1:1 ratio by nearest-neighbour matching without replacement, using a calliper width of 0.2 of the SD of the logit of the propensity score. Covariate balance was assessed using standardised mean differences, with an absolute SMD<0.10 indicating adequate balance (Supplementary Appendix, page 1). Propensity score matching was applied only to the mortality analyses to improve baseline comparability for long-term outcome assessment. IMV and NIMV were analysed in the full cohort because the number of ventilation events after matching was too limited for stable regression analyses in the matched sample.
We employed multivariable logistic regression to evaluate associations between Enterobacterales isolation and mechanical ventilation outcomes, and Cox proportional hazards models to assess associations between Enterobacterales and mortality. Overall and cause-specific survival were estimated using Kaplan–Meier curves. Patients lost to follow-up were treated as censored observations, and sensitivity analyses were undertaken to assess the robustness of the findings. Covariates were selected using least absolute shrinkage and selection operator (LASSO) regularisation, informed by clinical relevance (Supplementary Appendix, pages 2–3).
Restricted cubic spline (RCS) analyses were used to assess potential nonlinear associations of PNI with mortality and mechanical ventilation, with adjustment for the same covariates as in the corresponding multivariable models. Nonlinearity was assessed by testing the nonlinear spline terms. All models incorporated robust standard errors to account for potential model misspecification. Model adequacy was evaluated using variance inflation factors to assess multicollinearity, Hosmer–Lemeshow tests for logistic model calibration, and Schoenfeld residuals to test proportional hazards assumptions. Discrimination was assessed using the area under the receiver operating characteristic curve (AUC) for logistic models and Harrell C-index for Cox models. Sensitivity analyses included E-value calculations to quantify robustness to potential unmeasured confounding. A 2-sided P<.05 was considered statistically significant.
ResultsPatient characteristicsA total of 4634 hospitalised patients with bronchiectasis exacerbations were included in the study, of whom 228 (4.9%) were in the Enterobacterales group and 4406 (95.1%) were in the non-Enterobacterales group (Fig. S1 in the Supplementary Appendix). The median age was 58.6 years, and 51.5% of patients were male.
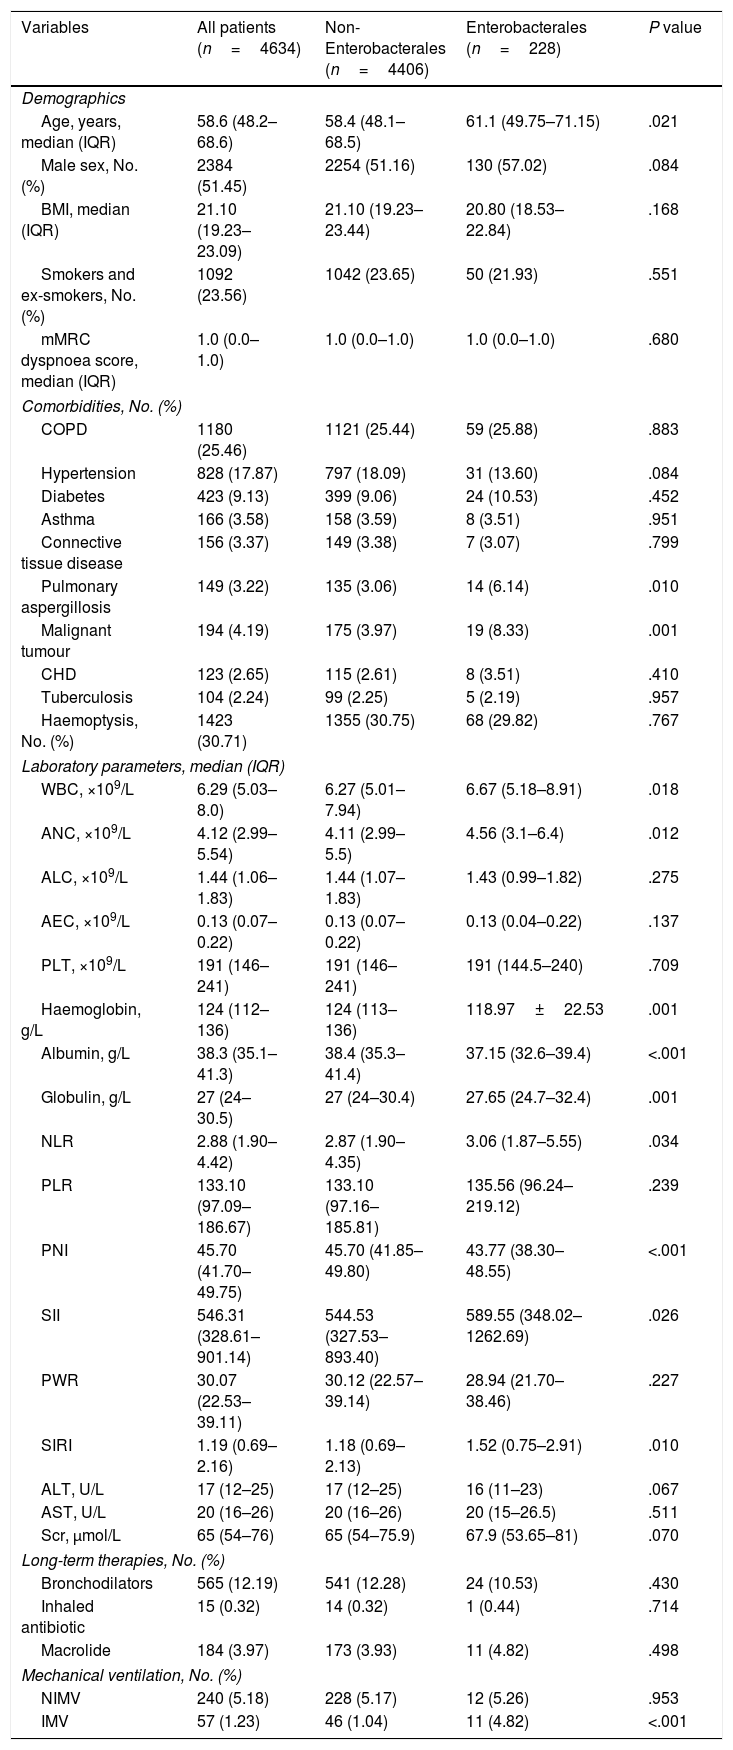
Pulmonary aspergillosis (6.1% vs 3.1%; P=.010) and malignancy (8.3% vs 4.0%; P=.001) were more prevalent in patients with Enterobacterales isolation. In the Enterobacterales group, the neutrophil-to-lymphocyte ratio (NLR), systemic immune-inflammation index (SII), and systemic inflammation response index (SIRI) were higher, whereas the prognostic nutritional index (PNI) was lower (43.77 vs 45.70; P<.001). IMV was more frequent in patients with Enterobacterales isolation (4.8% vs 1.0%; P<.001).
Detailed baseline characteristics are presented in Table 1. After 1:1 propensity score matching, baseline demographics, comorbidities, and laboratory parameters were well balanced between the 2 groups. During follow-up, cause-specific mortality was higher in the Enterobacterales group than in the non-Enterobacterales group (25.4% vs 18.0%; P=.053), although this difference did not reach conventional statistical significance (Table S1 in the Supplementary Appendix).
Characteristics and clinical outcomes of included patients before matching.
| Variables | All patients (n=4634) | Non-Enterobacterales (n=4406) | Enterobacterales (n=228) | P value |
|---|---|---|---|---|
| Demographics | ||||
| Age, years, median (IQR) | 58.6 (48.2–68.6) | 58.4 (48.1–68.5) | 61.1 (49.75–71.15) | .021 |
| Male sex, No. (%) | 2384 (51.45) | 2254 (51.16) | 130 (57.02) | .084 |
| BMI, median (IQR) | 21.10 (19.23–23.09) | 21.10 (19.23–23.44) | 20.80 (18.53–22.84) | .168 |
| Smokers and ex-smokers, No. (%) | 1092 (23.56) | 1042 (23.65) | 50 (21.93) | .551 |
| mMRC dyspnoea score, median (IQR) | 1.0 (0.0–1.0) | 1.0 (0.0–1.0) | 1.0 (0.0–1.0) | .680 |
| Comorbidities, No. (%) | ||||
| COPD | 1180 (25.46) | 1121 (25.44) | 59 (25.88) | .883 |
| Hypertension | 828 (17.87) | 797 (18.09) | 31 (13.60) | .084 |
| Diabetes | 423 (9.13) | 399 (9.06) | 24 (10.53) | .452 |
| Asthma | 166 (3.58) | 158 (3.59) | 8 (3.51) | .951 |
| Connective tissue disease | 156 (3.37) | 149 (3.38) | 7 (3.07) | .799 |
| Pulmonary aspergillosis | 149 (3.22) | 135 (3.06) | 14 (6.14) | .010 |
| Malignant tumour | 194 (4.19) | 175 (3.97) | 19 (8.33) | .001 |
| CHD | 123 (2.65) | 115 (2.61) | 8 (3.51) | .410 |
| Tuberculosis | 104 (2.24) | 99 (2.25) | 5 (2.19) | .957 |
| Haemoptysis, No. (%) | 1423 (30.71) | 1355 (30.75) | 68 (29.82) | .767 |
| Laboratory parameters, median (IQR) | ||||
| WBC, ×109/L | 6.29 (5.03–8.0) | 6.27 (5.01–7.94) | 6.67 (5.18–8.91) | .018 |
| ANC, ×109/L | 4.12 (2.99–5.54) | 4.11 (2.99–5.5) | 4.56 (3.1–6.4) | .012 |
| ALC, ×109/L | 1.44 (1.06–1.83) | 1.44 (1.07–1.83) | 1.43 (0.99–1.82) | .275 |
| AEC, ×109/L | 0.13 (0.07–0.22) | 0.13 (0.07–0.22) | 0.13 (0.04–0.22) | .137 |
| PLT, ×109/L | 191 (146–241) | 191 (146–241) | 191 (144.5–240) | .709 |
| Haemoglobin, g/L | 124 (112–136) | 124 (113–136) | 118.97±22.53 | .001 |
| Albumin, g/L | 38.3 (35.1–41.3) | 38.4 (35.3–41.4) | 37.15 (32.6–39.4) | <.001 |
| Globulin, g/L | 27 (24–30.5) | 27 (24–30.4) | 27.65 (24.7–32.4) | .001 |
| NLR | 2.88 (1.90–4.42) | 2.87 (1.90–4.35) | 3.06 (1.87–5.55) | .034 |
| PLR | 133.10 (97.09–186.67) | 133.10 (97.16–185.81) | 135.56 (96.24–219.12) | .239 |
| PNI | 45.70 (41.70–49.75) | 45.70 (41.85–49.80) | 43.77 (38.30–48.55) | <.001 |
| SII | 546.31 (328.61–901.14) | 544.53 (327.53–893.40) | 589.55 (348.02–1262.69) | .026 |
| PWR | 30.07 (22.53–39.11) | 30.12 (22.57–39.14) | 28.94 (21.70–38.46) | .227 |
| SIRI | 1.19 (0.69–2.16) | 1.18 (0.69–2.13) | 1.52 (0.75–2.91) | .010 |
| ALT, U/L | 17 (12–25) | 17 (12–25) | 16 (11–23) | .067 |
| AST, U/L | 20 (16–26) | 20 (16–26) | 20 (15–26.5) | .511 |
| Scr, μmol/L | 65 (54–76) | 65 (54–75.9) | 67.9 (53.65–81) | .070 |
| Long-term therapies, No. (%) | ||||
| Bronchodilators | 565 (12.19) | 541 (12.28) | 24 (10.53) | .430 |
| Inhaled antibiotic | 15 (0.32) | 14 (0.32) | 1 (0.44) | .714 |
| Macrolide | 184 (3.97) | 173 (3.93) | 11 (4.82) | .498 |
| Mechanical ventilation, No. (%) | ||||
| NIMV | 240 (5.18) | 228 (5.17) | 12 (5.26) | .953 |
| IMV | 57 (1.23) | 46 (1.04) | 11 (4.82) | <.001 |
IQR, interquartile range; BMI, body mass index; mMRC, modified Medical Research Council; COPD, chronic obstructive pulmonary disease; CHD, coronary heart disease; WBC, white blood cell count; ANC, absolute neutrophil count; ALC, absolute lymphocyte count; AEC, absolute eosinophil count; PLT, platelet count; ALT, alanine aminotransferase; AST, aspartate aminotransferase; Scr, serum creatinine; NLR, neutrophil-to-lymphocyte ratio; PLR, platelet-to-lymphocyte ratio; PNI, prognostic nutritional index (PNI=albumin [g/L]+5×lymphocyte count [×109/L]); SII, systemic immune-inflammation index (SII=platelet×neutrophil/lymphocyte); PWR, platelet-to-white blood cell ratio; SIRI, systemic inflammation response index (SIRI=neutrophil×monocyte/lymphocyte); IMV, invasive mechanical ventilation; NIMV, non-invasive mechanical ventilation.
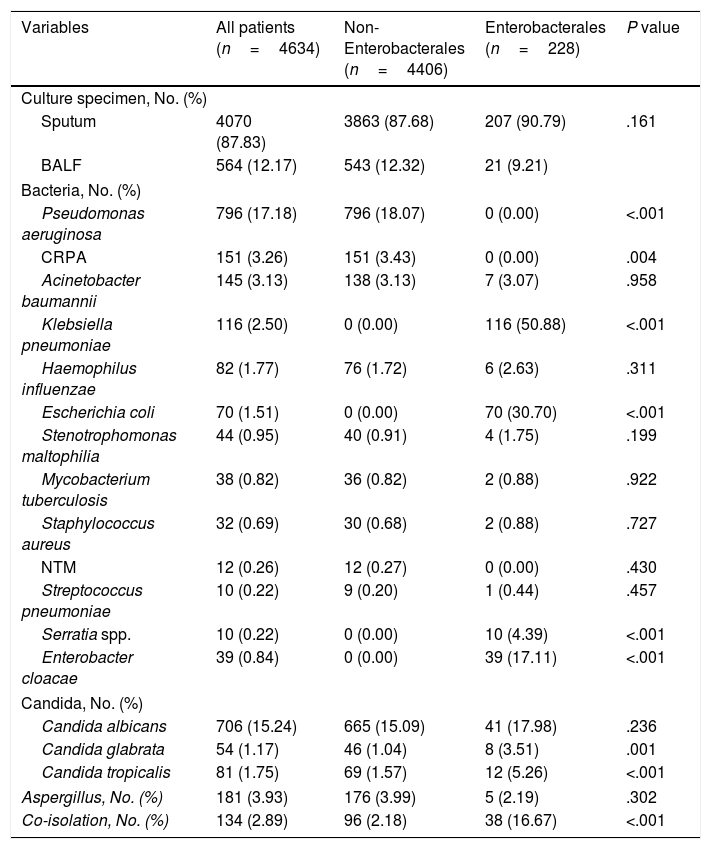
Pathogens were isolated from sputum in 4070 patients (87.8%) and from BALF in 564 (12.2%). Pseudomonas aeruginosa (P. aeruginosa) was the most frequently isolated bacterium, detected in 796 patients (17.2%), and carbapenem-resistant P. aeruginosa (CRPA) in 151 (3.3%). Other bacteria included H. influenzae in 82 patients (1.8%), Stenotrophomonas maltophilia in 44 (1.0%), Mycobacterium tuberculosis in 38 (0.8%), S. aureus in 32 (0.7%), nontuberculous mycobacteria in 12 (0.3%), and S. pneumoniae in 10 (0.2%).
Enterobacterales were isolated in 228 patients (4.9%). Within this group, the predominant species were Klebsiella pneumoniae (K. pneumoniae) in 116 patients (50.9%), Escherichia coli (E. coli) in 70 (30.7%), E. cloacae in 39 (17.1%), and Serratia spp. in 10 (4.4%). Co-isolation was markedly more prevalent in the Enterobacterales group than in the non-Enterobacterales group (16.7% vs 2.2%; P<.001). Candida glabrata and Candida tropicalis were also more common in the Enterobacterales than in the non-Enterobacterales group (3.5% vs 1.0% and 5.3% vs 1.6%, respectively; P=.001 and P<.001, respectively). Detailed microbiological characteristics are shown in Table 2. After 1:1 propensity score matching, microbiological characteristics in the matched cohort are presented in Table S2.
Microbiological characteristics of patients before matching.
| Variables | All patients (n=4634) | Non-Enterobacterales (n=4406) | Enterobacterales (n=228) | P value |
|---|---|---|---|---|
| Culture specimen, No. (%) | ||||
| Sputum | 4070 (87.83) | 3863 (87.68) | 207 (90.79) | .161 |
| BALF | 564 (12.17) | 543 (12.32) | 21 (9.21) | |
| Bacteria, No. (%) | ||||
| Pseudomonas aeruginosa | 796 (17.18) | 796 (18.07) | 0 (0.00) | <.001 |
| CRPA | 151 (3.26) | 151 (3.43) | 0 (0.00) | .004 |
| Acinetobacter baumannii | 145 (3.13) | 138 (3.13) | 7 (3.07) | .958 |
| Klebsiella pneumoniae | 116 (2.50) | 0 (0.00) | 116 (50.88) | <.001 |
| Haemophilus influenzae | 82 (1.77) | 76 (1.72) | 6 (2.63) | .311 |
| Escherichia coli | 70 (1.51) | 0 (0.00) | 70 (30.70) | <.001 |
| Stenotrophomonas maltophilia | 44 (0.95) | 40 (0.91) | 4 (1.75) | .199 |
| Mycobacterium tuberculosis | 38 (0.82) | 36 (0.82) | 2 (0.88) | .922 |
| Staphylococcus aureus | 32 (0.69) | 30 (0.68) | 2 (0.88) | .727 |
| NTM | 12 (0.26) | 12 (0.27) | 0 (0.00) | .430 |
| Streptococcus pneumoniae | 10 (0.22) | 9 (0.20) | 1 (0.44) | .457 |
| Serratia spp. | 10 (0.22) | 0 (0.00) | 10 (4.39) | <.001 |
| Enterobacter cloacae | 39 (0.84) | 0 (0.00) | 39 (17.11) | <.001 |
| Candida, No. (%) | ||||
| Candida albicans | 706 (15.24) | 665 (15.09) | 41 (17.98) | .236 |
| Candida glabrata | 54 (1.17) | 46 (1.04) | 8 (3.51) | .001 |
| Candida tropicalis | 81 (1.75) | 69 (1.57) | 12 (5.26) | <.001 |
| Aspergillus, No. (%) | 181 (3.93) | 176 (3.99) | 5 (2.19) | .302 |
| Co-isolation, No. (%) | 134 (2.89) | 96 (2.18) | 38 (16.67) | <.001 |
BALF, bronchoalveolar lavage fluid; CRPA, carbapenem-resistant Pseudomonas aeruginosa; NTM, non-tuberculous mycobacteria.
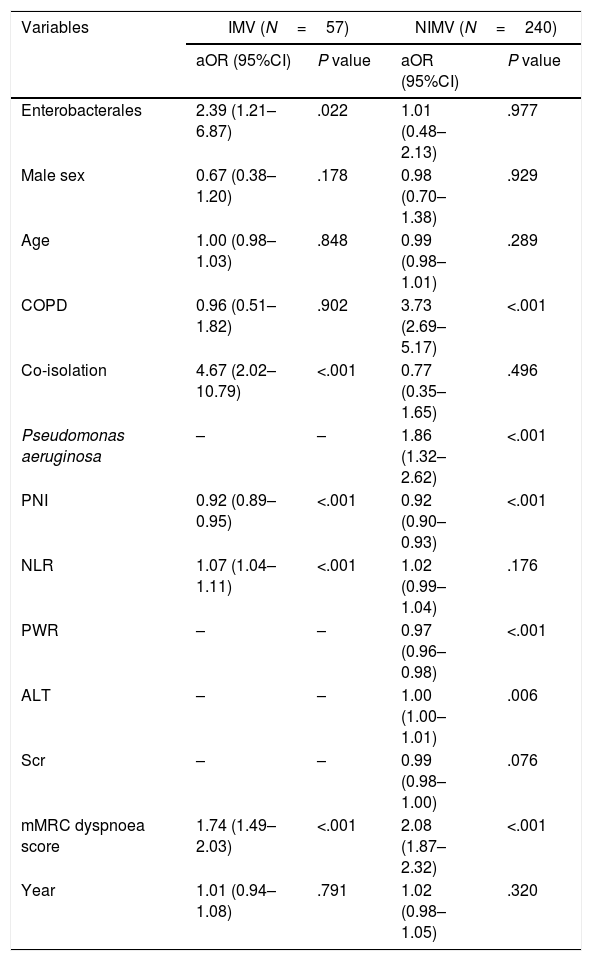
Multivariable logistic regression showed that Enterobacterales isolation was independently associated with IMV (adjusted odds ratio [aOR], 2.39; 95%CI, 1.21–6.87; P=.022), but not with NIMV (aOR, 1.01; 95%CI, 0.48–2.13; P=.977) (Table 3). Co-isolation (aOR, 4.67; 95%CI, 2.02–10.79; P<.001), mMRC dyspnoea score (aOR, 1.74; 95%CI, 1.49–2.03; P<.001), and NLR (aOR, 1.07; 95%CI, 1.04–1.11; P<.001) were also independently associated with increased odds of IMV, whereas PNI was associated with lower odds (aOR, 0.92; 95%CI, 0.89–0.95; P<.001).
Enterobacterales and mechanical ventilation: multivariable logistic regression analysis.
| Variables | IMV (N=57) | NIMV (N=240) | ||
|---|---|---|---|---|
| aOR (95%CI) | P value | aOR (95%CI) | P value | |
| Enterobacterales | 2.39 (1.21–6.87) | .022 | 1.01 (0.48–2.13) | .977 |
| Male sex | 0.67 (0.38–1.20) | .178 | 0.98 (0.70–1.38) | .929 |
| Age | 1.00 (0.98–1.03) | .848 | 0.99 (0.98–1.01) | .289 |
| COPD | 0.96 (0.51–1.82) | .902 | 3.73 (2.69–5.17) | <.001 |
| Co-isolation | 4.67 (2.02–10.79) | <.001 | 0.77 (0.35–1.65) | .496 |
| Pseudomonas aeruginosa | – | – | 1.86 (1.32–2.62) | <.001 |
| PNI | 0.92 (0.89–0.95) | <.001 | 0.92 (0.90–0.93) | <.001 |
| NLR | 1.07 (1.04–1.11) | <.001 | 1.02 (0.99–1.04) | .176 |
| PWR | – | – | 0.97 (0.96–0.98) | <.001 |
| ALT | – | – | 1.00 (1.00–1.01) | .006 |
| Scr | – | – | 0.99 (0.98–1.00) | .076 |
| mMRC dyspnoea score | 1.74 (1.49–2.03) | <.001 | 2.08 (1.87–2.32) | <.001 |
| Year | 1.01 (0.94–1.08) | .791 | 1.02 (0.98–1.05) | .320 |
The symbol “–” indicates not applicable.
IMV, invasive mechanical ventilation; NIMV, non-invasive mechanical ventilation; aOR, adjusted odds ratio; COPD, chronic obstructive pulmonary disease; P aeruginosa, Pseudomonas aeruginosa; PNI, prognostic nutritional index; NLR, neutrophil-to-lymphocyte ratio; PWR, platelet-to-white blood cell ratio; ALT, alanine aminotransferase; AST, aspartate aminotransferase; Scr, serum creatinine; mMRC, modified Medical Research Council.
For NIMV, COPD (aOR, 3.73; 95%CI, 2.69–5.17; P<.001), P. aeruginosa isolation (aOR, 1.86; 95%CI, 1.32–2.62; P<.001), mMRC dyspnoea score (aOR, 2.08; 95%CI, 1.87–2.32; P<.001), and higher ALT levels (aOR, 1.00; 95%CI, 1.00–1.01; P=.006) were associated with a higher risk of NIMV, whereas higher PNI (aOR, 0.92; 95%CI, 0.90–0.93; P<.001) and platelet-to-white blood cell ratio (PWR) (aOR, 0.97; 95%CI, 0.96–0.98; P<.001) were independently associated with a lower risk.
RCS analysis showed an inverse, approximately linear association between PNI and IMV (P for overall<.001; P for nonlinear=.159; Fig. S2A), and a nonlinear association between PNI and NIMV (P for overall<.001; P for nonlinear<.001; Fig. S2B). In the 2-piecewise logistic regression analysis, the estimated inflection point was 41. The association between PNI and NIMV was not significant below this threshold (OR, 0.970; 95%CI, 0.934–1.010; P=.122), whereas above this threshold, each 1-unit increase in PNI was associated with significantly lower odds of NIMV (OR, 0.847; 95%CI, 0.805–0.889; P<.001).
Model diagnostics showed no evidence of problematic multicollinearity (all VIFs≤1.35; Table S3). IMV and NIMV models showed excellent discrimination (AUC, 0.882 and 0.881, respectively; Tables S4 and S5). E-values for the associations of Enterobacterales isolation with IMV and NIMV are reported in Table S6. Logistic regression analyses for IMV and NIMV adjusted for treatment-related variables, including maintenance inhaled bronchodilator, macrolide, and systemic antibiotic therapy, are presented in Table S7.
Overall and cause-specific survival probabilityDuring a median follow-up of 72 months (IQR, 34.5–132), 14 patients in each of the Enterobacterales and non-Enterobacterales groups were lost to follow-up. Overall, 133 patients in the matched cohort (n=456) (29.2%) died, including 99 cause-specific deaths (Table S1).
Kaplan–Meier analysis demonstrated lower cause-specific survival in the Enterobacterales group than in the non-Enterobacterales group (P=.041; Fig. 1). The 1-, 3-, 5-, and 7-year cause-specific survival rates were 94.7%, 86.4%, 80.9%, and 73.8%, respectively, in the Enterobacterales group, compared with 94.7%, 88.4%, 83.9%, and 81.0%, respectively, in the non-Enterobacterales group.

All-cause and cause-specific survival probabilities according to Enterobacterales isolation and species. (A) Cause-specific survival of Enterobacterales and non-Enterobacterales; (B) all-cause survival of Enterobacterales and non-Enterobacterales; (C) cause-specific survival stratified by E. coli, K. pneumoniae, other Enterobacterales, and non-Enterobacterales; (D) all-cause survival stratified by E. coli, K. pneumoniae, other Enterobacterales, and non-Enterobacterales.
In species-level analyses, E. coli was associated with the lowest survival. Both cause-specific (P=.043) and all-cause (P=.016) survival were lower in patients with E. coli isolation than in those with K. pneumoniae or other Enterobacterales. For E. coli, the 1-, 3-, 5-, and 7-year cause-specific survival rates were 95.7%, 81.7%, 76.1%, and 66.2%, respectively, and the all-cause survival rates were 95.7%, 77.3%, 67.2%, and 58.4%, respectively.
Enterobacterales, E. coli, PNI, and mortalityIn multivariable Cox proportional hazards models, Enterobacterales isolation was independently associated with a higher risk of cause-specific mortality (adjusted hazard ratio [aHR], 1.49; 95%CI, 1.13–2.30; P=.035), whereas no significant association was observed with all-cause mortality (Table S8).
Older age (aHR, 1.05; 95%CI, 1.03–1.07; P<.001), COPD (aHR, 1.63; 95%CI, 1.06–2.51; P=.028), mMRC dyspnoea score (aHR, 1.25; 95%CI, 1.06–1.47; P=.007), and malignant tumour (aHR, 1.97; 95%CI, 1.10–3.52; P=.022) were independently associated with a higher risk of cause-specific mortality, whereas higher PNI was associated with a lower risk (aHR, 0.95; 95%CI, 0.92–0.97; P<.001).
In species-level Cox models, E. coli was consistently associated with an increased risk of both cause-specific mortality (aHR, 1.99; 95%CI, 1.13–3.50; P=.017) and all-cause mortality (aHR, 1.84; 95%CI, 1.18–2.87; P=.007), whereas K. pneumoniae and other Enterobacterales were not significantly associated with either outcome (Fig. 2; Tables S9–S11).

Univariable and multivariable Cox proportional hazards analyses of Enterobacterales and all-cause and cause-specific mortality. (A) Univariable Cox model for cause-specific mortality; (B) multivariable Cox model for cause-specific mortality; (C) univariable Cox model for all-cause mortality; and (D) multivariable Cox model for all-cause mortality. Multivariable models were adjusted for age, diabetes, COPD, malignant tumour, pulmonary aspergillosis, co-isolation, mMRC dyspnoea score, calendar year, and PNI.
Higher PNI was independently associated with a lower risk of both cause-specific mortality (aHR, 0.95; 95%CI, 0.92–0.97; P<.001) and all-cause mortality (aHR, 0.95; 95%CI, 0.93–0.97; P<.001). RCS analyses showed inverse associations of PNI with cause-specific and all-cause mortality, with no evidence of significant nonlinearity (P for nonlinear=.085 and .055, respectively; Fig. S3). Similar results were observed in the species-level models (P for nonlinear=.074 and .068, respectively; Fig. S4).
The pattern of covariate effects was similar in the species-level models, with older age, malignant tumour, and COPD associated with higher mortality risk. All Cox models satisfied the proportional hazards assumption and showed no evidence of problematic multicollinearity (mean VIF≈1.12–1.15; Tables S12 and S13). Binary and 4-category Enterobacterales models were well calibrated and demonstrated good discrimination, with Harrell C-index values of 0.785–0.791 for cause-specific mortality and 0.769–0.777 for all-cause mortality (Tables S14 and S17). E-value analyses were performed to assess the potential impact of unmeasured confounding on the associations between Enterobacterales (E. coli) and mortality (Tables S18 and S19). Cox regression analyses for cause-specific and all-cause mortality adjusted for treatment-related variables are shown in Tables S20–S22.
DiscussionIn this large retrospective cohort of patients with bronchiectasis exacerbations, we identified 3 principal findings. First, Enterobacterales isolation was independently associated with an increased risk of IMV and cause-specific mortality. Second, in species-level analyses, the mortality signal was confined to E. coli, whereas K. pneumoniae and other Enterobacterales were not associated with either all-cause or cause-specific mortality. Third, lower PNI was linked to increased risks of IMV, NIMV, all-cause mortality, and cause-specific mortality; RCS analyses indicated a nonlinear pattern for NIMV.
To our knowledge, this is the largest study to date to evaluate Enterobacterales and PNI in relation to clinical deterioration and long-term mortality in bronchiectasis. In our cohort, Enterobacterales isolation was associated with nearly 3-fold higher odds of IMV and a 1.5-fold higher risk of cause-specific but not all-cause mortality. These findings are biologically plausible and consistent with data from the Indian registry, which reported that infection with Gram-negative pathogens, predominantly K. pneumoniae, was independently associated with an approximately 3-fold increase in mortality risk among patients with bronchiectasis [15].
Enterobacterales are also major causes of severe hospital-acquired and healthcare-associated infections, including pneumonia, bloodstream, and intra-abdominal infections [21,22]. They frequently harbour ESBL production and carbapenem resistance, thereby limiting treatment options and delaying the initiation of appropriate targeted therapy; these resistance mechanisms have been associated with excess mortality in previous studies [23,24].
By contrast, the species-level pattern in our cohort differed from that observed in the Indian bronchiectasis registry, which reported that K. pneumoniae was associated with an approximately 3-fold higher mortality risk [15]. In our cohort, K. pneumoniae was not associated with long-term mortality, whereas only E. coli was independently associated with higher all-cause and cause-specific mortality.
Several mechanisms may underlie this discrepancy. First, even after propensity-score matching on measured comorbidities and laboratory indices, isolation of E. coli in sputum or BALF may still reflect unmeasured dimensions of clinical vulnerability, including frailty, greater disease severity, exacerbation burden, extrapulmonary infection, and prior antibiotic exposure, all of which may influence both microbiological isolation patterns and subsequent outcomes [25,26]. Therefore, the observed association may partly reflect residual confounding rather than a pathogen-specific effect alone.
Second, extraintestinal pathogenic E. coli (ExPEC) lineages possess an extensive repertoire of virulence factors, including adhesins, capsular polysaccharides, cytotoxins, and high-affinity siderophore systems, which facilitate colonisation of the lower airways, epithelial adherence, and immune evasion, thereby contributing to more severe respiratory infection [27,28]. Such virulence traits distinguish ExPEC from commensal E. coli and underpin their capacity to cause severe pneumonia as well as bacteraemia and sepsis in vulnerable hosts [29].
Taken together, host vulnerabilities, residual confounding, and ExPEC-specific virulence traits may underlie the observed association between E. coli and excess mortality in our cohort. Enterobacterales isolation, particularly E. coli, may serve as a microbiological marker for risk stratification in hospitalised patients with bronchiectasis exacerbations, identifying those at increased risk of respiratory deterioration and poor long-term outcomes. This finding may therefore support enhanced monitoring, earlier detection of clinical deterioration, and closer post-discharge follow-up.
Enterobacterales isolation in this study should be regarded as culture-based isolation rather than definitive infection. In bronchiectasis, colonisation and infection may exist along a dynamic continuum shaped by host immune status and airway inflammation, with colonisation progressing to clinically significant infection as host defences decline [30]. Serial isolation of the same Enterobacterales species during clinical stability would suggest colonisation, whereas isolation accompanied by symptom worsening, increased sputum purulence or volume, elevated inflammatory markers, or new/progressive radiological abnormalities would favour infection [19]. In patients with impaired host reserve or evolving clinical deterioration, a positive Enterobacterales culture should prompt close monitoring, repeat microbiological assessment, and timely culture-guided antimicrobial optimisation to prevent progression to severe infection [31].
Evidence regarding PNI in bronchiectasis remains limited. A recent single-centre cohort study reported that lower PNI was associated with an increased risk of respiratory-related hospitalisation over 1 year [18]. In line with this, several studies have shown that nutritional markers such as serum albumin and BMI are important determinants of prognosis in bronchiectasis. Low albumin is associated with greater disease severity and an increased risk of respiratory hospitalisation [32,33], while underweight independently predicts all-cause mortality [34]. A recent study using the Controlling Nutritional Status score in bronchiectasis patients undergoing lung resection also linked poorer nutritional status to greater disease severity and more postoperative complications [35]. Previous studies have shown that low PNI is an adverse prognostic factor in nontuberculous mycobacterial lung disease and in acute exacerbations of COPD [36,37].
Our findings extend these observations to bronchiectasis, suggesting that lower PNI is independently associated with mechanical ventilation and long-term mortality. RCS analyses further showed a nonlinear association between PNI and NIMV, with an exploratory inflection point around 41 that may help identify patients requiring closer respiratory monitoring. Derived from serum albumin and lymphocyte count, PNI reflects both nutritional and immune status [38]. Low albumin may indicate systemic inflammation, poor nutritional reserve, and a higher overall disease burden [32], whereas lymphopenia may reflect impaired host defence and reduced capacity to control infection [39]. Accordingly, low PNI may identify patients with nutritional and immunological vulnerability who are at increased risk of respiratory deterioration and poor long-term outcomes.
As a readily available laboratory index, PNI may refine risk stratification and prompt early nutritional assessment and individualised nutritional support. Previous interventional evidence in bronchiectasis suggests that oral nutritional supplementation enriched with β-hydroxy-β-methylbutyrate, when combined with pulmonary rehabilitation, may improve body composition, muscle strength, and health-related quality of life [40]. Future prospective interventional studies should evaluate whether improving PNI may reduce respiratory deterioration and long-term mortality.
This study has several limitations. First, the retrospective single-centre design precluded serial sputum or BALF sampling, limiting our ability to distinguish colonisation from infection. This uncertainty may limit causal interpretation of the observed associations. Second, over the 15-year study period, temporal changes in microbiological testing may have influenced culture-based detection of Enterobacterales, while evolving antimicrobial and respiratory care practices may have affected the use of mechanical ventilation and long-term outcomes. Although calendar year was adjusted for in the multivariable models, residual temporal effects cannot be fully excluded.
Third, the limited number of IMV events may have increased the risk of overfitting and reduced the stability of multivariable estimates. Accordingly, the association between Enterobacterales isolation and IMV should be considered exploratory. In addition, no NIMV events occurred in patients with Enterobacterales species other than Escherichia coli (E. coli) and Klebsiella pneumoniae (K. pneumoniae), precluding reliable assessment of species-specific associations with IMV or NIMV.
Fourth, spirometric data were available in only 11% of patients, precluding accurate calculation of multidimensional bronchiectasis severity scores such as the Bronchiectasis Severity Index (BSI) and FACED score. Although multivariable adjustment and E-value analyses were performed, residual confounding related to disease severity could not be fully excluded. Incomplete capture of disease severity, exacerbation burden, and prior antibiotic exposure may have led to overestimation of the observed associations. Prospective, multicentre studies with serial microbiological sampling and comprehensive bronchiectasis severity assessment are needed to validate and extend these findings.
ConclusionsEnterobacterales isolation was independently associated with an increased risk of IMV and cause-specific mortality in hospitalised patients with bronchiectasis exacerbations. At the species level, E. coli was the only Enterobacterales species independently associated with increased risks of all-cause and cause-specific mortality. PNI showed an inverse relationship with IMV, NIMV, and mortality, underscoring its potential value as a simple composite prognostic marker in bronchiectasis. Prospective multicentre studies are essential to validate these findings and to refine risk stratification in bronchiectasis.
Authors’ contributionsJibo Sun, Dajun Li, Wenting Lv, Jiehao Chen, Xiaoting Chen, Xirui Chen, Xing He, Xiangpeng Wang and Xiang Tong collected the clinical data. Jibo Sun, Donguang Wang, Guanping Liu, and Hong Fan contributed to interpretation of results and revision of the manuscript. Jibo Sun, Donguang Wang, Guanping Liu and Hong Fan wrote the manuscript. Xiang Tong and Hong Fan supervised the conceptualization, writing, and review process of the article. All authors read and approved the final manuscript.
Ethics approval and consent to participateThe study was approved by the Ethics Committee on Biomedical Research at West China Hospital of Sichuan University (approval No. 2022455). The requirement for informed consent was waived due to the retrospective design and the use of de-identified data.
Artificial intelligence involvementThe authors declare that no generative artificial intelligence was used to write this manuscript.
FundingThis work was supported by 2024 Tianfu Qingcheng Program, Sichuan Province (TJZ202454) and National Clinical Research Center for Geriatrics, West China Hospital, Sichuan University (Z2024LC005).
Conflicts of interestNone declared.
Data availabilityData are available from the corresponding author upon reasonable request.
None.
The followings are the supplementary data to this article:










