






Continuous positive airway pressure (CPAP) abolishes apneas in obstructive sleep apnea (OSA), but its long-term vascular associations remain uncertain. Findings from cohorts with coronary artery disease suggested higher CPAP pressures may be associated with endothelial biomarker patterns, raising concerns about potential pro-inflammatory responses in broader OSA populations. We therefore assessed the longitudinal associations of CPAP on endothelial and epithelial biomarkers in OSA patients free of cardiovascular comorbidities.
MethodsIn the EPIOSA study, a 5-year prospective cohort of moderate-to-severe OSA patients and non-OSA controls, plasma angiopoietin-2 (Ang-2), vascular endothelial growth factor (VEGF), Tie-2, and E-selectin were measured at baseline, 1 year, and 5 years. Participants were managed with or without CPAP according to clinical guidelines. Associations between biomarkers and clinical, sleep, and biochemical variables were examined using multivariable regression models.
ResultsAmong 326 participants (OSA: n=195; controls: n=72), CPAP-treated OSA patients (mean usage 6.7±1.1h/night) showed sustained reductions in VEGF at both follow-up visits, independently related to baseline VEGF and waist-to-hip ratio. Ang-2 increased over time in both OSA and control groups, with no association to CPAP pressure or adherence. Body weight and soluble ST2 (sST2) independently predicted baseline Ang-2. Tie-2 and E-selectin showed minimal temporal variation.
ConclusionsIn otherwise healthy OSA patients, long-term CPAP is associated with attenuation of hypoxia-driven VEGF pathways without altering Ang-2 trajectories, supporting non-hypoxic mechanisms of vascular risk that merit further investigation.

Since the first report over four decades ago on the use of continuous positive airway pressure (CPAP) via a nasal mask to eliminate obstructive apneas, there have been few major advances in the treatment of obstructive sleep apnea (OSA) [1]. CPAP remains the first-line therapy for most patients with moderate-to-severe OSA who do not have correctable anatomical abnormalities. When properly used, it abolishes apneas and markedly reduces both daytime symptoms (mainly excessive sleepiness) and nocturnal symptoms (snoring, nocturia, awakenings) [2]. It also lowers blood pressure in hypertensive OSA patients, particularly those with resistant hypertension [3], and long-term observational data suggest potential reductions in cardiovascular morbidity and mortality [4]. However, several randomized controlled trials of 3–5 years in OSA patients with ischemic heart disease have failed to demonstrate benefit for secondary cardiovascular prevention [5–7], leaving the impact of CPAP on long-term survival uncertain.
In clinical practice, CPAP pressure is determined through manual or automatic titration, followed by periodic adjustment to minimize side effects and ensure adherence. The RICCADSA trial recently reported that CPAP pressures>7cm H2O were associated with increased circulating angiopoietin-2 (Ang-2)—a pro-inflammatory factor linked to endothelial activation—and reduced vascular endothelial growth factor (VEGF), a biomarker with potential cardioprotective properties [8]. This biomarker profile has been linked to increased cardiovascular risk [7,8]. Importantly, RICCADSA participants were survivors of myocardial infarction due to coronary artery disease (CAD), a group not representative of the broader OSA population. Given that most CPAP-treated patients with OSA receive pressures above 7 cmH2O, these findings raised concern that CPAP might induce a pro-inflammatory state even in most patients with OSA without established cardiovascular disease (CVD). Moreover, clinical trials in heart-failure populations have shown conflicting cardiovascular outcomes with CPAP or servo-ventilation [9,10], emphasizing the complexity of its vascular impact. Therefore, there is an unmet need to clarify the vascular biomarker response to CPAP in OSA patients without cardiovascular comorbidities.
To address this question, we analyzed longitudinal changes in Ang-2, VEGF, and related endothelial and inflammatory biomarkers at baseline, 1 year, and 5 years in the Epigenetics Modification in Obstructive Sleep Apnea (EPIOSA) study, an ongoing prospective cohort of OSA patients free of established cardiovascular disease and managed with or without CPAP according to current guidelines [11].
MethodsThe EPIOSA study is a 5-year, prospective, non-interventional cohort study conducted at the Sleep Clinic of Hospital Universitario Miguel Servet, Zaragoza, Spain (ClinicalTrials.gov: NCT02131610) [11,12]. Its primary aim is to identify biomarkers and epigenetic factors associated with the prevalence and progression of subclinical atherosclerosis in OSA patients free from established cardiovascular and major metabolic comorbidities.
Consecutive participants aged 20–60 years were recruited during the first year. Inclusion criteria were: (1) Apnea–hypopnea index (AHI)≥15events/h (OSA group) or AHI<5events/h (control group); (2) willingness to participate and provide written informed consent; and (3) availability for 5 years of follow-up visits. For the purpose of this analysis, we excluded a previous diagnosis of diabetes, metabolic or endocrine disorders, cardiovascular or cerebrovascular diseases, autoimmune disease, malignancy, chronic inflammatory, infectious, or respiratory diseases; morbid obesity (BMI≥40kg/m2); sleep disorders other than OSA; prior upper airway surgery or previous CPAP therapy.
All participants received standardized lifestyle counseling, including recommendations for regular exercise, a healthy diet, and avoidance of smoking and alcohol. The study protocol was approved by the Regional Institutional Review Board of Aragón, Spain (IRB#03/2013, February 13, 2013). All participants provided written informed consent.
Clinical assessmentBaseline evaluation included standardized questionnaires covering demographics, anthropometrics, lifestyle factors, comorbidities, and medications. Daytime sleepiness was assessed with the Epworth Sleepiness Scale (ESS) [13], and blood pressure was measured by certified nurses following international guidelines [14].
Sleep study and CPAP managementAll participants underwent at home unattended sleep study with a type 3 polygraphy (ApneaLink Air, ResMed, San Diego, CA). Recorded signals included nasal pressure, thoracoabdominal effort, oxygen saturation, snoring, and body position. Events were scored manually per AASM criteria [15]. OSA was diagnosed at AHI≥10events/h to account for possible underestimation in home studies [16]. OSA patients were managed according to routine clinical practice and contemporary guideline recommendations. Because of the observational design of the study, treatment allocation was not randomized. CPAP prescription was based on OSA severity, daytime symptoms, physician clinical judgment, and patient acceptance of therapy. CPAP titration was conducted with auto-CPAP (Autoset-T; ResMed, Sydney, Australia) following validated national protocols [17], and adherence was monitored via device timers.
Biochemical determinationsAt baseline and annually, fasting blood samples were collected into serum gel, EDTA, sodium fluoride, and PaxgeneW tubes (PreAnalytix GmbH). For this analysis, only baseline, 1-year, and 5-year samples were used. Plasma Ang-2, Tie-2, VEGF, and E-selectin were quantified by ELISA (RayBiotech) in duplicate. Detection limits were 10 pg/mL for VEGF and Ang-2, 20 pg/mL for Tie-2, and 30 pg/mL for E-selectin, with intra-assay and inter-assay coefficients of variation below 10%. Glucose, triglycerides, total cholesterol, and HDL-C were measured by spectrophotometry (ILAB 650, Instrumentation Laboratory); apolipoproteins A and B by nephelometry (IMMAGE 800, Beckman Coulter); and hsCRP by particle-enhanced turbidimetric immunoassay. Additional baseline biomarkers, which included suppressor of tumorigenicity-2 (sST2), soluble receptor for advanced glycation end-products (sRAGE), Fms-like tyrosine kinase-1 or vascular endothelial growth factor receptor-1 (Flt-1 or VEGFR-1), tumor necrosis factor-alpha (TNF-α), interleukin-6 (IL-6), interleukin-18 (IL-18), interleukin-10 (IL-10), and C-C motif chemokine ligand 2 or monocyte chemoattractant protein-1 (CCL2 or MCP-1), were quantified using a customized bead-based assay (BioLegend). These markers were chosen to characterize vascular inflammation and endothelial function relevant to OSA-related cardiovascular risk.
Statistical analysisContinuous variables are summarized as median (interquartile range) and categorical variables as number (percentage). Biomarker concentrations were examined for distributional properties and were natural log-transformed to improve normality and stabilize variance. For clarity of clinical interpretation, descriptive statistics presented in tables and figures are shown in the original measurement scale.
The primary analyses focused on the four prespecified core biomarkers (angiopoietin, Tie-2, VEGF, and E-selectin), measured at baseline, 12 months, and 60 months. Longitudinal changes were analyzed using linear mixed-effects models with fixed effects for study group, visit, and the group x visit interaction, additionally adjusting for sex, body mass index (BMI), and baseline apnea-hypopnea index (AHI). A subject-specific random intercept was included to account for within-participant correlation. Models were estimated using restricted maximum likelihood. Estimated marginal means were used to derive baseline between-group differences and within-group contrasts comparing 12 and 60 months with baseline. Pairwise contrasts were adjusted for multiple comparisons within each model using Bonferroni correction. In addition, eight additional exploratory biomarkers were available only at baseline. Baseline differences among study groups for these biomarkers were assessed using linear models with study group as the main factor, yielding one overall p value per biomarker.
To account for multiple testing across biomarkers, p values were further adjusted using the Benjamini–Hochberg false discovery rate procedure, applied within prespecified sets of biomarkers corresponding to primary (core) and exploratory analyses.
Exploratory correlation and regression analyses were considered hypothesis-generating and should therefore be interpreted cautiously. Associations between study variables and circulating biomarkers were explored with Spearman correlations. Demographic, anthropometric, sleep-related, biochemical, and inflammatory variables showing significant associations in univariable analyses (p<0.05) were subsequently entered into stepwise multiple linear regression models to identify independent predictors. Regression assumptions (linearity, independence, normality, and homoscedasticity) were verified using residual analyses and variance inflation factors (VIF<10). Final models were reported with standardized regression coefficients (β), corresponding p-values, and the coefficient of determination (r2) as a measure of explained variance. Statistical significance was set at p<0.05 (two-tailed). All statistical analyses were performed using IBM SPSS Statistics for Windows, version 29.0 (IBM Corp., Armonk, NY, USA, 2022).
ResultsOf the 326 participants enrolled, 72 had AHI<5events/h (controls) and 195 had AHI>15events/h (OSA). Among patients with moderate-to-severe OSA, 118 received CPAP therapy and 77 were managed with usual care (Fig. 1).

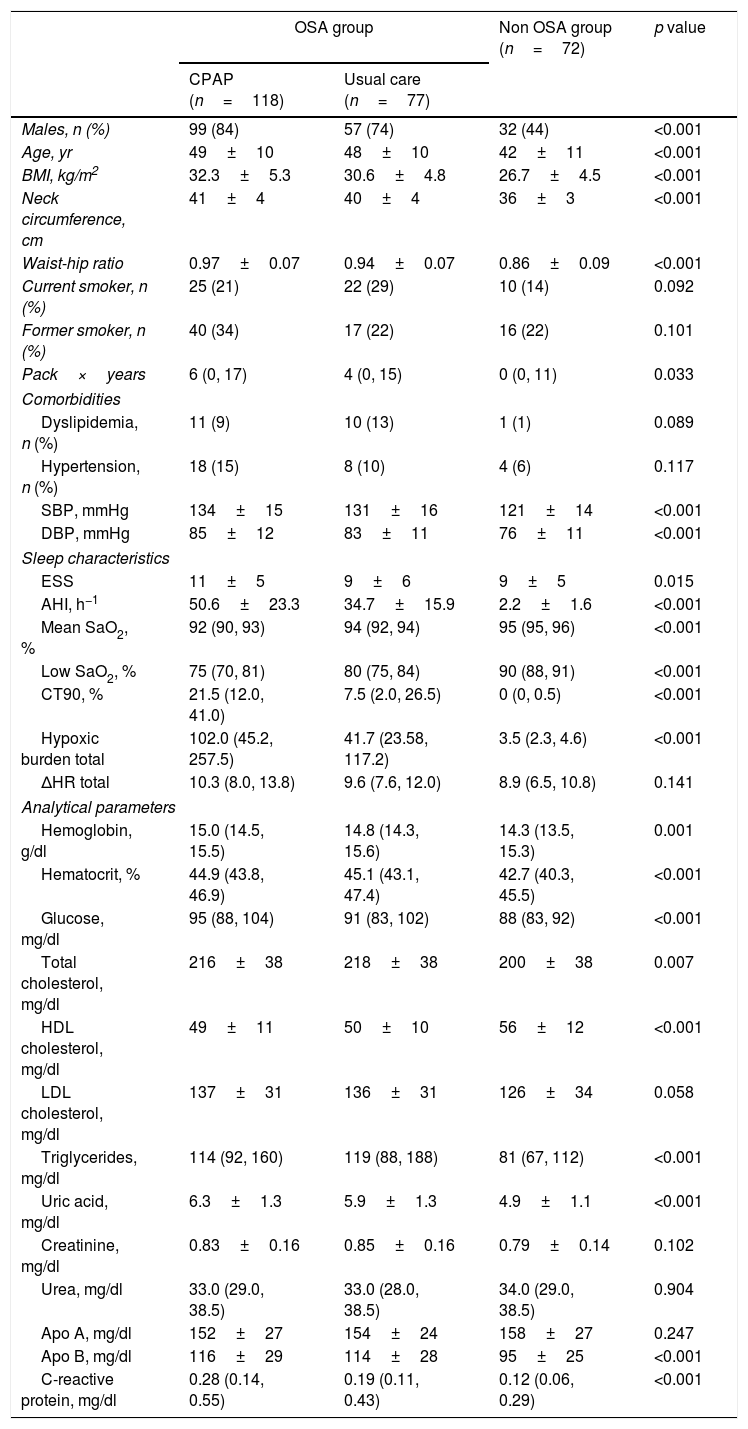
Baseline characteristics are presented in Table 1. Compared with controls, both OSA groups were older and had higher BMI, neck circumference, waist-to-hip ratio, and blood pressure. As expected, OSA groups exhibited more severe sleep abnormalities and elevated hematocrit, fasting glucose, lipid profile parameters, uric acid, apolipoprotein B, and C-reactive protein. Medication use and baseline plasma biomarker concentrations are summarized in Tables S1 and S2. At baseline, E-selectin and VEGF were significantly higher in both OSA groups than in controls, while Ang-2 and Tie-2 showed no significant differences.
General characteristics of study subjects.
| OSA group | Non OSA group (n=72) | p value | ||
|---|---|---|---|---|
| CPAP (n=118) | Usual care (n=77) | |||
| Males, n (%) | 99 (84) | 57 (74) | 32 (44) | <0.001 |
| Age, yr | 49±10 | 48±10 | 42±11 | <0.001 |
| BMI, kg/m2 | 32.3±5.3 | 30.6±4.8 | 26.7±4.5 | <0.001 |
| Neck circumference, cm | 41±4 | 40±4 | 36±3 | <0.001 |
| Waist-hip ratio | 0.97±0.07 | 0.94±0.07 | 0.86±0.09 | <0.001 |
| Current smoker, n (%) | 25 (21) | 22 (29) | 10 (14) | 0.092 |
| Former smoker, n (%) | 40 (34) | 17 (22) | 16 (22) | 0.101 |
| Pack×years | 6 (0, 17) | 4 (0, 15) | 0 (0, 11) | 0.033 |
| Comorbidities | ||||
| Dyslipidemia, n (%) | 11 (9) | 10 (13) | 1 (1) | 0.089 |
| Hypertension, n (%) | 18 (15) | 8 (10) | 4 (6) | 0.117 |
| SBP, mmHg | 134±15 | 131±16 | 121±14 | <0.001 |
| DBP, mmHg | 85±12 | 83±11 | 76±11 | <0.001 |
| Sleep characteristics | ||||
| ESS | 11±5 | 9±6 | 9±5 | 0.015 |
| AHI, h−1 | 50.6±23.3 | 34.7±15.9 | 2.2±1.6 | <0.001 |
| Mean SaO2, % | 92 (90, 93) | 94 (92, 94) | 95 (95, 96) | <0.001 |
| Low SaO2, % | 75 (70, 81) | 80 (75, 84) | 90 (88, 91) | <0.001 |
| CT90, % | 21.5 (12.0, 41.0) | 7.5 (2.0, 26.5) | 0 (0, 0.5) | <0.001 |
| Hypoxic burden total | 102.0 (45.2, 257.5) | 41.7 (23.58, 117.2) | 3.5 (2.3, 4.6) | <0.001 |
| ΔHR total | 10.3 (8.0, 13.8) | 9.6 (7.6, 12.0) | 8.9 (6.5, 10.8) | 0.141 |
| Analytical parameters | ||||
| Hemoglobin, g/dl | 15.0 (14.5, 15.5) | 14.8 (14.3, 15.6) | 14.3 (13.5, 15.3) | 0.001 |
| Hematocrit, % | 44.9 (43.8, 46.9) | 45.1 (43.1, 47.4) | 42.7 (40.3, 45.5) | <0.001 |
| Glucose, mg/dl | 95 (88, 104) | 91 (83, 102) | 88 (83, 92) | <0.001 |
| Total cholesterol, mg/dl | 216±38 | 218±38 | 200±38 | 0.007 |
| HDL cholesterol, mg/dl | 49±11 | 50±10 | 56±12 | <0.001 |
| LDL cholesterol, mg/dl | 137±31 | 136±31 | 126±34 | 0.058 |
| Triglycerides, mg/dl | 114 (92, 160) | 119 (88, 188) | 81 (67, 112) | <0.001 |
| Uric acid, mg/dl | 6.3±1.3 | 5.9±1.3 | 4.9±1.1 | <0.001 |
| Creatinine, mg/dl | 0.83±0.16 | 0.85±0.16 | 0.79±0.14 | 0.102 |
| Urea, mg/dl | 33.0 (29.0, 38.5) | 33.0 (28.0, 38.5) | 34.0 (29.0, 38.5) | 0.904 |
| Apo A, mg/dl | 152±27 | 154±24 | 158±27 | 0.247 |
| Apo B, mg/dl | 116±29 | 114±28 | 95±25 | <0.001 |
| C-reactive protein, mg/dl | 0.28 (0.14, 0.55) | 0.19 (0.11, 0.43) | 0.12 (0.06, 0.29) | <0.001 |
Values are mean±standard deviation, median (interquartile range) or number (percentage), according to their type and distribution. Comparisons were performed using chi-squared or Fisher's exact tests for categorical variables, as appropriate, and ANOVA or Kruskal–Wallis tests for the continuous variables.
Abbreviations: BMI, body mass index; SBP, systolic blood pressure; DBP, diastolic blood pressure; IMT, intima-media thickness; ESS, Epworth sleepiness scale; AHI, apnea–hypopnea index; SaO2, oxyhemoglobin saturation; CT90, time with SaO2<90%; HDL, high-density lipoprotein; LDL, low-density lipoprotein; Apo, apolipoprotein.
In OSA, baseline Ang-2 correlated positively with body weight (ρ=0.265, p<0.001), BMI (ρ=0.239, p=0.001), hypoxic burden (ρ=0.211, p=0.018), plasma sST2 (ρ=0.380, p<0.001), sRAGE (ρ=0.375, p<0.001) and Flt-1 (ρ=0.273, p=0.011). In multivariable models, only body weight (β=0.376, p=0.006) and plasma sST2 (β=0.666, p<0.001) remained independent predictors of baseline Ang-2 (Table S3 and Fig. S1). E-selectin correlated with age (ρ=0.178, p=0.013), body weight (ρ=0.181, p=0.011), BMI (ρ=0.250, p<0.001), waist-to-hip ratio (ρ=0.155, p=0.031), ESS score (ρ=0.150, p=0.039), mean nocturnal saturation (ρ=0.204, p=0.005), CT90.(ρ=0.180, p=0.014), and plasma concentrations of hemoglobin (ρ=0.155, p=0.032), triglycerides (ρ=0.204, p=0.004), sST2 (ρ=0.363, p<0.001) and IL-6 (ρ=0.387, p<0.001). Multivariable analysis identified body weight (β=0.274, p=0.003), sST2 (β=0.317, p=0.001), and IL-6 (β=0.378, p<0.001) as independent predictors (Table S4 and Fig. S2).
CPAP-treated patients used the device for an average of 6.7±1.1h at a mean pressure of 11±2cm H2O, with 112 patients (95%) meeting adherence criteria. Anthropometric variables differed between groups but remained stable over time (Table S5).
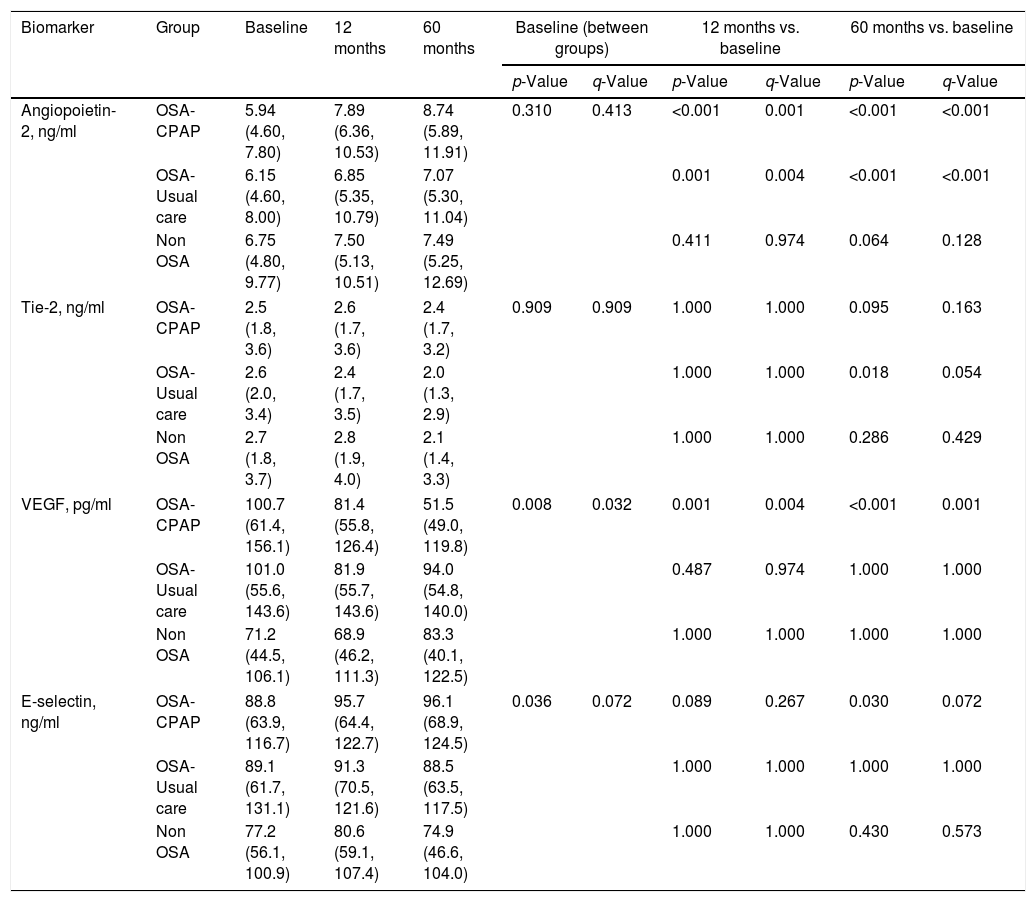
Plasma Ang-2 concentrations increased over time in patients with OSA irrespective of treatment allocation, whereas participants without OSA showed minimal longitudinal variation (Table 2). Formal interaction analyses showed no significant differences in Ang-2 trajectories between groups (group×visit interaction: F=1.118, p=0.347). Plasma VEGF concentrations in CPAP-treated patients were approximately 40–50% lower at follow-up compared with baseline values, whereas minimal longitudinal variation was observed in untreated OSA patients or controls. Formal interaction analyses confirmed significantly different VEGF trajectories between groups (group×visit interaction: F=3.154, p=0.012). No significant interaction effects were observed for Tie-2 or E-selectin.
Circulating biomarkers at baseline and after 12- and 60-months follow-up in patients with moderate-to-severe obstructive sleep apnea (OSA: with CPAP therapy or usual care) or without OSA.a
| Biomarker | Group | Baseline | 12 months | 60 months | Baseline (between groups) | 12 months vs. baseline | 60 months vs. baseline | |||
|---|---|---|---|---|---|---|---|---|---|---|
| p-Value | q-Value | p-Value | q-Value | p-Value | q-Value | |||||
| Angiopoietin-2, ng/ml | OSA-CPAP | 5.94 (4.60, 7.80) | 7.89 (6.36, 10.53) | 8.74 (5.89, 11.91) | 0.310 | 0.413 | <0.001 | 0.001 | <0.001 | <0.001 |
| OSA-Usual care | 6.15 (4.60, 8.00) | 6.85 (5.35, 10.79) | 7.07 (5.30, 11.04) | 0.001 | 0.004 | <0.001 | <0.001 | |||
| Non OSA | 6.75 (4.80, 9.77) | 7.50 (5.13, 10.51) | 7.49 (5.25, 12.69) | 0.411 | 0.974 | 0.064 | 0.128 | |||
| Tie-2, ng/ml | OSA-CPAP | 2.5 (1.8, 3.6) | 2.6 (1.7, 3.6) | 2.4 (1.7, 3.2) | 0.909 | 0.909 | 1.000 | 1.000 | 0.095 | 0.163 |
| OSA-Usual care | 2.6 (2.0, 3.4) | 2.4 (1.7, 3.5) | 2.0 (1.3, 2.9) | 1.000 | 1.000 | 0.018 | 0.054 | |||
| Non OSA | 2.7 (1.8, 3.7) | 2.8 (1.9, 4.0) | 2.1 (1.4, 3.3) | 1.000 | 1.000 | 0.286 | 0.429 | |||
| VEGF, pg/ml | OSA-CPAP | 100.7 (61.4, 156.1) | 81.4 (55.8, 126.4) | 51.5 (49.0, 119.8) | 0.008 | 0.032 | 0.001 | 0.004 | <0.001 | 0.001 |
| OSA-Usual care | 101.0 (55.6, 143.6) | 81.9 (55.7, 143.6) | 94.0 (54.8, 140.0) | 0.487 | 0.974 | 1.000 | 1.000 | |||
| Non OSA | 71.2 (44.5, 106.1) | 68.9 (46.2, 111.3) | 83.3 (40.1, 122.5) | 1.000 | 1.000 | 1.000 | 1.000 | |||
| E-selectin, ng/ml | OSA-CPAP | 88.8 (63.9, 116.7) | 95.7 (64.4, 122.7) | 96.1 (68.9, 124.5) | 0.036 | 0.072 | 0.089 | 0.267 | 0.030 | 0.072 |
| OSA-Usual care | 89.1 (61.7, 131.1) | 91.3 (70.5, 121.6) | 88.5 (63.5, 117.5) | 1.000 | 1.000 | 1.000 | 1.000 | |||
| Non OSA | 77.2 (56.1, 100.9) | 80.6 (59.1, 107.4) | 74.9 (46.6, 104.0) | 1.000 | 1.000 | 0.430 | 0.573 | |||
Data are presented as median (interquartile range). Baseline differences among the three study groups were assessed for each biomarker using linear mixed-effects models fitted on log-transformed concentrations, from which baseline between-group contrasts were derived. Longitudinal changes within each group were evaluated by comparing biomarker concentrations at 12 months and 60 months with baseline using planned contrasts based on estimated marginal means from the same mixed-effects models. For each contrast, nominal two-sided p values are reported together with p values adjusted for multiple comparisons using the Benjamini–Hochberg false discovery rate procedure (q values), applied within the prespecified family of core biomarkers.
No consistent dose–response relationship was observed between CPAP exposure variables and Ang-2 trajectories at either follow-up time point. In contrast, modest associations were identified between CPAP pressure and longitudinal VEGF changes at both follow-up visits. Fig. 2 illustrates the differential relationships between CPAP exposure and longitudinal changes in VEGF and Ang-2 concentrations.

At 12 months, increases in Ang-2 correlated inversely with baseline Ang-2 (ρ=−0.420, p<0.001) and ApoA (ρ=−0.221, p=0.022), and positively with hematocrit (ρ=0.305, p=0.001). At 60.months, changes in Ang-2 correlated inversely with baseline Ang-2 (ρ=−0.171, p=0.020), mean nocturnal saturation (ρ=−0.311, p=0.001), and HDL cholesterol (ρ=−0.219, p=0.021), and positively with waist-to-hip ratio (ρ=0.280, p=0.003), CT90 (ρ=0.317, p<0.001), fasting glucose (ρ=0.148, p=0.046), ApoA (ρ=−0.202, p=0.003), and CCL2 (MCP-1) (ρ=0.303, p=0.029). Multivariable analysis retained baseline Ang-2 (β=−0.512, p<0.001) and hematocrit (β=0.426, p<0.001) as independent predictors of the 12-month change and mean nocturnal saturation (β=−0.229, p=0.020) for the 60-month change (Table S6 and Fig. S3).
For VEGF, 12-month changes correlated with baseline VEGF (ρ=−0.676, p<0.001), waist-to-hip ratio (ρ=0.191, p=0.038), mean nocturnal oxygen saturation (ρ=−0.189, p=0.043), and CT90 (ρ=0.200, p=0.035), while the 60-month changes correlated only with baseline VEGF (ρ=−0.549, p<0.001). Multivariable analysis identified baseline VEGF (β=−0.674, p<0.001) and waist-to-hip ratio (β=0.175, p=0.012) as independent predictors at 12 months, and baseline VEGF (β=−0.494, p<0.001) as the sole predictor at 60 months (Table S7 and Fig. S4). Additional mixed-effects models including baseline VEGF concentrations as a covariate showed materially unchanged longitudinal VEGF trajectories in the CPAP-treated group, suggesting that regression-to-the-mean effects alone are unlikely to explain the observed findings.
DiscussionIn this prospective cohort of moderate-to-severe OSA patients free of major comorbidities, long-term CPAP therapy was associated with a substantial and sustained reduction in VEGF concentrations, with median levels approximately halved during follow-up compared with baseline. Although the clinical implications of this magnitude of change remain uncertain, the consistency of the findings over 5 years supports a biologically relevant modulation of hypoxia-responsive pathways. These findings contrast with those reported in OSA patients with established CVD, where CPAP failed to consistently alter VEGF or even reduced potentially cardio protective biomarkers [6,18]. Our data therefore extend the previous evidence by demonstrating that, in otherwise healthy OSA patients, CPAP may be associated with favorable vascular effects, at least concerning VEGF biology.
VEGF is a potent endothelial mitogen essential for angiogenesis and vascular permeability [19]. In OSA, intermittent hypoxia stimulates VEGF production via hypoxia-inducible factor-1α (HIF-1α) activation [20], representing an adaptive mechanism to preserve microvascular integrity. The long-term reduction in VEGF observed here in CPAP-treated patients likely reflects suppression of nocturnal hypoxemia and associated oxidative stress. While the clinical impact of reduced VEGF remains uncertain, it could be associated with less maladaptive neovascularization and vascular remodeling associated with early atherosclerosis [21,22]. Further mechanistic studies should clarify whether VEGF downregulation under CPAP is accompanied by improvements in endothelial function and microvascular health.
In contrast to VEGF, Ang-2 trajectories appeared largely independent of CPAP exposure. The longitudinal increases observed were relatively modest in magnitude and were similarly present in untreated participants and controls, arguing against a clinically meaningful CPAP-related pro-inflammatory effect. This pattern suggests that Ang-2 dynamics may be influenced by non-OSA-specific or non-hypoxic factors. Ang-2, an endothelial-derived growth factor stored in Weibel–Palade bodies, antagonizes angiopoietin-1 at the Tie-2 receptor, promoting endothelial activation, inflammation, and vascular permeability [23]. Elevated circulating Ang-2 has been linked to adverse cardiovascular outcomes in diverse populations, including those with CAD [24], heart failure [25], and critical illness [26].
The RICCADSA trial reported higher Ang-2 levels in OSA patients with CAD treated with CPAP pressures>7cm H2O [8]. In contrast, in our cohort neither prescribed pressure nor nightly CPAP usage correlated with Ang-2 changes at 1 or 5 years. This divergence likely reflects differences in baseline vascular status; in CAD, the vascular endothelium is primed toward an activated, pro-inflammatory state [27], possibly rendering it more susceptible to mechanical or shear stress-related perturbations from CPAP therapy. By contrast, in otherwise healthy OSA cohort, endothelial homeostasis may buffer any pressure-related stress.
The progressive rise in Ang-2 in both OSA and control participants may be associated with age-related endothelial dysfunction and low-grade vascular inflammation [28], processes known to upregulate Ang-2 expression [29]. Metabolic factors (waist-to-hip ratio, glucose, HDL cholesterol, and hematocrit) were also associated with Ang-2 changes, supporting this hypothesis. The possibility that Ang-2 elevation reflects cumulative environmental or lifestyle exposures not captured in our protocol should also be considered. Other contributors, such as subclinical infection, oxidative stress, or intermittent sympathetic activation—can trigger Weibel–Palade body exocytosis and Ang-2 release [30].
The observed association between Ang-2 and baseline sST2 concentrations in OSA raises the possibility of coordinated vascular and myocardial inflammatory activation independent of hypoxia. Ang-2, a well-established marker of endothelial injury and vascular inflammation, remained elevated despite CPAP exposure, suggesting the involvement of alternative triggers such as alveolar stretch, systemic inflammation, or complement activation [31]. Likewise, sST2, a member of the interleukin-1 receptor family, reflects myocardial stress and fibrosis and is generally considered to be independent of hypoxia-driven signaling [32]. Although longitudinal sST2 measurements were not available, these findings suggest that endothelial and myocardial inflammatory pathways may coexist in OSA beyond hypoxemia-related mechanisms.
In CVD patients, Ang-2 is closely associated with vascular remodeling and adverse outcomes [33], but in our comorbidity-free cohort its long-term prognostic value remains unclear. The presence of similar trajectories in controls suggests that Ang-2 could reflect vascular aging rather than OSA-specific effects.
Overall, our findings suggest that inflammatory and angiogenic pathways activated in OSA may respond differently to CPAP exposure. While VEGF concentrations were lower during follow-up in CPAP-treated patients, Ang-2 trajectories did not significantly differ between study groups and showed no consistent relationship with CPAP exposure variables, underscoring their distinct regulatory mechanisms. VEGF is largely hypoxia-dependent through HIF-1α, whereas Ang-2 responds to cytokines (e.g., TNF-α, IL-1β) and hemodynamic stimuli [34,35]. These observations suggest that CPAP exposure may be associated with modulation of hypoxia-related signaling, whereas low-grade inflammatory activation may follow different longitudinal patterns. Given the observational design and non-randomized treatment allocation, these findings should be interpreted as longitudinal associations between CPAP exposure and vascular biomarker trajectories rather than evidence of direct causal effects.
Clinically, these results indicate that long-term CPAP is unlikely to exacerbate systemic inflammation via Ang-2 upregulation in patients without CVD, alleviating concerns raised by prior studies [8]. The absence of association between CPAP pressure and Ang-2 changes supports maintaining current titration practices. Furthermore, we have recently demonstrated that in real-world practice, in patients with OSA, with or without cardiovascular comorbidities, very long-term use of CPAP (14 years on average) is not only not associated with an increase in adverse cardiovascular effects, but also significantly reduces major cardiovascular events compared to OSA patients who were not treated with CPAP [36]. These observations are consistent with the long-term cardiovascular safety and potential benefit of CPAP use in patients with OSA.
This study has several limitations. First, biomarker measurements were limited to baseline, 1-year, and 5-year intervals. Second, the observational design precludes definitive causal inference, and treatment allocation was not randomized. Third, despite stringent exclusion criteria, residual confounding from unmeasured variables (e.g., dietary factors, subclinical infections) cannot be excluded. Fourth, most participants underwent unattended type 3 polygraphy rather than full polysomnography for OSA diagnosis. Although this approach may underestimate AHI and introduce some degree of OSA severity misclassification, the devices used were previously validated and type 3 polygraphy is widely accepted in routine clinical practice. Moreover, the use of conservative diagnostic thresholds likely minimized clinically meaningful misclassification between groups. Fifth, the ELISA assays used have intra- and inter-assay variability that, although within acceptable ranges, could influence the detection of small changes. Finally, while our cohort was well characterized, the sample size—particularly in the control group—limits the precision of subgroup analyses and the generalizability to other populations, including women and older adults.
In conclusion, in moderate-to-severe OSA patients without established cardiovascular disease, long-term CPAP exposure was associated with lower VEGF concentrations over follow-up, whereas Ang-2 trajectories appeared largely independent of CPAP exposure. Ang-2 increased over time in both OSA and non-OSA participants without a clear relationship to CPAP pressure or adherence. These findings support differential longitudinal behavior between hypoxia-related and inflammation-related angiogenic pathways in OSA. Future studies with randomized designs and more comprehensive sleep assessment are needed to clarify the causal and clinical significance of these biomarker trajectories.
Author contributionDSR, CCZ, FGR, and JMM contributed to the study design. DSR, CCZ, MM-O, EDG, JR-S, PPM, CL-F, FGR, and JMM collected the data. CCZ and FGR performed the data analyses. DSR, CCZ, FGR, and JMM contributed to data interpretation. DSR, CCZ, FGR, and JMM drafted the first version of the manuscript. All authors reviewed, critically revised, and approved the final manuscript. DSR and CCZ contributed equally as co-primary authors; FGR and JMM contributed equally as co-senior authors.
Artificial intelligence involvementArtificial intelligence tools were not used in the preparation of this manuscript.
FundingSupported by Instituto de Salud Carlos III, Ministry of Health, Spain and the European Regional Development Fund (FEDER) (PI21/01954; CD22/00033), Department of Science and Universities, Government of Aragon, Spain (CUS/1638/2022; B22_23R), IIS Aragón, Spain (INTRAMURAL23/FSE-I/01) and Spanish Respiratory Society – SEPAR- (Research Grant 1584-2024).
Conflict of interestThe authors declare no competing interests.
Data sharingDe-identified individual participant data, along with the data dictionary and analytic code used in this study, are available upon reasonable request. Researchers interested in accessing these materials should submit a brief proposal outlining the planned analysis to the corresponding author. Data will be shared after review and approval of the proposal, provided that the intended use complies with ethical and legal requirements.
The followings are the supplementary data to this article:


articles







Archivos de Bronconeumología follows the Recommendations for the Conduct, Reporting, Editing and Publication of Scholarly Work in Medical Journals
