




Eosinophilic granulomatosis with polyangiitis (EGPA) is an ANCA-associated vasculitis of uncertain cause, characterized by eosinophil-rich necrotizing granulomatous inflammation and small- to medium-vessel necrotizing vasculitis [1]. Its European prevalence is about 12 cases per million, likely underestimated [2]. Clinical presentation is heterogeneous, ranging from non-severe disease to life- or organ-threatening disease affecting the lungs, heart, kidneys, central nervous system, or gastrointestinal tract [3]. Pathogenesis involves mainly Th2-driven eosinophilic inflammation, with IL-5 playing a central role [4,5]. Mepolizumab, an anti-IL-5 monoclonal antibody, is recommended for remission maintenance and for relapsing or refractory EGPA without life- or organ-threatening disease, although evidence in new-onset disease remains limited [6,7]. This study assessed the effectiveness of mepolizumab for remission induction and withdrawal of glucocorticoid (GC) maintenance therapy over 52 weeks.
We conducted a multicentre, observational, retrospective cohort study including adults diagnosed with new-onset EGPA between 2021 and 2025, with or without life- or organ-threatening disease, who were treated at diagnosis with mepolizumab 300mg every 4 weeks plus systemic glucocorticoids as remission-induction therapy and followed for at least 52 weeks. Treatment decisions were made by the treating physicians according to routine clinical practice and were not protocol-driven. Patients receiving cyclophosphamide or rituximab induction, lower doses of mepolizumab, or treatment for relapsed/refractory EGPA were excluded [8]. EGPA was diagnosed by the treating physicians on the basis of compatible clinical features, objective evidence of vasculitic or eosinophilic organ involvement, exclusion of relevant mimicking conditions, and multidisciplinary consensus [2,8]. Biopsy-proven vasculitis was documented in 15 patients. The 2022 ACR/EULAR classification criteria were applied retrospectively to support cohort homogeneity, and all patients achieved a score ≥6 after exclusion of alternative diagnoses.
Primary endpoints were remission at weeks 24 and 52 and GC dose reduction at weeks 24 and 52. Secondary endpoints were GC withdrawal at weeks 24 and 52; improvement in FEV1, asthma control test (ACT), and asthma quality of life questionnaire (AQLQ) at weeks 24 and 52; reduction in asthma exacerbations at week 52; EGPA relapse after starting mepolizumab and reduction in peripheral eosinophil counts. Subgroup analysis compared outcomes in patients with and without life-or-organ-threatening disease. Remission was defined as absence of systemic or inflammatory manifestations, no relapses, and prednisone dose ≤4mg/day or equivalent [1]. Statistical significance was set at p<0.05. This retrospective study was approved by the local ethics committee (2025.746).
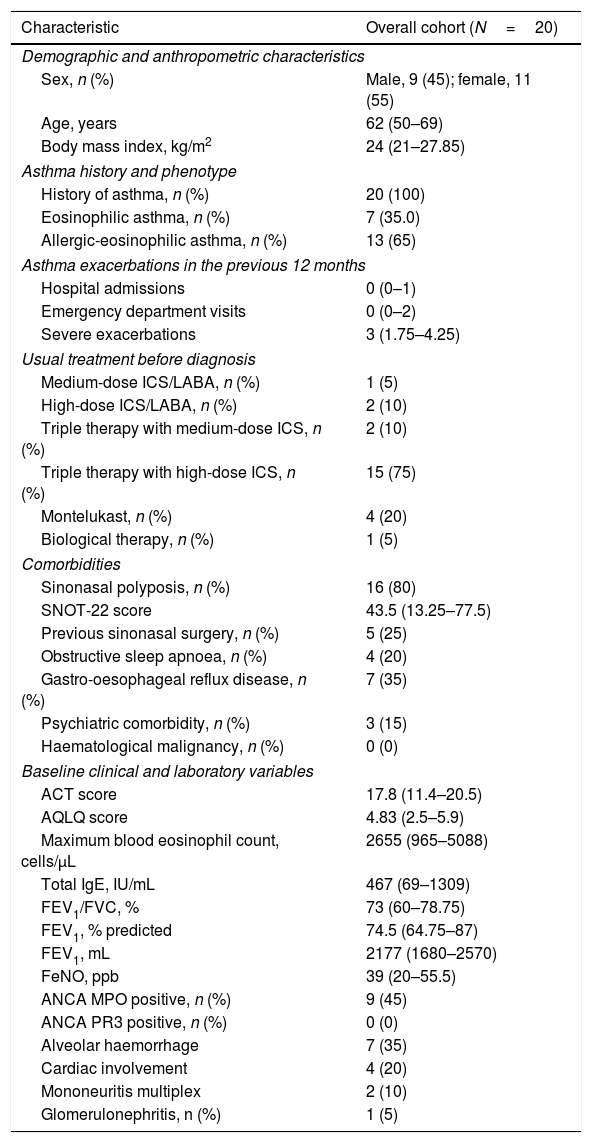
A total of 20 patients were included, of whom 14 presented with life-or-organ-threatening disease (alveolar haemorrhage: 7, cardiac involvement: 4, mononeuritis multiplex: 2, and glomerulonephritis: 1). Baseline characteristics are presented in Table 1. Remission with mepolizumab 300 mg was achieved in 90% at week 24 and 95% at week 52. There were no significant differences between patients with and without life- or organ-threatening disease at week 24 (93% vs 83%, p = 0.15) or week 52 (100% vs 83%, p = 0.07). 45% of patients were ANCA-positive. Nonetheless, in the subset of patients in whom BVAS was recorded, the mean initial score was 2, with a significant reduction of 80% at week 24 (2 vs 0.40, p<0.001) and of 92.5% at week 52 (2 vs 0.15, p<0.001). Notably, 6 of these 7 patients (85.7%) achieved a BVAS of 0 together with a prednisone dose ≤4mg/day, meeting the stricter remission definition used in several other published EGPA cohorts.
Baseline characteristics of the study cohort.
| Characteristic | Overall cohort (N=20) |
|---|---|
| Demographic and anthropometric characteristics | |
| Sex, n (%) | Male, 9 (45); female, 11 (55) |
| Age, years | 62 (50–69) |
| Body mass index, kg/m2 | 24 (21–27.85) |
| Asthma history and phenotype | |
| History of asthma, n (%) | 20 (100) |
| Eosinophilic asthma, n (%) | 7 (35.0) |
| Allergic-eosinophilic asthma, n (%) | 13 (65) |
| Asthma exacerbations in the previous 12 months | |
| Hospital admissions | 0 (0–1) |
| Emergency department visits | 0 (0–2) |
| Severe exacerbations | 3 (1.75–4.25) |
| Usual treatment before diagnosis | |
| Medium-dose ICS/LABA, n (%) | 1 (5) |
| High-dose ICS/LABA, n (%) | 2 (10) |
| Triple therapy with medium-dose ICS, n (%) | 2 (10) |
| Triple therapy with high-dose ICS, n (%) | 15 (75) |
| Montelukast, n (%) | 4 (20) |
| Biological therapy, n (%) | 1 (5) |
| Comorbidities | |
| Sinonasal polyposis, n (%) | 16 (80) |
| SNOT-22 score | 43.5 (13.25–77.5) |
| Previous sinonasal surgery, n (%) | 5 (25) |
| Obstructive sleep apnoea, n (%) | 4 (20) |
| Gastro-oesophageal reflux disease, n (%) | 7 (35) |
| Psychiatric comorbidity, n (%) | 3 (15) |
| Haematological malignancy, n (%) | 0 (0) |
| Baseline clinical and laboratory variables | |
| ACT score | 17.8 (11.4–20.5) |
| AQLQ score | 4.83 (2.5–5.9) |
| Maximum blood eosinophil count, cells/μL | 2655 (965–5088) |
| Total IgE, IU/mL | 467 (69–1309) |
| FEV1/FVC, % | 73 (60–78.75) |
| FEV1, % predicted | 74.5 (64.75–87) |
| FEV1, mL | 2177 (1680–2570) |
| FeNO, ppb | 39 (20–55.5) |
| ANCA MPO positive, n (%) | 9 (45) |
| ANCA PR3 positive, n (%) | 0 (0) |
| Alveolar haemorrhage | 7 (35) |
| Cardiac involvement | 4 (20) |
| Mononeuritis multiplex | 2 (10) |
| Glomerulonephritis, n (%) | 1 (5) |
Note. Data are presented as median (IQR) unless otherwise stated.
Abbreviations. ACT, Asthma Control Test; AQLQ, Asthma Quality of Life Questionnaire; FEV1, forced expiratory volume in 1 second; FVC, forced vital capacity; FeNO, fractional exhaled nitric oxide; ICS, inhaled corticosteroid; IgE, immunoglobulin E; IQR, interquartile range; LABA, long-acting beta2-agonist; NR, not reported; p-ANCA, perinuclear anti-neutrophil cytoplasmic antibody; SNOT-22, 22-item Sino-Nasal Outcome Test.
Median GC dose after hospital discharge was 55mg prednisone-equivalent/day (interquartile range [IQR 40–70mg]). GC dose decreased significantly by week 24 (55 vs 5mg, p<0.001) and week 52 (55 vs 2.25mg, p=0.002) (Fig. 1). This reduction was maintained in both subgroups at week 24 (life-or-organ-threatening disease: 60 vs 3.8mg, p<0.001; non-severe EGPA: 42.5 vs 3.8mg, p=0.02) and week 52 (60 vs 2mg, p<0.001; 42.5 vs 2.5mg, p=0.01) (Fig. 1). It was accompanied by a reduction in asthma exacerbations overall (3 vs 0, p<0.001), also seen in subgroup analyses (4 vs 0, p<0.01; 2 vs 0, p<0.01).

Among patients who achieved remission, 30% withdrew GC by week 24 and 60% by week 52. No significant subgroup differences were observed at week 24 (29% vs 33%, p=0.10) or week 52 (64% vs 50%, p=0.06).
Remission was associated with significant improvement in FEV1 at week 24 (2177 vs 2333mL, p<0.01) and week 52 (2177 vs 2541mL, p<0.001), with improvement in both subgroups. Baseline FEV1 did not differ between with and without life-or-organ-threatening disease (2206 vs 2110mL, p=0.9), nor at week 24 (2354 vs 2270mL, p=0.14), although a between-group difference emerged at week 52 (2675 vs 2352mL, p=0.02).
Asthma control also improved significantly, with ACT increasing from 17.8 to 23.5 at week 24 (p<0.001) and to 23.0 at week 52 (p=0.003), and AQLQ from 4.83 to 6.44 at week 24 (p=0.012) and 6.51 at week 52 (p=0.011). Both subgroups improved significantly. Patients with life-or-organ-threatening disease had lower baseline ACT (15 vs 18, p=0.03) and AQLQ (4.7 vs 5.5, p=0.04), but there were no subgroup differences at week 24 (ACT 23 vs 24, p=0.15; AQLQ 6.5 vs 6.4, p=0.08) or week 52 (ACT 22 vs 23, p=0.1; AQLQ 6.1 vs 6.7, p=0.06).
Only one patient relapsed after starting mepolizumab 300mg. Maximum peripheral eosinophil counts decreased significantly (3924 vs 150 cells/μL, p=0.01), and this reduction was maintained in both subgroups. No serious adverse events, major infections, or treatment discontinuations related to mepolizumab were observed.
In this multicentre retrospective cohort of patients with new-onset EGPA, mepolizumab 300mg every 4 weeks, administered in combination with GC as remission-induction therapy, was associated with high remission rates at 24 and 52 weeks, substantial GC sparing, improved asthma-related outcomes, and a low relapse rate over 52 weeks. Although these findings do not support replacing cyclophosphamide or rituximab but suggest that early IL-5 blockade may benefit carefully selected patients with severe eosinophilic EGPA. Prospective controlled studies are warranted to define the optimal candidates, timing of initiation, and combination strategies for this approach. Comparisons with previous studies are limited by differences in disease stage, prior immunosuppression, and remission definitions. Nevertheless, our findings are broadly comparable to previous real-world mepolizumab series.
Ueno et al. [9] compared 7 patients with new-onset EGPA and life-or-organ-threatening disease treated with mepolizumab 300mg plus high-dose GC with 13 patients treated with cyclophosphamide plus high-dose GC. Patients treated with mepolizumab achieved disease control comparable to intravenous cyclophosphamide, with faster GC tapering and fewer adverse events. Importantly, the reduced need for conventional immunosuppressive therapy supports broader control of systemic disease activity beyond asthma.
Another case series [10] included 10 patients with new-onset EGPA with life- or organ-threatening disease treated with mepolizumab 300mg and followed for 2 years. All patients achieved remission by week 8, with a 50% reduction in corticosteroid use at 2 years, consistent with our findings. A further study [11] included 10 patients with EGPA treated with mepolizumab 100mg during the remission-induction phase and followed for at least 12 months. Most had received prior immunosuppression. The 60% complete remission rate was lower than in our cohort, possibly reflecting the lower mepolizumab dose. That study also reported a significant reduction in GC dose, from 13.0±6.3mg/day to 3.3±3.1mg/day.
These comparisons should nevertheless be interpreted cautiously, as some patients had relapsing disease. Collectively, these findings suggest that eosinophilic inflammation may drive disease in selected patients with life- or organ-threatening EGPA, supporting IL-5 blockade as a potential therapeutic approach. An important implication of our findings concerns the role of conventional induction immunosuppressive therapy.
As emphasized in the recent review by Nanzer, et al. [12], patients without poor prognostic factors may achieve remission with GC alone, whereas randomized evidence supporting azathioprine, methotrexate, or mycophenolate for induction remains lacking. Current treatment algorithms therefore continue to reserve cyclophosphamide or rituximab mainly for life-or-organ-threatening disease or clearly vasculitic phenotypes. Our findings do not challenge that framework outright, but they broaden the discussion by showing that high remission rates were observed without cyclophosphamide or rituximab in a cohort that included many patients with life-or-organ-threatening disease, particularly in those with a more inflammatory phenotypic profile and clinical features driven predominantly by eosinophilic inflammation rather than vasculitic damage.
In addition, subgroup comparisons should be interpreted with caution, as the sample size was limited and the study was not powered to detect moderate differences between patients with and without life-or-organ-threatening disease. In this context, two large-scale studies are currently underway. One is the E-MERGE clinical trial [13], while data from another large real-world cohort, MEPEARL [14], suggest better outcomes in patients treated with mepolizumab than in those receiving conventional immunosuppressive therapy.
The remaining published evidence on the efficacy of mepolizumab during the remission-induction phase of EGPA is limited to case reports and small case series [15–20]. The main limitations of our study include its retrospective design, small sample size, and lack of a control group. Potential selection bias should also be acknowledged, as treatment allocation may have favoured patients with a predominantly eosinophilic phenotype. In addition, the use of a pragmatic remission definition may limit direct comparisons with other series. Nevertheless, the study also has notable strengths, including its multicenter design, 52-week follow-up, inclusion of a well-defined population with new-onset EGPA, subgroup analyses, and the use of the approved 300mg dose of mepolizumab.
These findings support the prospective evaluation of early IL-5 blockade as a remission-induction strategy in carefully selected patients with newly diagnosed EGPA.
EthicsThe study was conducted in accordance with the Declaration of Helsinki and was approved by the Ethics Committee of Hospital Universitario La Paz (2025.746). All patient data were anonymised before analysis, and confidentiality was maintained in compliance with Spanish Organic Law 3/2018 on Personal Data Protection. Owing to the retrospective, observational design, written informed consent was not required.
Artificial intelligenceMedical writing and English-language editing support, including refinement of scientific style, were provided in part by an artificial intelligence-based tool (ChatGPT 5.2, OpenAI) and were subsequently reviewed and approved by the authors.
Role of the funding sourceThere was no funding source in the study design, data collection, data analysis, data interpretation, or writing of the report. The corresponding author had full access to all the data in the study and had final responsibility for the decision to submit the manuscript for publication.
Conflicts of interestThe authors certify that none of them have any conflicts of interest.








